



Abstract
The evolution of brain tumor surgery has progressed from "microsurgery" to "precision neurosurgery," currently entering a new stage characterized by the deep integration of multimodal technologies and the concept of preserving functional brain networks. This article systematically reviews the current state of research on preserving brain functional networks during brain tumor surgery. It summarizes the composition of brain functional networks, the impact of brain tumors on these networks, the classification of multimodal technologies, and the application progress of protecting key functional networks during brain tumor surgery. It emphasizes that precision surgical strategies based on preserving functional brain networks can significantly improve patient quality of life and provide a new paradigm for translational brain science research.
Keywords: Brain Tumor; Multimodal Techniques; Functional Brain Networks; Neuroprotection; Glioma Surgery
The Need for Functional Brain Network Preservation in the Era of Precision Neurosurgery
The central challenge in brain tumor treatment lies in achieving a balance between maximal tumor resection and the preservation of neurological function. Although traditional anatomy-guided surgery has benefitted from microsurgical innovations, approximately 36%–56% of patients still experience postoperative neurological deficits, including language, motor, or cognitive impairments [1]. With advancements in neuroimaging, neurosurgery has transitioned from the era of “microsurgery” to that of “precision neurosurgery”, placing brain function preservation at its core. Research indicates that brain functions rely on the synergistic operation of dynamic networks involving multiple brain regions, driving an evolution in surgical strategy from purely "anatomical resection" towards "network preservation" (Figure 1). This shift is particularly critical in surgeries for tumors located in eloquent areas such as the frontal lobe and basal ganglia [2].
Figure 1. From anatomical excision to network preservation: an evolving paradigm in brain tumor surgery.
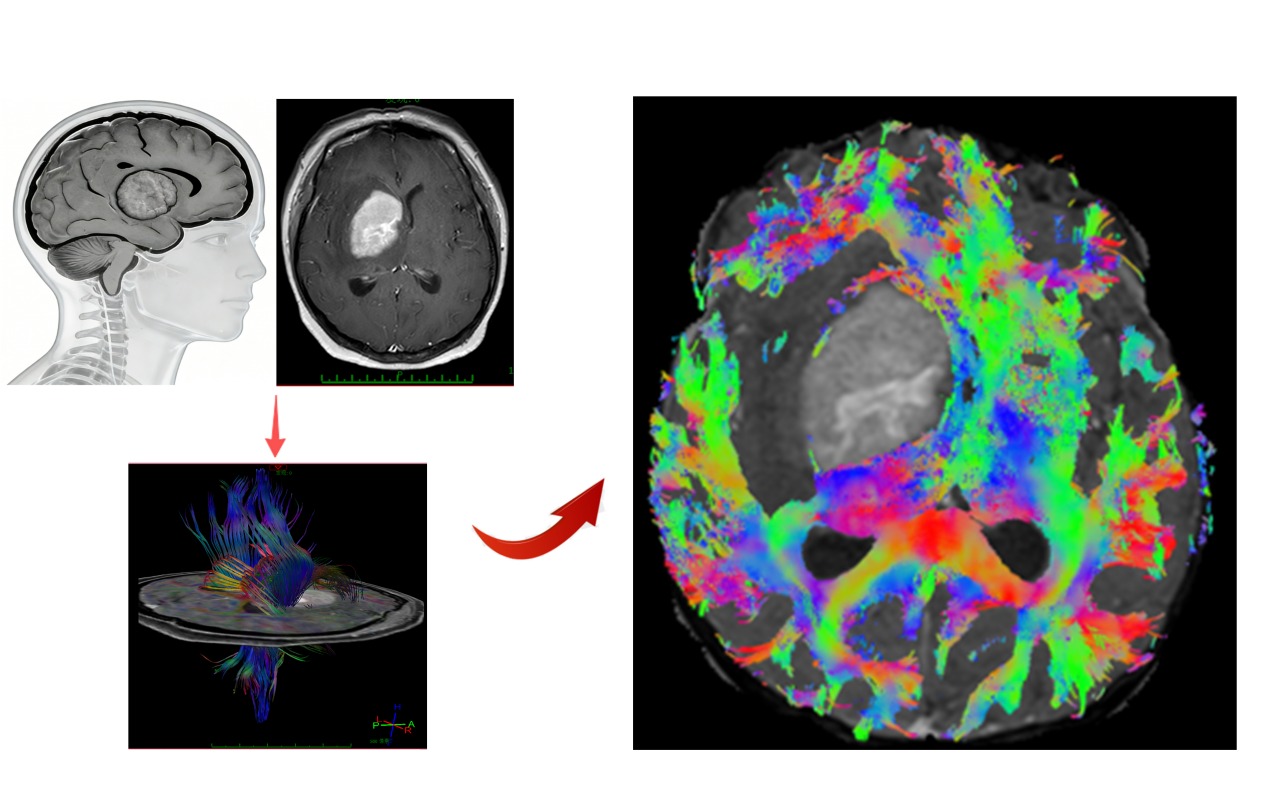
This figure illustrates the paradigm shift in brain tumor surgery from traditional anatomical resection to modern network-based preservation.
Multimodal technology is not merely a simple image overlay, but rather achieves deep integration of “structural-functional-molecular” information through cross-modal data fusion algorithms. It constructs personalized brain connectome maps, enabling visualization and quantification of the topological relationships between tumors and functional networks, thereby overcoming the limitations of single-data approaches [3–5]. Such advances have shifted the focus of surgical planning from lesion-centered localization to network-oriented functional preservation [6–7]. In this regard, connectome-based neurosurgery has emerged as an integrative paradigm that explicitly incorporates large-scale brain network organization into surgical decision-making, extending beyond traditional modular brain mapping. In this context, functional brain networks provide the theoretical framework through which multimodal information can be interpreted and applied in precision neurosurgery.
Functional brain networks refer to functionally synergistic systems formed by spatially separated brain regions through the synchronization of neural activity [8–9]. The strength of their connections can be quantified using neuroimaging techniques and supports multi-level functions ranging from basic perception to high-level cognition [10]. However, it should be acknowledged that the definition and reproducibility of functional brain networks—particularly those derived from resting-state fMRI—remain subject to ongoing methodological debate. Recent reviews highlight that resting-state fMRI is sensitive to acquisition parameters, preprocessing pipelines, and substantial inter-individual variability, which poses challenges for clinical translation [13–14]. These networks exhibit specific topological properties (e.g., modularity, small-world properties), whose strength and dynamic changes are constrained but not fully determined by underlying structural connectivity, with structure–function coupling itself varying systematically across the cortical hierarchy [2, 11–12]. They are further organized through rich-club architecture—a topological property in which highly connected hub regions (such as the precuneus and superior frontal gyrus) are preferentially interconnected with one another beyond what would be expected by chance, thereby enabling efficient global information integration. Accordingly, the clinical significance of multimodal guidance lies in its ability to simultaneously characterize these structural and functional dimensions, thereby allowing surgeons to identify critical cortical regions and subcortical pathways more precisely [15]. During brain tumor surgery, combining two types of critical information, static structural connectivity and dynamic task-based activation networks, enables precise localization of critical functional areas and neural fiber tracts. This approach optimizes surgical strategies to preserve brain function and maximize patients' postoperative quality of life [15].
This article systematically reviews the composition of functional brain networks, multimodal protective technologies, and future research directions, aiming to provide a theoretical basis for establishing new surgical protocols grounded in the preservation of functional brain networks, with the ultimate goal of maximizing tumor resection rates and improving patient quality of life.
Composition of Functional Brain Networks
Functional brain networks are conceptualized as organized assemblies of neural regions defined by the temporal correlation or functional coherence of spontaneous neural activity. Their functional organization is not random, but follows a hierarchically coordinated architecture, with primary sensorimotor systems supporting basic perception and action and higher-order association systems subserving socio-affective, cognitive, and executive functions [16–18]. This hierarchical organization is established early in development and refined through experience, providing the scaffolding upon which complex cognition emerges. Based on their functional attributes, functional brain networks can be broadly categorized into traditional and non-traditional systems. The complex and adaptive operations of the brain arise from the integrative and cooperative interactions among these distributed networks (Figure 2, Table 1).
Figure 2. Composition and function of brain functional networks.
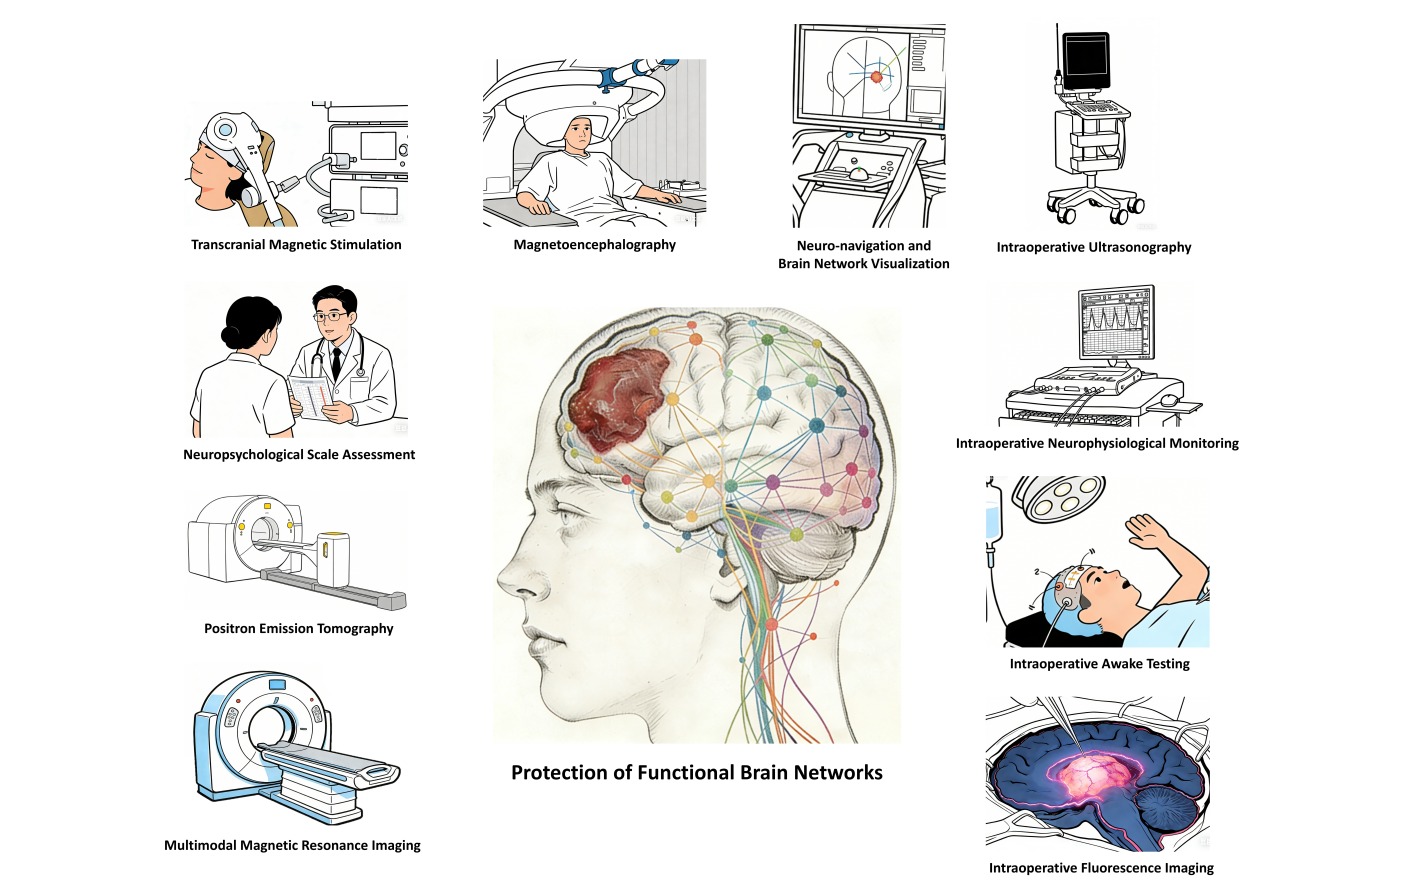
This figure depicts the major human brain functional networks and their core functions.
Table 1. Composition and functions of functional brain networks
| Category | Name | Constituent Structures | Anatomical Location | Core Functions | Symptoms After Damage |
|---|---|---|---|---|---|
| Traditional Functional Brain Networks | Sensorimotor Network (SMN) | Precentral gyrus, Postcentral gyrus, Supplementary motor area | Brain convexity (Frontoparietal lobe) | Somatosensory integration, Motor control | Hemiplegia, Sensory loss, Motor ataxia |
| Visual Network (VN) | Primary visual cortex (V1), Extrastriate cortex (V2-V5) | Occipital lobe and temporo-occipital junction | Visual information processing | Hemianopia, Visual agnosia, Metamorphopsia | |
| Auditory Network (AN) | Transverse temporal gyrus (Heschl's gyrus), Superior temporal gyrus | Superior part of temporal lobe | Auditory signal processing | Auditory agnosia, Tinnitus, Speech comprehension impairment | |
| Language Network (LangN) | Broca's area (Left inferior frontal gyrus), Wernicke's area (Posterior part of left superior temporal gyrus) | Left hemisphere dominant (Frontotemporal lobe) | Language expression and comprehension | Aphasia (Expressive/Receptive) | |
| Non-traditional Functional Brain Networks | Default Mode Network (DMN) | Posterior cingulate cortex, Medial prefrontal cortex, Angular gyrus, Parahippocampal gyrus | Midline structures (Medial frontal-parietal-temporal) | Introspection, Episodic memory, Social cognition | Autism, Cognitive decline in Alzheimer's disease |
| Salience Network (SN) | Anterior insula, Anterior cingulate cortex, Dorsolateral prefrontal cortex | Fronto-insulo-cingulate circuit | Attentional switching, Conflict detection | Schizophrenia, Executive dysfunction | |
| Central Executive Network (CEN) | Dorsolateral prefrontal cortex, Posterior parietal cortex | Bilateral frontoparietal lobe | Working memory, Decision making | Attention deficit, Impaired planning | |
| Limbic Network (LimbN) | Amygdala, Hypothalamus, Anterior cingulate cortex, Orbitofrontal cortex | Medial anterior brain | Emotional processing, Stress response | Anxiety, Depression, Emotional dysregulation | |
| Dorsal Attention Network (DAN) | Frontal eye field, Intraparietal sulcus, Superior parietal lobule | Dorsal posterior parietal-frontal lobe | Goal-directed attention | Neglect syndrome, Attention distraction | |
| Ventral Attention Network (VAN) | Temporoparietal junction, Ventral prefrontal cortex, Anterior insula | Right ventral temporo-parieto-frontal lobe | Stimulus-driven attention capture | Spatial neglect (Right hemisphere damage) |
Note: Functional brain networks are divided into traditional and non-traditional systems according to their major functional domains. The constituent structures listed are representative core regions rather than a complete set of anatomical components. The symptoms after damage refer to common manifestations associated with dysfunction of each network.
Traditional functional brain networks are directly associated with fundamental sensory and motor functions, primarily including the Sensorimotor Network (SMN), Visual Network (VN), Auditory Network (AN), and Language Network (LangN). In contrast, non-traditional functional brain networks participate in higher-order cognitive, affective, and introspective processes. These include the Default Mode Network (DMN, including the posterior cingulate cortex, precuneus, medial prefrontal cortex, angular gyrus, and parahippocampal gyrus), Salience Network (SN), Central Executive Network (CEN), Limbic Network (LimbN), Dorsal Attention Network (DAN), and Ventral Attention Network (VAN) [19–34]. Although these networks lack clearly defined physical structural boundaries, they are crucial for maintaining cognitive integrity and emotional stability. It should be emphasized, however, that the level of evidence varies across networks:the DMN has been most robustly identified across individuals and clinical populations, whereas the reproducible identification of SN, CEN, DAN, and VAN in tumor patients remains methodologically challenging. Consensus has not yet been reached regarding which non-traditional networks can be reliably preserved through surgical intervention—an area requiring further empirical investigation.
Impact of Brain Tumor Invasion on Functional Brain Networks
Brain tumors disrupt network topology and interfere with neural signal transmission, thereby causing deficits in cognition, motor function, and other domains [35–37]. Glioma growth and infiltration exhibit marked network dependency:high-grade gliomas (HGG) have been reported to preferentially invade rich-club hub regions such as the insula and temporal lobe, whereas low-grade gliomas (LGG) tend to favor locally densely connected regions in the frontal cortex [38–40]. However, the available evidence is heterogeneous, and not all studies confirm a strict HGG–hub versus LGG–periphery dichotomy; therefore, these patterns should be regarded as probabilistic tendencies rather than absolute rules. This selective infiltration pattern might reflect the biological and connectomic properties of hub-enriched regions, including their high metabolic activity and dense integration within large-scale brain networks [41–42].
At the clinical level, such network-dependent invasion is reflected not only in global connectome disruption but also in focal damage to eloquent cortical regions and subcortical pathways [43]. A multimodal imaging analysis of 115 patients with low-grade glioma (LGG) showed that injury involving the precentral gyrus, middle frontal gyrus, and insula, as well as major white matter tracts such as the arcuate fasciculus and corticospinal tract, was directly associated with reduced language fluency [44]. In addition, among 45 patients with insular glioma, 98% showed tumor proximity to or invasion of higher-order cognitive functional networks, further emphasizing the widespread impact of glioma infiltration on distributed brain systems and the limitations of conventional anatomy-based surgery in achieving true functional preservation [45].
Effects of brain tumor mass effect on functional brain networks
Brain tumor mass effect alters functional brain networks through both structural distortion and secondary functional reorganization [46–48]. Compression of white matter pathways, edema-related displacement, and disruption of large-scale connectivity can affect key systems such as the CEN and DMN [42]. Benign tumors more often cause displacement of adjacent fiber tracts, whereas aggressive gliomas are more likely to induce substantial tract disruption and broader connectome-level impairment, although these effects should be interpreted as a spectrum rather than a strict binary distinction based on FA alone [49]. In parallel, the brain may undergo compensatory remodeling through perilesional recruitment, interhemispheric redistribution, and reconfiguration of hub-related interactions [50].
Importantly, glioma-induced network disruption is not a passive process but involves active glioma–neuron interactions; recent work demonstrates that glioblastoma can disrupt cortical network activity at multiple spatial and temporal scales and remodel neuronal circuits in ways that promote regional immunosuppression [51–52]. Clinically, this means that adaptive remodeling may preserve function in the short term but still leave patients vulnerable to postoperative cognitive decline, especially when higher-order association systems are involved [50].
Significance of Functional Brain Network Preservation
In brain tumor treatment, the delicate balance between tumor resection and preservation of brain function presents a critical clinical decision-making challenge [53–54]. Preservation of traditional functional brain networks is crucial for postoperative quality of life. Intraoperative neuronavigation and mapping enable maximal safe resection, which has been associated with improved motor and language preservation as well as extended survival in selected glioma cohorts [55–56]. Gliomas infiltrate functional brain networks; focal resection risks damaging critical white matter tracts (e.g., arcuate fasciculus, corticospinal tract), causing permanent neurological deficits [57]. Traditional functional brain network preservation provides the structural substrate for neuroplasticity, facilitating long-term recovery.
Preservation of non-traditional networks (e.g., default mode network (DMN), salience network (SN)) represents a critical advance toward whole-brain network protection [58–59]. Up to approximately 36%–56% of patients exhibit cognitive deficits attributable, at least in part, to non-traditional network damage, although the precise contribution of individual networks to specific deficits varies across studies [1]. Safeguarding these networks is increasingly considered important to reduce postoperative memory decline and emotional disturbance. Intraoperative preservation of the DMN helps prevent episodic memory impairment, thereby significantly improving postoperative memory retention and the patient's ability for self-care [60].
Methods and Techniques for Functional Brain Network Preservation
Preoperative Multimodal Evaluation
In preoperative planning for brain tumor surgery, high-resolution structural imaging, functional activation mapping, and diffusion-based white matter tractography should be integrated to define the individualized spatial and network relationships between the tumor and functional brain networks [61–63]. Contemporary network-based frameworks emphasize that multimodal assessment is necessary not only to localize the lesion but also to identify functionally preserved tissue, estimate network vulnerability, and guide maximal safe resection [64–65]. Advanced diffusion imaging and connectome-based analyses can further characterize tumor-related displacement, compression, or infiltration of major white matter pathways, thereby improving patient-specific surgical planning [66]. In addition, individualized functional imaging may reveal preserved sensorimotor and cognitive network organization within or adjacent to tumor tissue, highlighting the value of personalized, network-informed preoperative evaluation [6, 67].
Neuronavigation-guided preoperative planning
Neuronavigation-guided preoperative planning integrates structural MRI, diffusion-based tractography, functional mapping, and, when appropriate, navigated transcranial magnetic stimulation to generate patient-specific anatomy-function maps for surgical planning [68]. In preoperative assessment, these multimodal data help define the spatial relationship between tumors and eloquent cortical and subcortical systems, thereby supporting trajectory design and functional preservation [69–70]. In selected glioma patients, amino-acid PET such as 11C-MET-PET can further complement MRI by improving delineation of tumor extent and infiltration margins [71]. Together, these approaches support more individualized surgical decision-making and may help reduce the risk of postoperative neurological deficits.
Preoperative Transcranial Magnetic Stimulation (TMS)
TMS technology, through precise neurofunctional localization and multimodal imaging integration, provides critical preoperative assessment and planning for functional brain network preservation [72]. Navigated TMS (nTMS), fused with electromagnetic navigation and 3D MRI, can preoperatively map primary motor cortex somatotopy and delineate tumor–motor cortex spatial relationships, helping to anticipate functional risk before surgery [73]. Combined with DTI corticospinal tract reconstruction, it quantifies tumor-tract distances, providing "function-structure" coupling models for trajectory planning that have been associated with reductions in postoperative motor deficits compared with anatomical-only localization [74–75].Repetitive TMS inhibits naming errors to localize language areas, compensating for fMRI limitations from tumor edema. This electrophysiological approach enables preoperative risk stratification, multimodal navigation, and personalized surgical strategies, maximizing resection while optimizing functional brain network preservation [76]. Additionally, TMS assesses preoperative functional network plasticity [77]. Tumor mass effect induces network remodeling; TMS detects excitability changes and connectivity alterations, informing compensatory capacity for individualized planning. In patients intolerant of awake craniotomy (e.g., obesity, OSA), TMS serves as an alternative to intraoperative direct cortical stimulation for functional localization [78].
Preoperative Neuropsychological Assessment
Neuropsychological scales provide critical clinical value in preoperative and postoperative brain tumor evaluation by quantifying cognitive changes to inform surgical planning, risk prediction, and rehabilitation [79–81]. Rather than presenting isolated scales as universal recommendations, a domain-oriented assessment strategy is preferred, focusing on language, attention, executive function, and verbal memory according to tumor location and planned surgical strategy. Selection of specific scales is guided by their validation in neuro-oncological cohorts, sensitivity to focal cognitive deficits, and feasibility of repeat administration. For patients with aphasia, the “Aphasia Battery of Chinese (ABC)” is recommended due to its comprehensive evaluation of expressive and receptive language domains in Chinese-speaking populations [44]; for those with cognitive dysfunction, the “Montreal Cognitive Assessment (MoCA)” is advised given its established sensitivity for mild cognitive impairment [82–83]; for motor impairments, the “Motor Assessment Scale (MAS)” is suggested for its standardized evaluation of functional motor performance [84]; for verbal memory deficits, the “Hopkins Verbal Learning Test (HVLT)” is utilized owing to its validation in glioma populations [85]; and for spatial memory disorders, the "Blessed Dementia Rating Scale (BDRS)" is applied to establish preoperative functional baselines [86].
The integrating neuropsychological assessment with diffusion-based neuroimaging (e.g., DTI tractography/connectomics) helps identify tumor-related network disruption and interpret its functional relevance for cognitive risk stratification [42]. Scales serve as "functional landmarks" across tumor management:preoperative risk boundary definition, intraoperative functional preservation guidance, postoperative recovery trajectory monitoring [87–88]. Future integration of advanced neuroimaging and molecular biomarkers may facilitate a shift from group-level cognitive profiling toward individualized prediction, with the goal of improving cognitive preservation and oncological decision-making in glioma care [89–90].
Intraoperative Methods and Techniques for Functional Brain Network Preservation
To achieve maximal safe resection while preserving neurological function, multimodal strategies have been implemented across the preoperative, intraoperative, and postoperative stages (Figure 3).
Figure 3. Strategies for brain functional network preservation.
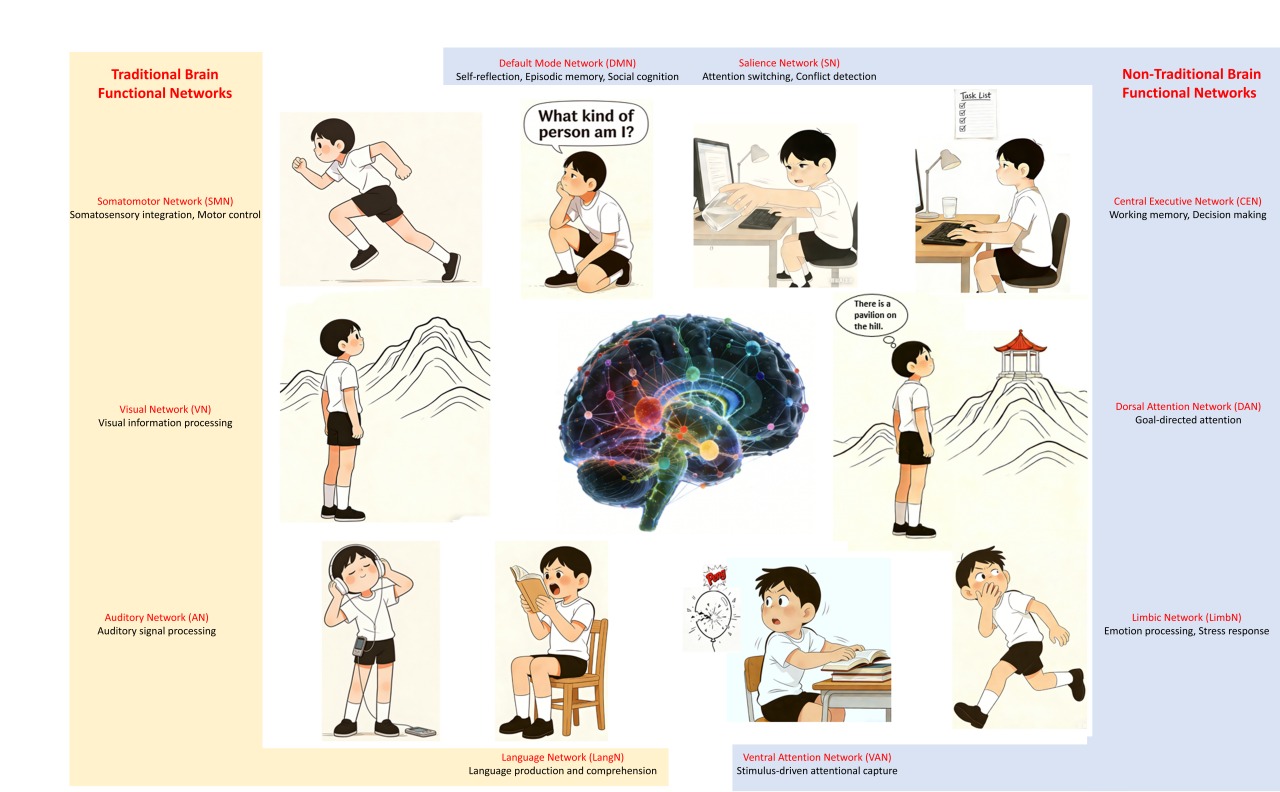
This figure summarizes the multimodal strategies used pre-, intra-, and post-operatively to protect brain functional networks during tumor surgery.
Functional Brain Network Reconstruction and Intraoperative Navigation
During brain tumor resection, multimodal neuronavigation establishes a framework for functional brain network preservation by integrating preoperative imaging with real-time anatomical scenes. By superimposing preoperative fMRI-based functional hotspots and DTI-based tractography models onto the surgical microscope view—often utilizing augmented reality—surgeons can visually identify the spatial relationship between the tumor and critical networks, such as language and motor pathways. When surgical instruments approach predefined safety boundaries, these systems provide distance-based proximity alerts to prevent inadvertent damage to subcortical tracts. However, because preoperative models are subject to intraoperative brain shift following dural opening and tumor resection, navigation data frequently require real-time updating with intraoperative MRI (iMRI) or ultrasound to maintain spatial accuracy [91–92].
Intraoperative navigation also facilitates the real-time integration of preoperatively acquired TMS mapping data with intraoperative direct electrical stimulation (DES) and continuous neuromonitoring [93]. While preoperative TMS provides a reliable initial cortical map showing high spatial concordance with DES, intraoperative DES remains the gold standard for functional localization, allowing dynamic adjustment of resection margins. Concurrently, continuous monitoring of motor evoked potentials (MEPs) and somatosensory evoked potentials (SEPs) provides real-time feedback on pathway integrity; notably, a significant amplitude drop in MEPs serves as a critical predictor of postoperative motor deterioration. This integrated mapping and monitoring approach has been shown to significantly reduce the incidence of permanent postoperative neurological deficits, thereby achieving an optimal balance between maximal safe resection and functional preservation [94–96].
Intraoperative Neurophysiological Monitoring (IONM)
IONM is a key adjunct in brain tumor surgery involving eloquent cortex or critical white-matter pathways. Its primary objective is to maximize tumor resection while preserving neurological function through real-time monitoring of neural pathways, proving particularly crucial during operations within eloquent brain areas. The IONM technical framework has become increasingly sophisticated, primarily encompassing:(1) Evoked potential monitoring, such as Motor Evoked Potentials (MEPs), Somatosensory Evoked Potentials (SSEPs), Brainstem Auditory Evoked Potentials (BAEPs), and Visual Evoked Potentials (VEPs) [97]; (2) Cortical and subcortical mapping techniques, where direct electrical cortical stimulation and electrocorticography (ECoG) can precisely delineate functional boundaries, significantly reducing the risk of permanent postoperative neurological deficits [98]; and (3) Cranial nerve monitoring, exemplified by facial nerve monitoring during vestibular schwannoma resection, which, combined with EMG recordings of muscle activity, substantially lowers the incidence of postoperative facial palsy [99]. Several studies indicate that patients undergoing brain tumor surgery with IONM have a significantly lower probability of functional sequelae compared to those without it [95, 100–101]. Furthermore, IONM enhances surgical safety. A German multicenter study demonstrated an IONM application rate of 46.4%, and its use was associated with a significant reduction in in-hospital mortality compared to cases where IONM was not employed [102].
iMRI and Intraoperative Ultrasonography (IOUS)
iMRI and IOUS enable dynamic correction of imaging discrepancies during surgery, addressing brain shift occurs after dural opening and tumor debulking [103–104]. iMRI acquires detailed, high-resolution images of intracranial structures, clearly displaying the tumor's location, morphology, and its relationship to surrounding eloquent tissues. This assists surgeons in precisely determining tumor boundaries, avoiding localization errors due to brain displacement, thereby enhancing resection accuracy and extent, monitoring surgical complications, guiding intraoperative strategy adjustments, and achieving maximal safe resection. Similarly, IOUS provides real-time guidance for surgical maneuvers, clearly visualizing the tumor's feeding arteries and draining veins, helping surgeons avoid critical vasculature and reduce intraoperative bleeding risk. A meta-analysis indicates that for pediatric brain tumors, IOUS is comparable to iMRI in estimating the extent of resection [105]. Combined with its lower cost and reduced requirements for radiation and contrast agents, IOUS is more readily applicable and promotable in primary hospitals or resource-limited settings, providing intraoperative imaging assistance for a broader patient population [106–107].
Awake Craniotomy (AC) and Intraoperative Functional Assessment
Guided by multimodal technology, awake craniotomy (AC) combined with intraoperative neurophysiological monitoring has become a cornerstone strategy for preserving functional brain networks. AC utilizes real-time cortical and subcortical electrical stimulation to dynamically map neural circuits, enabling maximal safe tumor resection while sparing critically functioning peritumoral tissue. High-level evidence from recent meta-analyses demonstrates that, compared with surgery under general anesthesia, AC significantly reduces the incidence of late severe neurological deficits and improves the extent of resection across various glioma subgroups [108–110].
The anesthetic management for AC must be carefully tailored to the individual patient, primarily involving either an Asleep-Awake-Asleep (SAS) technique or a continuous Conscious Sedation (Awake-Awake-Awake, AAA) approach [111]. SAS provides a robust sedation buffer during cranial opening and closure, making it highly suitable for patients with anxiety sensitivity or those anticipating particularly lengthy and complex resections. Conversely, AAA favors uninterrupted baseline monitoring and patient cooperation throughout the procedure [112]. The optimal choice is continuously refined based on tumor location, psychological assessment, and the multidisciplinary team's expertise, rather than rigid operative time constraints [108–109, 113–114].
Beyond traditional basic language and motor mapping, the integration of AC with advanced neurocognitive assessment has significantly evolved. Modern intraoperative functional assessment now incorporates tailored neuropsychological paradigms to monitor higher-order cognitive domains—such as executive function, visuospatial processing, and social cognition—in real time. By continuously correlating these intraoperative cognitive task performances with preoperative network models, surgeons can precisely adjust the resection trajectory to avoid disrupting distributed functional network hubs and connecting white matter tracts. This individualized approach ensures the integrity of large-scale cognitive networks, fundamentally optimizing postoperative quality of life [115–116].
Intraoperative Tumor Fluorescence Imaging
5-Aminolevulinic acid (5-ALA) fluorescence-guided surgery is an established adjunct in the resection of contrast-enhancing malignant gliomas [117]. After preoperative oral administration, 5-ALA is metabolized into fluorescent protoporphyrin IX within tumor cells, allowing intraoperative visualization of tumor tissue under blue-violet light. This improves identification of residual enhancing tumor and supports more complete resection when integrated with standard microsurgical and functional-guidance techniques [118]. In the landmark multicenter phase III randomized controlled trial by Stummer et al., 5-ALA-guided surgery achieved a higher rate of complete resection of contrast-enhancing tumor than white-light microsurgery alone (65% vs 36%, p<0.0001) and improved 6-month progression-free survival (41.0% vs 21.1%, p=0.0003), without increasing severe adverse events [119].
Rehabilitation Strategies for Postoperative Functional Brain Networks
Assessment Methods
Multimodal imaging may support postoperative rehabilitation planning by enabling comparison of tract integrity across preoperative and postoperative examinations. Preoperative DTI can delineate tumor-related compression or infiltration of critical white-matter pathways, such as the corticospinal tract and arcuate fasciculus, whereas postoperative DTI can help assess tract preservation, edema-related change, and structural injury [120]. When interpreted together with neurological or neuropsychological assessments, these imaging findings may help stratify functional risk, distinguish transient from persistent deficits, and estimate recovery potential during rehabilitation [121–122].
Rehabilitation Methods
Early postoperative inpatient rehabilitation focuses on improving patient consciousness levels, emphasizing early physical therapy intervention and multidisciplinary collaboration [123–124]. Progressive training from bed rest to walking reduces delirium risk by 43% and shortens hospital stay by 1 day [125]. For moderate-to-severe motor paralysis patients, repetitive facilitation training promotes early postoperative mobilization. Marciniak et al. analysis of 132 brain tumor patients demonstrates that multimodal-guided physical therapy significantly improves motor and cognitive efficiency, independent of tumor type [126–128].
In addition to conventional physical therapy, noninvasive neuromodulation techniques such as repetitive transcranial magnetic stimulation (rTMS) are increasingly utilized to facilitate neural plasticity [129–130]. Recent randomized, sham-controlled trials indicate that navigated low-frequency rTMS, when applied to the unaffected hemisphere or motor cortex alongside standard physical therapy, can effectively accelerate the recovery of specific motor deficits following the resection of motor-eloquent supratentorial tumors [131].
Furthermore, brain-computer interface (BCI) technology is emerging as a highly promising tool in neurorehabilitation. Although predominantly validated in broader neurological injuries such as stroke, BCI systems utilize visual or proprioceptive feedback during motor imagery to activate residual cortical areas [132–133]. Advanced neuroimaging demonstrates that such BCI-guided training can stimulate targeted neuroplasticity and strengthen functional connectivity within compromised sensorimotor networks, offering a novel synergistic approach to optimize long-term upper limb functional scores in post-surgical neuro-oncology patients [134–136].
Significance of Functional Brain Network Assessment for Rehabilitation Training
Functional brain network assessment provides critical guidance for postoperative brain tumor rehabilitation, offering a comprehensive scientific framework from preoperative planning to postoperative intervention [137]. Preoperative fMRI and DTI localize tumor-infiltrated cortical nodes and subcortical tracts; combined with intraoperative mapping and clinical scales, these modalities help optimize surgical trajectories to preserve residual functioning networks. Postoperatively, network-based evaluations enable the design of personalized rehabilitation protocols. For instance, rather than adopting a uniform rehabilitation strategy, identifying specific disruptions in the sensorimotor network or the default mode network (DMN) allows clinicians to implement concurrent, targeted physical and cognitive therapies tailored to the patient's unique deficit profile [137–140].
This "network-based subtyping" overcomes the limitations of traditional, one-size-fits-all rehabilitation approaches. Recent advanced neuroimaging studies demonstrate that brain tumors not only cause localized structural damage but also induce global alterations in functional network topology—such as changes in network segregation and hub centrality—that are closely correlated with specific cognitive outcomes; notably, increased network segregation following therapy may reflect either compensatory adaptation or maladaptive reorganization, depending on its impact on cognitive performance [138, 141]. Monitoring these functional connectivity patterns longitudinally helps estimate a patient's neuroplastic potential, thereby facilitating dynamic adjustments of training intensity and supporting a more precise, individualized neurorehabilitation strategy [142–143].
Challenges and Future Directions of Functional Brain Networks
Despite the clear clinical value of functional brain network preservation, significant challenges persist in daily neuro-oncological practice [144–145]. First, interindividual functional variability and intraoperative brain shift resulting from cerebrospinal fluid loss frequently degrade the spatial accuracy of preoperative navigation data. Second, resting-state fMRI–based network identification remains susceptible to acquisition and preprocessing variability, limiting reproducibility, particularly for non-traditional networks such as SN, CEN, and attention systems. Furthermore, acquiring and interpreting multimodal network imaging is time-consuming, resource-intensive, and challenging for widespread adoption in resource-limited settings [146]. A critical unresolved issue is the accurate characterization of network resilience during tumor infiltration and the ability to confidently predict postoperative compensatory plasticity using individualized network models [111, 147].
Future directions must address these limitations by shifting the surgical paradigm from an "experience-driven" approach to a precision "data-driven" framework. A highly promising avenue involves integrating large-scale connectomics data with artificial intelligence (AI) and machine learning algorithms [3, 122, 148]. Such integration aims to develop robust "network risk assessment tools" capable of generating personalized surgical trajectories and real-time intraoperative updates [149]. Along with multidimensional technological innovations and improved clinical translation, these data-driven models are expected to ultimately optimize the delicate balance between maximal oncological control and the preservation of global neurocognitive function [150].
Summary
Preserving neural functional networks during brain tumor resection embodies a "functional prognosis priority" decision-making logic, seeking the optimal balance between maximal tumor removal and neural function preservation. Brain functional networks critically regulate cognition, motor function, language, and other essential abilities. Protecting these networks during extensive tumor resection effectively reduces postoperative neurological deficits, helping patients maintain self-care capabilities and social functions while significantly improving quality of life. This paradigm drives neurosurgery's transformation from "anatomy-oriented" to "functional network-oriented" approaches, ultimately achieving dual optimization of "tumor control" and "quality of life."
Multimodal technology-driven network preservation marks brain tumor surgery's transition from "anatomical resection" to a new era of "brain functional network protection." Integrating multi-source data precisely delineates tumor-network relationships and constructs topology-based surgical strategies, substantially enhancing patient survival quality. Future breakthroughs in dynamic monitoring and data fusion, alongside standardized surgical protocols, will synergistically optimize neural function preservation with tumor eradication.
Abbreviations
5-ALA: 5-aminolevulinic acid; AC: Awake Craniotomy; BCI: Brain-Computer Interface; CEN: Central Executive Network; DMN: Default Mode Network; DTI: Diffusion Tensor Imaging; fMRI: Functional Magnetic Resonance Imaging; IONM: Intraoperative Neurophysiological Monitoring; TMS: Transcranial Magnetic Stimulation; AN: Auditory Network; BDRS: Blessed Dementia Rating Scale; DAN: Dorsal Attention Network; HGG: High-Grade Gliomas; HVLT: Hopkins Verbal Learning Test; iMRI: intraoperative Magnetic Resonance Imaging; IOUS: intraoperative Ultrasonography; LGG: Low-Grade Gliomas; LN: Limbic Network; Language Network; MAS: Motor Assessment Scale; MoCA: Montreal Cognitive Assessment; nTMS: navigated Transcranial Magnetic Stimulation; SMN: Sensorimotor Network; SN: Salience Network; VAN: Ventral Attention Network; VN: Visual Network.
Declarations
Author Contributions
Mu Fengchun and Li Huaixu contributed equally as co-first authors and were responsible for conceptualization, investigation, formal analysis, visualization, and writing the original draft. Yang Ming and Jinghai Wan contributed equally as corresponding authors and were responsible for conceptualization, supervision, project administration, funding acquisition, and writing, review and editing. All authors have read and approved the final version.
Acknowledgements
The authors gratefully acknowledge the administrative and technical support from the Department of Neurosurgery, National Cancer Center / Cancer Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College.
Funding Information
This work was supported by the Innovation Project of the Cancer Hospital, Chinese Academy of Medical Sciences—Special Program for Cultivating and Recruiting Leading Talents in Medical and Health Sciences and Technologies (Grant No. 2024-I2M-3-014).
Ethics Approval and Consent to Participate
Not applicable. This study is a review article and does not involve direct experimentation with human participants or animals.
Competing Interests
The authors declare that they have no existing or potential commercial or financial relationships that could create a conflict of interest.
Data Availability
Not applicable. No new datasets were generated or analyzed. All data discussed are derived from publicly available literature cited within the reference list.
References
[1] DADARIO N B, SUGHRUE M E. Should Neurosurgeons Try to Preserve Non-Traditional Brain Networks? A Systematic Review of the Neuroscientific Evidence [J]. Journal of personalized medicine, 2022, 12(4).https://doi.org/10.3390/jpm12040587. https://doi.org/10.3390/jpm12040587
[2] FOTIADIS P, PARKES L, DAVIS K A, et al. Structure-function coupling in macroscale human brain networks [J]. Nature reviews Neuroscience, 2024, 25(10):688-704.https://doi.org/10.1038/s41583-024-00846-6. https://doi.org/10.1038/s41583-024-00846-6
[3] KHALIGHI S, REDDY K, MIDYA A, et al. Artificial intelligence in neuro-oncology:advances and challenges in brain tumor diagnosis, prognosis, and precision treatment [J]. NPJ precision oncology, 2024, 8(1):80.https://doi.org/10.1038/s41698-024-00575-0. https://doi.org/10.1038/s41698-024-00575-0
[4] ZEINELDIN R A, KARAR M E, BURGERT O, et al. NeuroIGN:Explainable Multimodal Image-Guided System for Precise Brain Tumor Surgery [J]. Journal of medical systems, 2024, 48(1):25.https://doi.org/10.1007/s10916-024-02037-3. https://doi.org/10.1007/s10916-024-02037-3
[5] QIN J, XU D, ZHANG H, et al. BTSegDiff:Brain tumor segmentation based on multimodal MRI Dynamically guided diffusion probability model [J]. Computers in biology and medicine, 2025, 186:109694.https://doi.org/10.1016/j.compbiomed.2025.109694. https://doi.org/10.1016/j.compbiomed.2025.109694
[6] SALVALAGGIO A, PINI L, BERTOLDO A, et al. Glioblastoma and brain connectivity:the need for a paradigm shift [J]. The Lancet Neurology, 2024, 23(7):740-8.https://doi.org/10.1016/s1474-4422(24)00160-1. https://doi.org/10.1016/s1474-4422(24)00160-1
[7] MAGNANI M, RUSTICI A, ZOLI M, et al. Connectome-Based Neurosurgery in Primary Intra-Axial Neoplasms:Beyond the Traditional Modular Conception of Brain Architecture for the Preservation of Major Neurological Domains and Higher-Order Cognitive Functions [J]. Life (Basel, Switzerland), 2024, 14(1).https://doi.org/10.3390/life14010136. https://doi.org/10.3390/life14010136
[8] VAN DEN HEUVEL M P, HULSHOFF POL H E. Exploring the brain network:a review on resting-state fMRI functional connectivity [J]. European neuropsychopharmacology :the journal of the European College of Neuropsychopharmacology, 2010, 20(8):519-34.https://doi.org/10.1016/j.euroneuro.2010.03.008. https://doi.org/10.1016/j.euroneuro.2010.03.008
[9] YAO Z, HU B, XIE Y, et al. A review of structural and functional brain networks:small world and atlas [J]. Brain informatics, 2015, 2(1):45-52.https://doi.org/10.1007/s40708-015-0009-z. https://doi.org/10.1007/s40708-015-0009-z
[11] PANG J C, AQUINO K M, OLDEHINKEL M, et al. Geometric constraints on human brain function [J]. Nature, 2023, 618(7965):566-74.https://doi.org/10.1038/s41586-023-06098-1. https://doi.org/10.1038/s41586-023-06098-1
[12] LIAO X, VASILAKOS A V, HE Y. Small-world human brain networks:Perspectives and challenges [J]. Neuroscience and biobehavioral reviews, 2017, 77:286-300.https://doi.org/10.1016/j.neubiorev.2017.03.018. https://doi.org/10.1016/j.neubiorev.2017.03.018
[13] PARK H J, FRISTON K. Structural and functional brain networks:from connections to cognition [J]. Science (New York, NY), 2013, 342(6158):1238411.https://doi.org/10.1126/science.1238411. https://doi.org/10.1126/science.1238411
[14] BISWAL B B, UDDIN L Q. The history and future of resting-state functional magnetic resonance imaging [J]. Nature, 2025, 641(8065):1121-31.https://doi.org/10.1038/s41586-025-08953-9. https://doi.org/10.1038/s41586-025-08953-9
[15] LAKHANI D A, SABSEVITZ D S, CHAICHANA K L, et al. Current State of Functional MRI in the Presurgical Planning of Brain Tumors [J]. Radiology Imaging cancer, 2023, 5(6):e230078.https://doi.org/10.1148/rycan.230078. https://doi.org/10.1148/rycan.230078
[16] GAO W. A hierarchical model of early brain functional network development [J]. Trends in cognitive sciences, 2025, 29(9):855-68.https://doi.org/10.1016/j.tics.2025.04.001. https://doi.org/10.1016/j.tics.2025.04.001
[17] KULKARNI S, BASSETT D S. Toward Principles of Brain Network Organization and Function [J]. Annual review of biophysics, 2025, 54(1):353-78.https://doi.org/10.1146/annurev-biophys-030722-110624. https://doi.org/10.1146/annurev-biophys-030722-110624
[18] VAN ES M W J, HIGGINS C, GOHIL C, et al. Large-scale cortical functional networks are organized in structured cycles [J]. Nature neuroscience, 2025, 28(10):2118-28.https://doi.org/10.1038/s41593-025-02052-8. https://doi.org/10.1038/s41593-025-02052-8
[19] YEO B T, KRIENEN F M, SEPULCRE J, et al. The organization of the human cerebral cortex estimated by intrinsic functional connectivity [J]. Journal of neurophysiology, 2011, 106(3):1125-65.https://doi.org/10.1152/jn.00338.2011. https://doi.org/10.1152/jn.00338.2011
[20] POWER J D, COHEN A L, NELSON S M, et al. Functional network organization of the human brain [J]. Neuron, 2011, 72(4):665-78.https://doi.org/10.1016/j.neuron.2011.09.006. https://doi.org/10.1016/j.neuron.2011.09.006
[21] FOX M D, SNYDER A Z, VINCENT J L, et al. The human brain is intrinsically organized into dynamic, anticorrelated functional networks [J]. Proceedings of the National Academy of Sciences of the United States of America, 2005, 102(27):9673-8.https://doi.org/10.1073/pnas.0504136102. https://doi.org/10.1073/pnas.0504136102
[22] MENON V. 20 years of the default mode network: A review and synthesis. Neuron, 2023 Aug, 111(16):2469-2487. https://doi.org/10.1016/j.neuron.2023.04.023. https://doi.org/10.1016/j.neuron.2023.04.023
[23] FEDORENKO E, IVANOVA A A, REGEV T I. The language network as a natural kind within the broader landscape of the human brain [J]. Nature reviews Neuroscience, 2024, 25(5):289-312.https://doi.org/10.1038/s41583-024-00802-4. https://doi.org/10.1038/s41583-024-00802-4
[24] ALVES P N, FORKEL S J, CORBETTA M, et al. The subcortical and neurochemical organization of the ventral and dorsal attention networks [J]. Communications biology, 2022, 5(1):1343.https://doi.org/10.1038/s42003-022-04281-0. https://doi.org/10.1038/s42003-022-04281-0
[25] YESHURUN Y, NGUYEN M, HASSON U. The default mode network:where the idiosyncratic self meets the shared social world [J]. Nature reviews Neuroscience, 2021, 22(3):181-92.https://doi.org/10.1038/s41583-020-00420-w. https://doi.org/10.1038/s41583-020-00420-w
[26] PAQUOLA C, GARBER M, FRäSSLE S, et al. The architecture of the human default mode network explored through cytoarchitecture, wiring and signal flow [J]. Nature neuroscience, 2025, 28(3):654-64.https://doi.org/10.1038/s41593-024-01868-0. https://doi.org/10.1038/s41593-024-01868-0
[27] ELORETTE C, FUJIMOTO A, STOLL F M, et al. The neural basis of resting-state fMRI functional connectivity in fronto-limbic circuits revealed by chemogenetic manipulation [J]. Nature communications, 2024, 15(1):4669.https://doi.org/10.1038/s41467-024-49140-0. https://doi.org/10.1038/s41467-024-49140-0
[28] VAFAII H, MANDINO F, DESROSIERS-GRéGOIRE G, et al. Multimodal measures of spontaneous brain activity reveal both common and divergent patterns of cortical functional organization [J]. Nature communications, 2024, 15(1):229.https://doi.org/10.1038/s41467-023-44363-z. https://doi.org/10.1038/s41467-023-44363-z
[29] MESBAH R, KOENDERS M A, VAN DER WEE N J A, et al. Association Between the Fronto-Limbic Network and Cognitive and Emotional Functioning in Individuals With Bipolar Disorder:A Systematic Review and Meta-analysis [J]. JAMA psychiatry, 2023, 80(5):432-40.https://doi.org/10.1001/jamapsychiatry.2023.0131. https://doi.org/10.1001/jamapsychiatry.2023.0131
[30] BERTOCCI M A, AFRIYIE-AGYEMANG Y, ROZOVSKY R, et al. Altered patterns of central executive, default mode and salience network activity and connectivity are associated with current and future depression risk in two independent young adult samples [J]. Molecular psychiatry, 2023, 28(3):1046-56.https://doi.org/10.1038/s41380-022-01899-8. https://doi.org/10.1038/s41380-022-01899-8
[31] BROWN J A, LEE A J, FERNHOFF K, et al. Functional network collapse in neurodegenerative disease [J]. Nature communications, 2025, 16(1):10273.https://doi.org/10.1038/s41467-025-65156-6. https://doi.org/10.1038/s41467-025-65156-6
[32] SCHUMER M C, BERTOCCI M A, ASLAM H A, et al. Patterns of Neural Network Functional Connectivity Associated With Mania/Hypomania and Depression Risk in 3 Independent Young Adult Samples [J]. JAMA psychiatry, 2024, 81(2):167-77.https://doi.org/10.1001/jamapsychiatry.2023.4150. https://doi.org/10.1001/jamapsychiatry.2023.4150
[33] LUPPI A I, SINGLETON S P, HANSEN J Y, et al. Contributions of network structure, chemoarchitecture and diagnostic categories to transitions between cognitive topographies [J]. Nature biomedical engineering, 2024, 8(9):1142-61.https://doi.org/10.1038/s41551-024-01242-2. https://doi.org/10.1038/s41551-024-01242-2
[34] MATYI M A, RADHAKRISHNAN H, OLM C A, et al. Executive dysfunction relates to salience network desegregation in behavioural variant frontotemporal dementia [J]. NeuroImage Clinical, 2025, 48:103853.https://doi.org/10.1016/j.nicl.2025.103853. https://doi.org/10.1016/j.nicl.2025.103853
[35] HART M G, ROMERO-GARCIA R, PRICE S J, et al. Global Effects of Focal Brain Tumors on Functional Complexity and Network Robustness:A Prospective Cohort Study [J]. Neurosurgery, 2019, 84(6):1201-13.https://doi.org/10.1093/neuros/nyy378. https://doi.org/10.1093/neuros/nyy378
[36] DERKS J, KULIK S D, NUMAN T, et al. Understanding Global Brain Network Alterations in Glioma Patients [J]. Brain connectivity, 2021, 11(10):865-74.https://doi.org/10.1089/brain.2020.0801. https://doi.org/10.1089/brain.2020.0801
[37] FEIGL G C, RITZ R, MORAES M, et al. Resection of malignant brain tumors in eloquent cortical areas:a new multimodal approach combining 5-aminolevulinic acid and intraoperative monitoring [J]. Journal of neurosurgery, 2010, 113(2):352-7.https://doi.org/10.3171/2009.10.JNS09447. https://doi.org/10.3171/2009.10.JNS09447
[38] MANDAL A S, BREM S, SUCKLING J. Brain network mapping and glioma pathophysiology [J]. Brain communications, 2023, 5(2):fcad040.https://doi.org/10.1093/braincomms/fcad040. https://doi.org/10.1093/braincomms/fcad040
[39] ROMERO-GARCIA R, MANDAL A S, BETHLEHEM R A I, et al. Transcriptomic and connectomic correlates of differential spatial patterning among gliomas [J]. Brain :a journal of neurology, 2023, 146(3):1200-11.https://doi.org/10.1093/brain/awac378. https://doi.org/10.1093/brain/awac378
[40] SUN Y, WANG X, ZHANG D Y, et al. Brain-wide neuronal circuit connectome of human glioblastoma [J]. Nature, 2025, 641(8061):222-31.https://doi.org/10.1038/s41586-025-08634-7. https://doi.org/10.1038/s41586-025-08634-7
[41] DOUW L, REIJNEVELD J C, MANDAL A S. Multiscale network perspectives on glioma:from tumour biology to symptoms, survival and treatment [J]. Nature reviews Neurology, 2026, 22(2):73-89.https://doi.org/10.1038/s41582-025-01171-x. https://doi.org/10.1038/s41582-025-01171-x
[42] WEI Y, LI C, CUI Z, et al. Structural connectome quantifies tumour invasion and predicts survival in glioblastoma patients [J]. Brain :a journal of neurology, 2023, 146(4):1714-27.https://doi.org/10.1093/brain/awac360. https://doi.org/10.1093/brain/awac360
[43] SHABO E, SARIKAYA-SEIWERT S, BORGER V, et al. Neurosurgery 4.0:A Scoping Review of Current Trends and Challenges in Specialized Smart Hospitals [J]. Cureus, 2025, 17(9):e92673.https://doi.org/10.7759/cureus.92673. https://doi.org/10.7759/cureus.92673
[44] SUN C, ZHANG J, BU L, et al. A speech fluency brain network derived from gliomas [J]. Brain communications, 2024, 6(3):fcae153.https://doi.org/10.1093/braincomms/fcae153. https://doi.org/10.1093/braincomms/fcae153
[45] WU Z, HU G, CAO B, et al. Non-traditional cognitive brain network involvement in insulo-Sylvian gliomas:a case series study and clinical experience using Quicktome [J]. Chin Neurosurg J, 2023, 9(1):16.https://doi.org/10.1186/s41016-023-00325-4. https://doi.org/10.1186/s41016-023-00325-4
[46] KRISHNA S, CHOUDHURY A, KEOUGH M B, et al. Glioblastoma remodelling of human neural circuits decreases survival [J]. Nature, 2023, 617(7961):599-607.https://doi.org/10.1038/s41586-023-06036-1. https://doi.org/10.1038/s41586-023-06036-1
[47] TAYLOR K R, BARRON T, HUI A, et al. Glioma synapses recruit mechanisms of adaptive plasticity [J]. Nature, 2023, 623(7986):366-74.https://doi.org/10.1038/s41586-023-06678-1. https://doi.org/10.1038/s41586-023-06678-1
[48] WANG Y, WANG Y, BAO H, et al. Mechanisms and therapeutic implications of glioma-neuron interactions [J]. Cancer letters, 2025, 629:217884.https://doi.org/10.1016/j.canlet.2025.217884. https://doi.org/10.1016/j.canlet.2025.217884
[49] EL OUADIH Y, PEREIRA B, BIAU J, et al. DTI Abnormalities Related to Glioblastoma:A Prospective Comparative Study with Metastasis and Healthy Subjects [J]. Current oncology (Toronto, Ont), 2022, 29(4):2823-34.https://doi.org/10.3390/curroncol29040230. https://doi.org/10.3390/curroncol29040230
[50] MORELL A A, EICHBERG D G, SHAH A H, et al. Using machine learning to evaluate large-scale brain networks in patients with brain tumors:Traditional and non-traditional eloquent areas [J]. Neurooncol Adv, 2022, 4(1):vdac142.https://doi.org/10.1093/noajnl/vdac142. https://doi.org/10.1093/noajnl/vdac142
[51] MEYER J, YU K, LUNA-FIGUEROA E, et al. Glioblastoma disrupts cortical network activity at multiple spatial and temporal scales [J]. Nature communications, 2024, 15(1):4503.https://doi.org/10.1038/s41467-024-48757-5. https://doi.org/10.1038/s41467-024-48757-5
[52] NEJO T, KRISHNA S, YAMAMICHI A, et al. Glioma-neuronal circuit remodeling induces regional immunosuppression [J]. Nature communications, 2025, 16(1):4770.https://doi.org/10.1038/s41467-025-60074-z. https://doi.org/10.1038/s41467-025-60074-z
[53] DUFFAU H. The challenge to remove diffuse low-grade gliomas while preserving brain functions [J]. Acta Neurochir (Wien), 2012, 154(4):569-74.https://doi.org/10.1007/s00701-012-1275-7. https://doi.org/10.1007/s00701-012-1275-7
[54] GERRITSEN J K W, KARSCHNIA P, BELLO L, et al. A comprehensive framework for glioma surgery by the PIONEER Consortium and RANO resect group, part 2:perioperative recommendations for neurological, language, functional, and quality-of-life assessment [J]. The Lancet Oncology, 2026, 27(1):e24-e32.https://doi.org/10.1016/s1470-2045(25)00532-7. https://doi.org/10.1016/s1470-2045(25)00532-7
[55] YOUNG J S, LEE A T, CHANG E F. A Review of Cortical and Subcortical Stimulation Mapping for Language [J]. Neurosurgery, 2021, 89(3):331-42.https://doi.org/10.1093/neuros/nyaa436. https://doi.org/10.1093/neuros/nyaa436
[56] GERRITSEN J K W, KARSCHNIA P, BELLO L, et al. A comprehensive framework for glioma surgery by the PIONEER Consortium and RANO resect group, part 1:intraoperative recommendations for mapping, monitoring, and decision making [J]. The Lancet Oncology, 2026, 27(1):e11-e23.https://doi.org/10.1016/s1470-2045(25)00531-5. https://doi.org/10.1016/s1470-2045(25)00531-5
[57] SAMUEL N, VETKAS A, PANCHOLI A, et al. A Network-Based Approach to Glioma Surgery:Insights from Functional Neurosurgery [J]. Cancers (Basel), 2021, 13(23).https://doi.org/10.3390/cancers13236127. https://doi.org/10.3390/cancers13236127
[58] FALCó-ROGET J, CACCIOLA A, SAMBATARO F, et al. Functional and structural reorganization in brain tumors:a machine learning approach using desynchronized functional oscillations [J]. Communications biology, 2024, 7(1):419.https://doi.org/10.1038/s42003-024-06119-3. https://doi.org/10.1038/s42003-024-06119-3
[59] BOU DARGHAM T, WINTER S F, BATICH K, et al. Neurocognitive outcomes in patients with brain metastases:a systematic review [J]. The Lancet Oncology, 2025, 26(12):e671-e82.https://doi.org/10.1016/s1470-2045(25)00525-x. https://doi.org/10.1016/s1470-2045(25)00525-x
[60] ROMERO-GARCIA R, SUCKLING J, OWEN M, et al. Memory recovery in relation to default mode network impairment and neurite density during brain tumor treatment [J]. Journal of neurosurgery, 2022, 136(2):358-68.https://doi.org/10.3171/2021.1.Jns203959. https://doi.org/10.3171/2021.1.Jns203959
[61] MUELLER S, WANG D, FOX M D, et al. Individual variability in functional connectivity architecture of the human brain [J]. Neuron, 2013, 77(3):586-95.https://doi.org/10.1016/j.neuron.2012.12.028. https://doi.org/10.1016/j.neuron.2012.12.028
[62] CUI W, WANG Y, REN J, et al. Personalized fMRI Delineates Functional Regions Preserved within Brain Tumors [J]. Annals of neurology, 2022, 91(3):353-66.https://doi.org/10.1002/ana.26303. https://doi.org/10.1002/ana.26303
[63] PAIVA W S, FONOFF E T, DOS SANTOS SILVA R P, et al. Preoperative Cortical Mapping for Brain Tumor Surgery Using Navigated Transcranial Stimulation:Analysis of Accuracy [J]. Brain sciences, 2024, 14(9).https://doi.org/10.3390/brainsci14090867. https://doi.org/10.3390/brainsci14090867
[64] SINHA S, KALYAL N, GALLAGHER M J, et al. Impact of Preoperative Mapping and Intraoperative Neuromonitoring in Minimally Invasive Parafascicular Surgery for Deep-Seated Lesions [J]. World neurosurgery, 2024, 181:e1019-e37.https://doi.org/10.1016/j.wneu.2023.11.030. https://doi.org/10.1016/j.wneu.2023.11.030
[65] BAIG MIRZA A, VASTANI A, SUVARNA R, et al. Preoperative and intraoperative neuromonitoring and mapping techniques impact oncological and functional outcomes in supratentorial function-eloquent brain tumours:a systematic review and meta-analysis [J]. EClinicalMedicine, 2025, 80:103055.https://doi.org/10.1016/j.eclinm.2024.103055. https://doi.org/10.1016/j.eclinm.2024.103055
[66] SMOLDERS L, DE BAENE W, GEHRING K, et al. Presurgical structural connectivity predicts postsurgical cognitive impairment in glioma patients [J]. Brain communications, 2025, 7(5):fcaf346.https://doi.org/10.1093/braincomms/fcaf346. https://doi.org/10.1093/braincomms/fcaf346
[67] YUAN B, ZHANG N, YAN J, et al. Resting-state functional connectivity predicts individual language impairment of patients with left hemispheric gliomas involving language network [J]. NeuroImage Clinical, 2019, 24:102023.https://doi.org/10.1016/j.nicl.2019.102023. https://doi.org/10.1016/j.nicl.2019.102023
[68] AYDOGAN D B, SOUZA V H, MATSUDA R H, et al. Real-Time Tractography-Assisted Neuronavigation for Transcranial Magnetic Stimulation [J]. Human brain mapping, 2025, 46(1):e70122.https://doi.org/10.1002/hbm.70122. https://doi.org/10.1002/hbm.70122
[69] MUIR M T, NOLL K, PRINSLOO S, et al. Preoperative Brain Mapping Predicts Language Outcomes After Eloquent Tumor Resection [J]. Human brain mapping, 2025, 46(15):e70340.https://doi.org/10.1002/hbm.70340. https://doi.org/10.1002/hbm.70340
[70] SOMMER B, GRUMMICH P, HAMER H, et al. Frameless stereotactic functional neuronavigation combined with intraoperative magnetic resonance imaging as a strategy in highly eloquent located tumors causing epilepsy [J]. Stereotactic and functional neurosurgery, 2014, 92(1):59-67.https://doi.org/10.1159/000355216. https://doi.org/10.1159/000355216
[71] NINATTI G, SOLLINI M, BONO B, et al. Preoperative [11C]methionine PET to personalize treatment decisions in patients with lower-grade gliomas [J]. Neuro-oncology, 2022, 24(9):1546-56.https://doi.org/10.1093/neuonc/noac040. https://doi.org/10.1093/neuonc/noac040
[72] FREY D, SCHILT S, STRACK V, et al. Navigated transcranial magnetic stimulation improves the treatment outcome in patients with brain tumors in motor eloquent locations [J]. Neuro-oncology, 2014, 16(10):1365-72.https://doi.org/10.1093/neuonc/nou110. https://doi.org/10.1093/neuonc/nou110
[73] PICHT T, SCHMIDT S, BRANDT S, et al. Preoperative functional mapping for rolandic brain tumor surgery:comparison of navigated transcranial magnetic stimulation to direct cortical stimulation [J]. Neurosurgery, 2011, 69(3):581-8; discussion 8.https://doi.org/10.1227/NEU.0b013e3182181b89. https://doi.org/10.1227/NEU.0b013e3182181b89
[74] LEONE A, CARBONE F, SPETZGER U, et al. Preoperative mapping techniques for brain tumor surgery:a systematic review [J]. Front Oncol, 2024, 14:1481430.https://doi.org/10.3389/fonc.2024.1481430. https://doi.org/10.3389/fonc.2024.1481430
[75] RAFFA G, QUATTROPANI M C, GERMANò A. When imaging meets neurophysiology:the value of navigated transcranial magnetic stimulation for preoperative neurophysiological mapping prior to brain tumor surgery [J]. Neurosurg Focus, 2019, 47(6):E10.https://doi.org/10.3171/2019.9.Focus19640. https://doi.org/10.3171/2019.9.Focus19640
[76] PICHT T, MULARSKI S, KUEHN B, et al. Navigated transcranial magnetic stimulation for preoperative functional diagnostics in brain tumor surgery [J]. Neurosurgery, 2009, 65(6 Suppl):93-8; discussion 8-9.https://doi.org/10.1227/01.Neu.0000348009.22750.59. https://doi.org/10.1227/01.Neu.0000348009.22750.59
[77] INDHARTY R S, JAPARDI I, IRINA R S, et al. Comparison of direct cortical stimulation and transcranial magnetic stimulation in brain tumor surgery:systematic review and meta analyses [J]. J Neurooncol, 2023, 163(3):505-14.https://doi.org/10.1007/s11060-023-04378-4. https://doi.org/10.1007/s11060-023-04378-4
[78] HADDAD A F, YOUNG J S, BERGER M S, et al. Preoperative Applications of Navigated Transcranial Magnetic Stimulation [J]. Frontiers in neurology, 2020, 11:628903.https://doi.org/10.3389/fneur.2020.628903. https://doi.org/10.3389/fneur.2020.628903
[79] MEYERS C A, BROWN P D. Role and relevance of neurocognitive assessment in clinical trials of patients with CNS tumors [J]. Journal of clinical oncology :official journal of the American Society of Clinical Oncology, 2006, 24(8):1305-9.https://doi.org/10.1200/jco.2005.04.6086. https://doi.org/10.1200/jco.2005.04.6086
[80] TAPHOORN M J, KLEIN M. Cognitive deficits in adult patients with brain tumours [J]. The Lancet Neurology, 2004, 3(3):159-68.https://doi.org/10.1016/s1474-4422(04)00680-5. https://doi.org/10.1016/s1474-4422(04)00680-5
[81] PARSONS M W, DIETRICH J. Assessment and Management of Cognitive Symptoms in Patients With Brain Tumors [J]. 2021, (41):e90-e9.https://doi.org/10.1200/edbk_320813. https://doi.org/10.1200/edbk_320813
[82] NASREDDINE Z S, PHILLIPS N A, BéDIRIAN V, et al. The Montreal Cognitive Assessment, MoCA:a brief screening tool for mild cognitive impairment [J]. Journal of the American Geriatrics Society, 2005, 53(4):695-9.https://doi.org/10.1111/j.1532-5415.2005.53221.x. https://doi.org/10.1111/j.1532-5415.2005.53221.x
[83] JAMMULA V, ROGERS J L, VERA E, et al. The Montreal Cognitive Assessment (MoCA) in neuro-oncology:A pilot study of feasibility and utility in telehealth and in-person clinical assessments [J]. Neuro-oncology practice, 2022, 9(5):429-40.https://doi.org/10.1093/nop/npac038. https://doi.org/10.1093/nop/npac038
[84] CARR J H, SHEPHERD R B, NORDHOLM L, et al. Investigation of a new motor assessment scale for stroke patients [J]. Physical therapy, 1985, 65(2):175-80.https://doi.org/10.1093/ptj/65.2.175. https://doi.org/10.1093/ptj/65.2.175
[85] NOLL K R, ZIU M, WEINBERG J S, et al. Neurocognitive functioning in patients with glioma of the left and right temporal lobes [J]. Journal of neuro-oncology, 2016, 128(2):323-31.https://doi.org/10.1007/s11060-016-2114-0. https://doi.org/10.1007/s11060-016-2114-0
[86] ISLAM N, HASHEM R, GAD M, et al. Accuracy of the Montreal Cognitive Assessment tool for detecting mild cognitive impairment:A systematic review and meta-analysis [J]. Alzheimers Dement, 2023, 19(7):3235-43.https://doi.org/10.1002/alz.13040. https://doi.org/10.1002/alz.13040
[87] TOMASINO B, GUARRACINO I, IUS T, et al. Continuous Real-Time Neuropsychological Testing during Resection Phase in Left and Right Prefrontal Brain Tumors [J]. Curr Oncol, 2023, 30(2):2007-20.https://doi.org/10.3390/curroncol30020156. https://doi.org/10.3390/curroncol30020156
[88] CARPENTIERI S C, WABER D P, POMEROY S L, et al. Neuropsychological functioning after surgery in children treated for brain tumor [J]. Neurosurgery, 2003, 52(6):1348-56; discussion 56-7.https://doi.org/10.1227/01.neu.0000064804.00766.62. https://doi.org/10.1227/01.neu.0000064804.00766.62
[89] TAYLOR J W, WEYER-JAMORA C, HERVEY-JUMPER S. Molecularly determining cognition in glioma:New insights as the plot thickens [J]. Neuro-oncology, 2022, 24(10):1671-2.https://doi.org/10.1093/neuonc/noac149. https://doi.org/10.1093/neuonc/noac149
[90] VAN KESSEL E, BERENDSEN S, BAUMFALK A E, et al. Tumor-related molecular determinants of neurocognitive deficits in patients with diffuse glioma [J]. Neuro-oncology, 2022, 24(10):1660-70.https://doi.org/10.1093/neuonc/noac036. https://doi.org/10.1093/neuonc/noac036
[91] WACH J, VYCHOPEN M, BASARAN A E, et al. Efficacy and safety of intraoperative MRI in glioma surgery:a systematic review and meta-analysis of prospective randomized controlled trials [J]. Journal of neurosurgery, 2025, 142(5):1319-30.https://doi.org/10.3171/2024.7.Jns241102. https://doi.org/10.3171/2024.7.Jns241102
[92] SENFT C, BINK A, FRANZ K, et al. Intraoperative MRI guidance and extent of resection in glioma surgery:a randomised, controlled trial [J]. The Lancet Oncology, 2011, 12(11):997-1003.https://doi.org/10.1016/s1470-2045(11)70196-6. https://doi.org/10.1016/s1470-2045(11)70196-6
[93] DUFFAU H. Lessons from brain mapping in surgery for low-grade glioma:insights into associations between tumour and brain plasticity [J]. The Lancet Neurology, 2005, 4(8):476-86.https://doi.org/10.1016/s1474-4422(05)70140-x. https://doi.org/10.1016/s1474-4422(05)70140-x
[94] KöHLERT K, JäHNE K, SAUR D, et al. Neurophysiological examination combined with functional intraoperative navigation using TMS in patients with brain tumor near the central region-a pilot study [J]. Acta Neurochir (Wien), 2019, 161(9):1853-64.https://doi.org/10.1007/s00701-019-04004-1. https://doi.org/10.1007/s00701-019-04004-1
[95] DE WITT HAMER P C, ROBLES S G, ZWINDERMAN A H, et al. Impact of intraoperative stimulation brain mapping on glioma surgery outcome:a meta-analysis [J]. Journal of clinical oncology :official journal of the American Society of Clinical Oncology, 2012, 30(20):2559-65.https://doi.org/10.1200/jco.2011.38.4818. https://doi.org/10.1200/jco.2011.38.4818
[96] LOWENSTEIN P R, CASTRO M G. Pushing the Limits of Glioma Resection Using Electrophysiologic Brain Mapping [J]. 2012, 30(20):2437-40.https://doi.org/10.1200/jco.2011.40.6959. https://doi.org/10.1200/jco.2011.40.6959
[97] MACDONALD D B, SKINNER S, SHILS J, et al. Intraoperative motor evoked potential monitoring - a position statement by the American Society of Neurophysiological Monitoring [J]. Clinical neurophysiology :official journal of the International Federation of Clinical Neurophysiology, 2013, 124(12):2291-316.https://doi.org/10.1016/j.clinph.2013.07.025. https://doi.org/10.1016/j.clinph.2013.07.025
[98] LI T, BAI H, WANG G, et al. Glioma localization and excision using direct electrical stimulation for language mapping during awake surgery [J]. Experimental and therapeutic medicine, 2015, 9(5):1962-6.https://doi.org/10.3892/etm.2015.2359. https://doi.org/10.3892/etm.2015.2359
[99] FATEMI P, ZHANG M, MILLER K J, et al. How Intraoperative Tools and Techniques Have Changed the Approach to Brain Tumor Surgery [J]. Curr Oncol Rep, 2018, 20(11):89.https://doi.org/10.1007/s11912-018-0723-9. https://doi.org/10.1007/s11912-018-0723-9
[100] BRELL M, IBáñEZ J, CARAL L, et al. Factors influencing surgical complications of intra-axial brain tumours [J]. Acta Neurochir (Wien), 2000, 142(7):739-50.https://doi.org/10.1007/s007010070088. https://doi.org/10.1007/s007010070088
[101] DUFFAU H, LOPES M, ARTHUIS F, et al. Contribution of intraoperative electrical stimulations in surgery of low grade gliomas:a comparative study between two series without (1985-96) and with (1996-2003) functional mapping in the same institution [J]. J Neurol Neurosurg Psychiatry, 2005, 76(6):845-51.https://doi.org/10.1136/jnnp.2004.048520. https://doi.org/10.1136/jnnp.2004.048520
[102] KAMP M A, FINK L, FORSTER M T, et al. In-patient neurosurgical tumor treatments for malignant glioma patients in Germany [J]. J Neurooncol, 2024, 170(3):527-42.https://doi.org/10.1007/s11060-024-04784-2. https://doi.org/10.1007/s11060-024-04784-2
[103] BAYER S, MAIER A, OSTERMEIER M, et al. Intraoperative Imaging Modalities and Compensation for Brain Shift in Tumor Resection Surgery [J]. International journal of biomedical imaging, 2017, 2017:6028645.https://doi.org/10.1155/2017/6028645. https://doi.org/10.1155/2017/6028645
[104] NARASIMHAN S, WEIS J A, LUO M, et al. Accounting for intraoperative brain shift ascribable to cavity collapse during intracranial tumor resection [J]. Journal of medical imaging (Bellingham, Wash), 2020, 7(3):031506.https://doi.org/10.1117/1.Jmi.7.3.031506. https://doi.org/10.1117/1.Jmi.7.3.031506
[105] FOUNTAIN D M, BRYANT A, BARONE D G, et al. Intraoperative imaging technology to maximise extent of resection for glioma:a network meta-analysis [J]. The Cochrane database of systematic reviews, 2021, 1(1):Cd013630.https://doi.org/10.1002/14651858.CD013630.pub2. https://doi.org/10.1002/14651858.CD013630.pub2
[106] GIUSSANI C, TREZZA A, RICCIUTI V, et al. Intraoperative MRI versus intraoperative ultrasound in pediatric brain tumor surgery:is expensive better than cheap? A review of the literature [J]. Childs Nerv Syst, 2022, 38(8):1445-54.https://doi.org/10.1007/s00381-022-05545-0. https://doi.org/10.1007/s00381-022-05545-0
[107] XIE X, SHEN C, ZHANG X, et al. Rapid intraoperative multi-molecular diagnosis of glioma with ultrasound radio frequency signals and deep learning [J]. EBioMedicine, 2023, 98:104899.https://doi.org/10.1016/j.ebiom.2023.104899. https://doi.org/10.1016/j.ebiom.2023.104899
[108] FERGUSON J, HWANG S W, TATARYN Z, et al. Neuromonitoring changes in pediatric spinal deformity surgery:a single-institution experience [J]. J Neurosurg Pediatr, 2014, 13(3):247-54.https://doi.org/10.3171/2013.12.Peds13188. https://doi.org/10.3171/2013.12.Peds13188
[109] SAMDANI A F, BENNETT J T, AMES R J, et al. Reversible Intraoperative Neurophysiologic Monitoring Alerts in Patients Undergoing Arthrodesis for Adolescent Idiopathic Scoliosis:What Are the Outcomes of Surgery? [J]. J Bone Joint Surg Am, 2016, 98(17):1478-83.https://doi.org/10.2106/jbjs.15.01379. https://doi.org/10.2106/jbjs.15.01379
[110] KARSCHNIA P, GERRITSEN J K W, TESKE N, et al. The oncological role of resection in newly diagnosed diffuse adult-type glioma defined by the WHO 2021 classification:a Review by the RANO resect group [J]. The Lancet Oncology, 2024, 25(9):e404-e19.https://doi.org/10.1016/s1470-2045(24)00130-x. https://doi.org/10.1016/s1470-2045(24)00130-x
[111] HERBET G, DUFFAU H. Revisiting the Functional Anatomy of the Human Brain:Toward a Meta-Networking Theory of Cerebral Functions [J]. Physiological reviews, 2020, 100(3):1181-228.https://doi.org/10.1152/physrev.00033.2019. https://doi.org/10.1152/physrev.00033.2019
[112] CHOWDHURY T, SINGH G P, ZEILER F A, et al. Anesthesia for Awake Craniotomy for Brain Tumors in an Intraoperative MRI Suite:Challenges and Evidence [J]. Frontiers in oncology, 2018, 8:519.https://doi.org/10.3389/fonc.2018.00519. https://doi.org/10.3389/fonc.2018.00519
[113] THUET E D, WINSCHER J C, PADBERG A M, et al. Validity and reliability of intraoperative monitoring in pediatric spinal deformity surgery:a 23-year experience of 3436 surgical cases [J]. Spine (Phila Pa 1976), 2010, 35(20):1880-6.https://doi.org/10.1097/BRS.0b013e3181e53434. https://doi.org/10.1097/BRS.0b013e3181e53434
[114] DE ZWART B, RUIS C. An update on tests used for intraoperative monitoring of cognition during awake craniotomy [J]. Acta neurochirurgica, 2024, 166(1):204.https://doi.org/10.1007/s00701-024-06062-6. https://doi.org/10.1007/s00701-024-06062-6
[115] TOMASELLI A, LUCA A, FERINI G, et al. Cognitive Profiles and Determinants of Eligibility for Awake Surgery in Non-Dominant Hemisphere Gliomas:A Narrative Review [J]. Brain and behavior, 2025, 15(6):e70604.https://doi.org/10.1002/brb3.70604. https://doi.org/10.1002/brb3.70604
[116] LANDERS M J F, BROUWERS B, WEGGELAAR A M, et al. Monitoring of Executive Functions During Awake Glioma Surgery:A Standardized Multicenter Protocol [J]. Neurosurgery practice, 2025, 6(3):e000152.https://doi.org/10.1227/neuprac.0000000000000152. https://doi.org/10.1227/neuprac.0000000000000152
[117] MCCRACKEN D J, SCHUPPER A J, LAKOMKIN N, et al. Turning on the light for brain tumor surgery:A 5-aminolevulinic acid story [J]. Neuro-oncology, 2022, 24(Suppl 6):S52-s61.https://doi.org/10.1093/neuonc/noac191. https://doi.org/10.1093/neuonc/noac191
[118] WELLER M, VAN DEN BENT M, PREUSSER M, et al. EANO guidelines on the diagnosis and treatment of diffuse gliomas of adulthood [J]. Nature reviews Clinical oncology, 2021, 18(3):170-86.https://doi.org/10.1038/s41571-020-00447-z. https://doi.org/10.1038/s41571-020-00447-z
[119] STUMMER W, PICHLMEIER U, MEINEL T, et al. Fluorescence-guided surgery with 5-aminolevulinic acid for resection of malignant glioma:a randomised controlled multicentre phase III trial [J]. The Lancet Oncology, 2006, 7(5):392-401.https://doi.org/10.1016/s1470-2045(06)70665-9. https://doi.org/10.1016/s1470-2045(06)70665-9
[120] WANG X, ZUO Z, YU S, et al. Long-term clinical prognosis of patients with gliomas infiltrating corticospinal tract on DTI tractography [J]. Chinese neurosurgical journal, 2025, 11(1):26.https://doi.org/10.1186/s41016-025-00412-8. https://doi.org/10.1186/s41016-025-00412-8
[121] BEN DOR N, SIGHINOLFI G, ROSETTI V, et al. Diffusion Tensor Imaging Biomarkers to Predict Neurological Outcomes in Brain Surgery:A Systematic Review [J]. Life (Basel, Switzerland), 2026, 16(1).https://doi.org/10.3390/life16010115. https://doi.org/10.3390/life16010115
[122] FRIEDRICH M, FILSS C P, LOHMANN P, et al. Structural connectome-based predictive modeling of cognitive deficits in treated glioma patients [J]. Neuro-oncology advances, 2024, 6(1):vdad151.https://doi.org/10.1093/noajnl/vdad151. https://doi.org/10.1093/noajnl/vdad151
[123] KAWAHIRA K, SHIMODOZONO M, OGATA A, et al. Addition of intensive repetition of facilitation exercise to multidisciplinary rehabilitation promotes motor functional recovery of the hemiplegic lower limb [J]. J Rehabil Med, 2004, 36(4):159-64.https://doi.org/10.1080/16501970410029753. https://doi.org/10.1080/16501970410029753
[124] DONNELLY B M, STARK K G, PERSAUD C J, et al. Optimizing post-acute care inpatient rehabilitation for patients with brain metastasis:A systematic review of functional outcomes [J]. Supportive care in cancer :official journal of the Multinational Association of Supportive Care in Cancer, 2025, 33(5):418.https://doi.org/10.1007/s00520-025-09468-9. https://doi.org/10.1007/s00520-025-09468-9
[125] MCLARNEY M, FERGESTROM N, ZHENG J, et al. Rehabilitation after brain tumor resection:A national study of postacute care service use through insurance claims data [J]. Pm r, 2024, 16(5):441-8.https://doi.org/10.1002/pmrj.13117. https://doi.org/10.1002/pmrj.13117
[126] MARCINIAK C M, SLIWA J A, HEINEMANN A W, et al. Functional outcomes of persons with brain tumors after inpatient rehabilitation [J]. Arch Phys Med Rehabil, 2001, 82(4):457-63.https://doi.org/10.1053/apmr.2001.21862. https://doi.org/10.1053/apmr.2001.21862
[127] YUAN Y, GU Q, ZHU M, et al. Frailty-originated early rehabilitation reduces postoperative delirium in brain tumor patients:Results from a prospective randomized study [J]. Asia-Pacific journal of oncology nursing, 2023, 10(8):100263.https://doi.org/10.1016/j.apjon.2023.100263. https://doi.org/10.1016/j.apjon.2023.100263
[128] ENGELHARDT M, SCHNEIDER H, REUTHER J, et al. Low-frequency repetitive transcranial magnetic stimulation in patients with motor deficits after brain tumor resection:a randomized, double-blind, sham-controlled trial [J]. Frontiers in oncology, 2024, 14:1368924.https://doi.org/10.3389/fonc.2024.1368924. https://doi.org/10.3389/fonc.2024.1368924
[129] POOLOGAINDRAN A, PROFYRIS C, YOUNG I M, et al. Interventional neurorehabilitation for promoting functional recovery post-craniotomy:a proof-of-concept [J]. Sci Rep, 2022, 12(1):3039.https://doi.org/10.1038/s41598-022-06766-8. https://doi.org/10.1038/s41598-022-06766-8
[130] ENGELHARDT M, GRITTNER U, KRIEG S, et al. Preconditioning of the motor network with repetitive navigated transcranial magnetic stimulation (rnTMS) to improve oncological and functional outcome in brain tumor surgery:a study protocol for a randomized, sham-controlled, triple-blind clinical trial [J]. Trials, 2023, 24(1):638.https://doi.org/10.1186/s13063-023-07640-2. https://doi.org/10.1186/s13063-023-07640-2
[131] EINSTEIN E H, DADARIO N B, KHILJI H, et al. Transcranial magnetic stimulation for post-operative neurorehabilitation in neuro-oncology:a review of the literature and future directions [J]. J Neurooncol, 2022, 157(3):435-43.https://doi.org/10.1007/s11060-022-03987-9. https://doi.org/10.1007/s11060-022-03987-9
[132] MA J, RUI Z, ZOU Y, et al. Neurosurgical and BCI approaches to visual rehabilitation in occipital lobe tumor patients [J]. Heliyon, 2024, 10(23):e39072.https://doi.org/10.1016/j.heliyon.2024.e39072. https://doi.org/10.1016/j.heliyon.2024.e39072
[133] YOUNG M J, LIN D J, HOCHBERG L R. Brain-Computer Interfaces in Neurorecovery and Neurorehabilitation [J]. Seminars in neurology, 2021, 41(2):206-16.https://doi.org/10.1055/s-0041-1725137. https://doi.org/10.1055/s-0041-1725137
[134] CARINO-ESCOBAR R I, RODRIGUEZ-BARRAGAN M A, CARRILLO-MORA P, et al. Brain-computer interface as complementary therapy for hemiparesis in an astrocytoma patient [J]. Neurol Sci, 2022, 43(4):2879-81.https://doi.org/10.1007/s10072-022-05924-0. https://doi.org/10.1007/s10072-022-05924-0
[135] CHAUDHARY U, BIRBAUMER N, RAMOS-MURGUIALDAY A. Brain-computer interfaces for communication and rehabilitation [J]. Nature reviews Neurology, 2016, 12(9):513-25.https://doi.org/10.1038/nrneurol.2016.113. https://doi.org/10.1038/nrneurol.2016.113
[136] WANG N, TU W J. Editorial:Brain-computer interfaces in neurological disorders:expanding horizons for diagnosis, treatment, and rehabilitation [J]. Frontiers in neuroscience, 2024, 18:1526723.https://doi.org/10.3389/fnins.2024.1526723. https://doi.org/10.3389/fnins.2024.1526723
[137] EKERT J O, GOYAL A, YOUNG J S, et al. Interventional neurorehabilitation for glioma patients:A systematic review [J]. Neuro-oncology practice, 2024, 11(6):679-90.https://doi.org/10.1093/nop/npae066. https://doi.org/10.1093/nop/npae066
[138] DE ROECK L, COLAES R, DUPONT P, et al. Increased functional network segregation in glioma patients posttherapy:A neurological compensatory response or catastrophe for cognition? [J]. Network neuroscience (Cambridge, Mass), 2025, 9(2):743-60.https://doi.org/10.1162/netn_a_00449. https://doi.org/10.1162/netn_a_00449
[139] SAVIOLA F, ZIGIOTTO L, NOVELLO L, et al. The role of the default mode network in longitudinal functional brain reorganization of brain gliomas [J]. Brain structure & function, 2022, 227(9):2923-37.https://doi.org/10.1007/s00429-022-02490-1. https://doi.org/10.1007/s00429-022-02490-1
[140] RAMíREZ-FERRER E, AGUILERA-PENA M P, DUFFAU H. Functional and oncological outcomes after right hemisphere glioma resection in awake versus asleep patients:a systematic review and meta-analysis [J]. Neurosurgical review, 2024, 47(1):160.https://doi.org/10.1007/s10143-024-02370-8. https://doi.org/10.1007/s10143-024-02370-8
[142] PEROVNIK M, RUS T, SCHINDLBECK K A, et al. Functional brain networks in the evaluation of patients with neurodegenerative disorders [J]. Nat Rev Neurol, 2023, 19(2):73-90.https://doi.org/10.1038/s41582-022-00753-3. https://doi.org/10.1038/s41582-022-00753-3
[144] DUFFAU H. The huge plastic potential of adult brain and the role of connectomics:new insights provided by serial mappings in glioma surgery [J]. Cortex; a journal devoted to the study of the nervous system and behavior, 2014, 58:325-37.https://doi.org/10.1016/j.cortex.2013.08.005. https://doi.org/10.1016/j.cortex.2013.08.005
[145] YANG J, KUDULAITI N, CHEN Z, et al. Within and beyond the visual cortex:brain tumors induce highly sensitive plasticity of visual processing in whole-brain neural functional networks [J]. Cerebral cortex (New York, NY :1991), 2022, 32(20):4422-35.https://doi.org/10.1093/cercor/bhab492. https://doi.org/10.1093/cercor/bhab492
[146] NG S, MORITZ-GASSER S, LEMAITRE A L, et al. Multivariate mapping of low-resilient neurocognitive systems within and around low-grade gliomas [J]. Brain :a journal of neurology, 2024, 147(8):2718-31.https://doi.org/10.1093/brain/awae130. https://doi.org/10.1093/brain/awae130
[147] DUFFAU H. Brain plasticity:from pathophysiological mechanisms to therapeutic applications [J]. Journal of clinical neuroscience :official journal of the Neurosurgical Society of Australasia, 2006, 13(9):885-97.https://doi.org/10.1016/j.jocn.2005.11.045. https://doi.org/10.1016/j.jocn.2005.11.045
[148] BI W L, HOSNY A, SCHABATH M B, et al. Artificial intelligence in cancer imaging:Clinical challenges and applications [J]. CA:a cancer journal for clinicians, 2019, 69(2):127-57.https://doi.org/10.3322/caac.21552. https://doi.org/10.3322/caac.21552
[149] KICKINGEREDER P, ISENSEE F, TURSUNOVA I, et al. Automated quantitative tumour response assessment of MRI in neuro-oncology with artificial neural networks:a multicentre, retrospective study [J]. The Lancet Oncology, 2019, 20(5):728-40.https://doi.org/10.1016/s1470-2045(19)30098-1. https://doi.org/10.1016/s1470-2045(19)30098-1
[150] BOERGER T F, PAHAPILL P, BUTTS A M, et al. Large-scale brain networks and intra-axial tumor surgery:a narrative review of functional mapping techniques, critical needs, and scientific opportunities [J]. Frontiers in human neuroscience, 2023, 17:1170419.https://doi.org/10.3389/fnhum.2023.1170419. https://doi.org/10.3389/fnhum.2023.1170419
 Figures
 References
 Peer
 Information
Figure 1. From anatomical excision to network preservation: an evolving paradigm in brain tumor surgery. This figure illustrates the paradigm shift in brain tumor surgery from traditional anatomical resection to modern network-based preservation.
Figure 2. Composition and function of brain functional networks. This figure depicts the major human brain functional networks and their core functions.
Figure 3. Strategies for brain functional network preservation. This figure summarizes the multimodal strategies used pre-, intra-, and post-operatively to protect brain functional networks during tumor surgery.
[1] DADARIO N B, SUGHRUE M E. Should Neurosurgeons Try to Preserve Non-Traditional Brain Networks? A Systematic Review of the Neuroscientific Evidence [J]. Journal of personalized medicine, 2022, 12(4).https://doi.org/10.3390/jpm12040587. https://doi.org/10.3390/jpm12040587
[2] FOTIADIS P, PARKES L, DAVIS K A, et al. Structure-function coupling in macroscale human brain networks [J]. Nature reviews Neuroscience, 2024, 25(10):688-704.https://doi.org/10.1038/s41583-024-00846-6. https://doi.org/10.1038/s41583-024-00846-6
[3] KHALIGHI S, REDDY K, MIDYA A, et al. Artificial intelligence in neuro-oncology:advances and challenges in brain tumor diagnosis, prognosis, and precision treatment [J]. NPJ precision oncology, 2024, 8(1):80.https://doi.org/10.1038/s41698-024-00575-0. https://doi.org/10.1038/s41698-024-00575-0
[4] ZEINELDIN R A, KARAR M E, BURGERT O, et al. NeuroIGN:Explainable Multimodal Image-Guided System for Precise Brain Tumor Surgery [J]. Journal of medical systems, 2024, 48(1):25.https://doi.org/10.1007/s10916-024-02037-3. https://doi.org/10.1007/s10916-024-02037-3
[5] QIN J, XU D, ZHANG H, et al. BTSegDiff:Brain tumor segmentation based on multimodal MRI Dynamically guided diffusion probability model [J]. Computers in biology and medicine, 2025, 186:109694.https://doi.org/10.1016/j.compbiomed.2025.109694. https://doi.org/10.1016/j.compbiomed.2025.109694
[6] SALVALAGGIO A, PINI L, BERTOLDO A, et al. Glioblastoma and brain connectivity:the need for a paradigm shift [J]. The Lancet Neurology, 2024, 23(7):740-8.https://doi.org/10.1016/s1474-4422(24)00160-1. https://doi.org/10.1016/s1474-4422(24)00160-1
[7] MAGNANI M, RUSTICI A, ZOLI M, et al. Connectome-Based Neurosurgery in Primary Intra-Axial Neoplasms:Beyond the Traditional Modular Conception of Brain Architecture for the Preservation of Major Neurological Domains and Higher-Order Cognitive Functions [J]. Life (Basel, Switzerland), 2024, 14(1).https://doi.org/10.3390/life14010136. https://doi.org/10.3390/life14010136
[8] VAN DEN HEUVEL M P, HULSHOFF POL H E. Exploring the brain network:a review on resting-state fMRI functional connectivity [J]. European neuropsychopharmacology :the journal of the European College of Neuropsychopharmacology, 2010, 20(8):519-34.https://doi.org/10.1016/j.euroneuro.2010.03.008. https://doi.org/10.1016/j.euroneuro.2010.03.008
[9] YAO Z, HU B, XIE Y, et al. A review of structural and functional brain networks:small world and atlas [J]. Brain informatics, 2015, 2(1):45-52.https://doi.org/10.1007/s40708-015-0009-z. https://doi.org/10.1007/s40708-015-0009-z
[11] PANG J C, AQUINO K M, OLDEHINKEL M, et al. Geometric constraints on human brain function [J]. Nature, 2023, 618(7965):566-74.https://doi.org/10.1038/s41586-023-06098-1. https://doi.org/10.1038/s41586-023-06098-1
[12] LIAO X, VASILAKOS A V, HE Y. Small-world human brain networks:Perspectives and challenges [J]. Neuroscience and biobehavioral reviews, 2017, 77:286-300.https://doi.org/10.1016/j.neubiorev.2017.03.018. https://doi.org/10.1016/j.neubiorev.2017.03.018
[13] PARK H J, FRISTON K. Structural and functional brain networks:from connections to cognition [J]. Science (New York, NY), 2013, 342(6158):1238411.https://doi.org/10.1126/science.1238411. https://doi.org/10.1126/science.1238411
[14] BISWAL B B, UDDIN L Q. The history and future of resting-state functional magnetic resonance imaging [J]. Nature, 2025, 641(8065):1121-31.https://doi.org/10.1038/s41586-025-08953-9. https://doi.org/10.1038/s41586-025-08953-9
[15] LAKHANI D A, SABSEVITZ D S, CHAICHANA K L, et al. Current State of Functional MRI in the Presurgical Planning of Brain Tumors [J]. Radiology Imaging cancer, 2023, 5(6):e230078.https://doi.org/10.1148/rycan.230078. https://doi.org/10.1148/rycan.230078
[16] GAO W. A hierarchical model of early brain functional network development [J]. Trends in cognitive sciences, 2025, 29(9):855-68.https://doi.org/10.1016/j.tics.2025.04.001. https://doi.org/10.1016/j.tics.2025.04.001
[17] KULKARNI S, BASSETT D S. Toward Principles of Brain Network Organization and Function [J]. Annual review of biophysics, 2025, 54(1):353-78.https://doi.org/10.1146/annurev-biophys-030722-110624. https://doi.org/10.1146/annurev-biophys-030722-110624
[18] VAN ES M W J, HIGGINS C, GOHIL C, et al. Large-scale cortical functional networks are organized in structured cycles [J]. Nature neuroscience, 2025, 28(10):2118-28.https://doi.org/10.1038/s41593-025-02052-8. https://doi.org/10.1038/s41593-025-02052-8
[19] YEO B T, KRIENEN F M, SEPULCRE J, et al. The organization of the human cerebral cortex estimated by intrinsic functional connectivity [J]. Journal of neurophysiology, 2011, 106(3):1125-65.https://doi.org/10.1152/jn.00338.2011. https://doi.org/10.1152/jn.00338.2011
[20] POWER J D, COHEN A L, NELSON S M, et al. Functional network organization of the human brain [J]. Neuron, 2011, 72(4):665-78.https://doi.org/10.1016/j.neuron.2011.09.006. https://doi.org/10.1016/j.neuron.2011.09.006
[21] FOX M D, SNYDER A Z, VINCENT J L, et al. The human brain is intrinsically organized into dynamic, anticorrelated functional networks [J]. Proceedings of the National Academy of Sciences of the United States of America, 2005, 102(27):9673-8.https://doi.org/10.1073/pnas.0504136102. https://doi.org/10.1073/pnas.0504136102
[22] MENON V. 20 years of the default mode network: A review and synthesis. Neuron, 2023 Aug, 111(16):2469-2487. https://doi.org/10.1016/j.neuron.2023.04.023. https://doi.org/10.1016/j.neuron.2023.04.023
[23] FEDORENKO E, IVANOVA A A, REGEV T I. The language network as a natural kind within the broader landscape of the human brain [J]. Nature reviews Neuroscience, 2024, 25(5):289-312.https://doi.org/10.1038/s41583-024-00802-4. https://doi.org/10.1038/s41583-024-00802-4
[24] ALVES P N, FORKEL S J, CORBETTA M, et al. The subcortical and neurochemical organization of the ventral and dorsal attention networks [J]. Communications biology, 2022, 5(1):1343.https://doi.org/10.1038/s42003-022-04281-0. https://doi.org/10.1038/s42003-022-04281-0
[25] YESHURUN Y, NGUYEN M, HASSON U. The default mode network:where the idiosyncratic self meets the shared social world [J]. Nature reviews Neuroscience, 2021, 22(3):181-92.https://doi.org/10.1038/s41583-020-00420-w. https://doi.org/10.1038/s41583-020-00420-w
[26] PAQUOLA C, GARBER M, FRäSSLE S, et al. The architecture of the human default mode network explored through cytoarchitecture, wiring and signal flow [J]. Nature neuroscience, 2025, 28(3):654-64.https://doi.org/10.1038/s41593-024-01868-0. https://doi.org/10.1038/s41593-024-01868-0
[27] ELORETTE C, FUJIMOTO A, STOLL F M, et al. The neural basis of resting-state fMRI functional connectivity in fronto-limbic circuits revealed by chemogenetic manipulation [J]. Nature communications, 2024, 15(1):4669.https://doi.org/10.1038/s41467-024-49140-0. https://doi.org/10.1038/s41467-024-49140-0
[28] VAFAII H, MANDINO F, DESROSIERS-GRéGOIRE G, et al. Multimodal measures of spontaneous brain activity reveal both common and divergent patterns of cortical functional organization [J]. Nature communications, 2024, 15(1):229.https://doi.org/10.1038/s41467-023-44363-z. https://doi.org/10.1038/s41467-023-44363-z
[29] MESBAH R, KOENDERS M A, VAN DER WEE N J A, et al. Association Between the Fronto-Limbic Network and Cognitive and Emotional Functioning in Individuals With Bipolar Disorder:A Systematic Review and Meta-analysis [J]. JAMA psychiatry, 2023, 80(5):432-40.https://doi.org/10.1001/jamapsychiatry.2023.0131. https://doi.org/10.1001/jamapsychiatry.2023.0131
[30] BERTOCCI M A, AFRIYIE-AGYEMANG Y, ROZOVSKY R, et al. Altered patterns of central executive, default mode and salience network activity and connectivity are associated with current and future depression risk in two independent young adult samples [J]. Molecular psychiatry, 2023, 28(3):1046-56.https://doi.org/10.1038/s41380-022-01899-8. https://doi.org/10.1038/s41380-022-01899-8
[31] BROWN J A, LEE A J, FERNHOFF K, et al. Functional network collapse in neurodegenerative disease [J]. Nature communications, 2025, 16(1):10273.https://doi.org/10.1038/s41467-025-65156-6. https://doi.org/10.1038/s41467-025-65156-6
[32] SCHUMER M C, BERTOCCI M A, ASLAM H A, et al. Patterns of Neural Network Functional Connectivity Associated With Mania/Hypomania and Depression Risk in 3 Independent Young Adult Samples [J]. JAMA psychiatry, 2024, 81(2):167-77.https://doi.org/10.1001/jamapsychiatry.2023.4150. https://doi.org/10.1001/jamapsychiatry.2023.4150
[33] LUPPI A I, SINGLETON S P, HANSEN J Y, et al. Contributions of network structure, chemoarchitecture and diagnostic categories to transitions between cognitive topographies [J]. Nature biomedical engineering, 2024, 8(9):1142-61.https://doi.org/10.1038/s41551-024-01242-2. https://doi.org/10.1038/s41551-024-01242-2
[34] MATYI M A, RADHAKRISHNAN H, OLM C A, et al. Executive dysfunction relates to salience network desegregation in behavioural variant frontotemporal dementia [J]. NeuroImage Clinical, 2025, 48:103853.https://doi.org/10.1016/j.nicl.2025.103853. https://doi.org/10.1016/j.nicl.2025.103853
[35] HART M G, ROMERO-GARCIA R, PRICE S J, et al. Global Effects of Focal Brain Tumors on Functional Complexity and Network Robustness:A Prospective Cohort Study [J]. Neurosurgery, 2019, 84(6):1201-13.https://doi.org/10.1093/neuros/nyy378. https://doi.org/10.1093/neuros/nyy378
[36] DERKS J, KULIK S D, NUMAN T, et al. Understanding Global Brain Network Alterations in Glioma Patients [J]. Brain connectivity, 2021, 11(10):865-74.https://doi.org/10.1089/brain.2020.0801. https://doi.org/10.1089/brain.2020.0801
[37] FEIGL G C, RITZ R, MORAES M, et al. Resection of malignant brain tumors in eloquent cortical areas:a new multimodal approach combining 5-aminolevulinic acid and intraoperative monitoring [J]. Journal of neurosurgery, 2010, 113(2):352-7.https://doi.org/10.3171/2009.10.JNS09447. https://doi.org/10.3171/2009.10.JNS09447
[38] MANDAL A S, BREM S, SUCKLING J. Brain network mapping and glioma pathophysiology [J]. Brain communications, 2023, 5(2):fcad040.https://doi.org/10.1093/braincomms/fcad040. https://doi.org/10.1093/braincomms/fcad040
[39] ROMERO-GARCIA R, MANDAL A S, BETHLEHEM R A I, et al. Transcriptomic and connectomic correlates of differential spatial patterning among gliomas [J]. Brain :a journal of neurology, 2023, 146(3):1200-11.https://doi.org/10.1093/brain/awac378. https://doi.org/10.1093/brain/awac378
[40] SUN Y, WANG X, ZHANG D Y, et al. Brain-wide neuronal circuit connectome of human glioblastoma [J]. Nature, 2025, 641(8061):222-31.https://doi.org/10.1038/s41586-025-08634-7. https://doi.org/10.1038/s41586-025-08634-7
[41] DOUW L, REIJNEVELD J C, MANDAL A S. Multiscale network perspectives on glioma:from tumour biology to symptoms, survival and treatment [J]. Nature reviews Neurology, 2026, 22(2):73-89.https://doi.org/10.1038/s41582-025-01171-x. https://doi.org/10.1038/s41582-025-01171-x
[42] WEI Y, LI C, CUI Z, et al. Structural connectome quantifies tumour invasion and predicts survival in glioblastoma patients [J]. Brain :a journal of neurology, 2023, 146(4):1714-27.https://doi.org/10.1093/brain/awac360. https://doi.org/10.1093/brain/awac360
[43] SHABO E, SARIKAYA-SEIWERT S, BORGER V, et al. Neurosurgery 4.0:A Scoping Review of Current Trends and Challenges in Specialized Smart Hospitals [J]. Cureus, 2025, 17(9):e92673.https://doi.org/10.7759/cureus.92673. https://doi.org/10.7759/cureus.92673
[44] SUN C, ZHANG J, BU L, et al. A speech fluency brain network derived from gliomas [J]. Brain communications, 2024, 6(3):fcae153.https://doi.org/10.1093/braincomms/fcae153. https://doi.org/10.1093/braincomms/fcae153
[45] WU Z, HU G, CAO B, et al. Non-traditional cognitive brain network involvement in insulo-Sylvian gliomas:a case series study and clinical experience using Quicktome [J]. Chin Neurosurg J, 2023, 9(1):16.https://doi.org/10.1186/s41016-023-00325-4. https://doi.org/10.1186/s41016-023-00325-4
[46] KRISHNA S, CHOUDHURY A, KEOUGH M B, et al. Glioblastoma remodelling of human neural circuits decreases survival [J]. Nature, 2023, 617(7961):599-607.https://doi.org/10.1038/s41586-023-06036-1. https://doi.org/10.1038/s41586-023-06036-1
[47] TAYLOR K R, BARRON T, HUI A, et al. Glioma synapses recruit mechanisms of adaptive plasticity [J]. Nature, 2023, 623(7986):366-74.https://doi.org/10.1038/s41586-023-06678-1. https://doi.org/10.1038/s41586-023-06678-1
[48] WANG Y, WANG Y, BAO H, et al. Mechanisms and therapeutic implications of glioma-neuron interactions [J]. Cancer letters, 2025, 629:217884.https://doi.org/10.1016/j.canlet.2025.217884. https://doi.org/10.1016/j.canlet.2025.217884
[49] EL OUADIH Y, PEREIRA B, BIAU J, et al. DTI Abnormalities Related to Glioblastoma:A Prospective Comparative Study with Metastasis and Healthy Subjects [J]. Current oncology (Toronto, Ont), 2022, 29(4):2823-34.https://doi.org/10.3390/curroncol29040230. https://doi.org/10.3390/curroncol29040230
[50] MORELL A A, EICHBERG D G, SHAH A H, et al. Using machine learning to evaluate large-scale brain networks in patients with brain tumors:Traditional and non-traditional eloquent areas [J]. Neurooncol Adv, 2022, 4(1):vdac142.https://doi.org/10.1093/noajnl/vdac142. https://doi.org/10.1093/noajnl/vdac142
[51] MEYER J, YU K, LUNA-FIGUEROA E, et al. Glioblastoma disrupts cortical network activity at multiple spatial and temporal scales [J]. Nature communications, 2024, 15(1):4503.https://doi.org/10.1038/s41467-024-48757-5. https://doi.org/10.1038/s41467-024-48757-5
[52] NEJO T, KRISHNA S, YAMAMICHI A, et al. Glioma-neuronal circuit remodeling induces regional immunosuppression [J]. Nature communications, 2025, 16(1):4770.https://doi.org/10.1038/s41467-025-60074-z. https://doi.org/10.1038/s41467-025-60074-z
[53] DUFFAU H. The challenge to remove diffuse low-grade gliomas while preserving brain functions [J]. Acta Neurochir (Wien), 2012, 154(4):569-74.https://doi.org/10.1007/s00701-012-1275-7. https://doi.org/10.1007/s00701-012-1275-7
[54] GERRITSEN J K W, KARSCHNIA P, BELLO L, et al. A comprehensive framework for glioma surgery by the PIONEER Consortium and RANO resect group, part 2:perioperative recommendations for neurological, language, functional, and quality-of-life assessment [J]. The Lancet Oncology, 2026, 27(1):e24-e32.https://doi.org/10.1016/s1470-2045(25)00532-7. https://doi.org/10.1016/s1470-2045(25)00532-7
[55] YOUNG J S, LEE A T, CHANG E F. A Review of Cortical and Subcortical Stimulation Mapping for Language [J]. Neurosurgery, 2021, 89(3):331-42.https://doi.org/10.1093/neuros/nyaa436. https://doi.org/10.1093/neuros/nyaa436
[56] GERRITSEN J K W, KARSCHNIA P, BELLO L, et al. A comprehensive framework for glioma surgery by the PIONEER Consortium and RANO resect group, part 1:intraoperative recommendations for mapping, monitoring, and decision making [J]. The Lancet Oncology, 2026, 27(1):e11-e23.https://doi.org/10.1016/s1470-2045(25)00531-5. https://doi.org/10.1016/s1470-2045(25)00531-5
[57] SAMUEL N, VETKAS A, PANCHOLI A, et al. A Network-Based Approach to Glioma Surgery:Insights from Functional Neurosurgery [J]. Cancers (Basel), 2021, 13(23).https://doi.org/10.3390/cancers13236127. https://doi.org/10.3390/cancers13236127
[58] FALCó-ROGET J, CACCIOLA A, SAMBATARO F, et al. Functional and structural reorganization in brain tumors:a machine learning approach using desynchronized functional oscillations [J]. Communications biology, 2024, 7(1):419.https://doi.org/10.1038/s42003-024-06119-3. https://doi.org/10.1038/s42003-024-06119-3
[59] BOU DARGHAM T, WINTER S F, BATICH K, et al. Neurocognitive outcomes in patients with brain metastases:a systematic review [J]. The Lancet Oncology, 2025, 26(12):e671-e82.https://doi.org/10.1016/s1470-2045(25)00525-x. https://doi.org/10.1016/s1470-2045(25)00525-x
[60] ROMERO-GARCIA R, SUCKLING J, OWEN M, et al. Memory recovery in relation to default mode network impairment and neurite density during brain tumor treatment [J]. Journal of neurosurgery, 2022, 136(2):358-68.https://doi.org/10.3171/2021.1.Jns203959. https://doi.org/10.3171/2021.1.Jns203959
[61] MUELLER S, WANG D, FOX M D, et al. Individual variability in functional connectivity architecture of the human brain [J]. Neuron, 2013, 77(3):586-95.https://doi.org/10.1016/j.neuron.2012.12.028. https://doi.org/10.1016/j.neuron.2012.12.028
[62] CUI W, WANG Y, REN J, et al. Personalized fMRI Delineates Functional Regions Preserved within Brain Tumors [J]. Annals of neurology, 2022, 91(3):353-66.https://doi.org/10.1002/ana.26303. https://doi.org/10.1002/ana.26303
[63] PAIVA W S, FONOFF E T, DOS SANTOS SILVA R P, et al. Preoperative Cortical Mapping for Brain Tumor Surgery Using Navigated Transcranial Stimulation:Analysis of Accuracy [J]. Brain sciences, 2024, 14(9).https://doi.org/10.3390/brainsci14090867. https://doi.org/10.3390/brainsci14090867
[64] SINHA S, KALYAL N, GALLAGHER M J, et al. Impact of Preoperative Mapping and Intraoperative Neuromonitoring in Minimally Invasive Parafascicular Surgery for Deep-Seated Lesions [J]. World neurosurgery, 2024, 181:e1019-e37.https://doi.org/10.1016/j.wneu.2023.11.030. https://doi.org/10.1016/j.wneu.2023.11.030
[65] BAIG MIRZA A, VASTANI A, SUVARNA R, et al. Preoperative and intraoperative neuromonitoring and mapping techniques impact oncological and functional outcomes in supratentorial function-eloquent brain tumours:a systematic review and meta-analysis [J]. EClinicalMedicine, 2025, 80:103055.https://doi.org/10.1016/j.eclinm.2024.103055. https://doi.org/10.1016/j.eclinm.2024.103055
[66] SMOLDERS L, DE BAENE W, GEHRING K, et al. Presurgical structural connectivity predicts postsurgical cognitive impairment in glioma patients [J]. Brain communications, 2025, 7(5):fcaf346.https://doi.org/10.1093/braincomms/fcaf346. https://doi.org/10.1093/braincomms/fcaf346
[67] YUAN B, ZHANG N, YAN J, et al. Resting-state functional connectivity predicts individual language impairment of patients with left hemispheric gliomas involving language network [J]. NeuroImage Clinical, 2019, 24:102023.https://doi.org/10.1016/j.nicl.2019.102023. https://doi.org/10.1016/j.nicl.2019.102023
[68] AYDOGAN D B, SOUZA V H, MATSUDA R H, et al. Real-Time Tractography-Assisted Neuronavigation for Transcranial Magnetic Stimulation [J]. Human brain mapping, 2025, 46(1):e70122.https://doi.org/10.1002/hbm.70122. https://doi.org/10.1002/hbm.70122
[69] MUIR M T, NOLL K, PRINSLOO S, et al. Preoperative Brain Mapping Predicts Language Outcomes After Eloquent Tumor Resection [J]. Human brain mapping, 2025, 46(15):e70340.https://doi.org/10.1002/hbm.70340. https://doi.org/10.1002/hbm.70340
[70] SOMMER B, GRUMMICH P, HAMER H, et al. Frameless stereotactic functional neuronavigation combined with intraoperative magnetic resonance imaging as a strategy in highly eloquent located tumors causing epilepsy [J]. Stereotactic and functional neurosurgery, 2014, 92(1):59-67.https://doi.org/10.1159/000355216. https://doi.org/10.1159/000355216
[71] NINATTI G, SOLLINI M, BONO B, et al. Preoperative [11C]methionine PET to personalize treatment decisions in patients with lower-grade gliomas [J]. Neuro-oncology, 2022, 24(9):1546-56.https://doi.org/10.1093/neuonc/noac040. https://doi.org/10.1093/neuonc/noac040
[72] FREY D, SCHILT S, STRACK V, et al. Navigated transcranial magnetic stimulation improves the treatment outcome in patients with brain tumors in motor eloquent locations [J]. Neuro-oncology, 2014, 16(10):1365-72.https://doi.org/10.1093/neuonc/nou110. https://doi.org/10.1093/neuonc/nou110
[73] PICHT T, SCHMIDT S, BRANDT S, et al. Preoperative functional mapping for rolandic brain tumor surgery:comparison of navigated transcranial magnetic stimulation to direct cortical stimulation [J]. Neurosurgery, 2011, 69(3):581-8; discussion 8.https://doi.org/10.1227/NEU.0b013e3182181b89. https://doi.org/10.1227/NEU.0b013e3182181b89
[74] LEONE A, CARBONE F, SPETZGER U, et al. Preoperative mapping techniques for brain tumor surgery:a systematic review [J]. Front Oncol, 2024, 14:1481430.https://doi.org/10.3389/fonc.2024.1481430. https://doi.org/10.3389/fonc.2024.1481430
[75] RAFFA G, QUATTROPANI M C, GERMANò A. When imaging meets neurophysiology:the value of navigated transcranial magnetic stimulation for preoperative neurophysiological mapping prior to brain tumor surgery [J]. Neurosurg Focus, 2019, 47(6):E10.https://doi.org/10.3171/2019.9.Focus19640. https://doi.org/10.3171/2019.9.Focus19640
[76] PICHT T, MULARSKI S, KUEHN B, et al. Navigated transcranial magnetic stimulation for preoperative functional diagnostics in brain tumor surgery [J]. Neurosurgery, 2009, 65(6 Suppl):93-8; discussion 8-9.https://doi.org/10.1227/01.Neu.0000348009.22750.59. https://doi.org/10.1227/01.Neu.0000348009.22750.59
[77] INDHARTY R S, JAPARDI I, IRINA R S, et al. Comparison of direct cortical stimulation and transcranial magnetic stimulation in brain tumor surgery:systematic review and meta analyses [J]. J Neurooncol, 2023, 163(3):505-14.https://doi.org/10.1007/s11060-023-04378-4. https://doi.org/10.1007/s11060-023-04378-4
[78] HADDAD A F, YOUNG J S, BERGER M S, et al. Preoperative Applications of Navigated Transcranial Magnetic Stimulation [J]. Frontiers in neurology, 2020, 11:628903.https://doi.org/10.3389/fneur.2020.628903. https://doi.org/10.3389/fneur.2020.628903
[79] MEYERS C A, BROWN P D. Role and relevance of neurocognitive assessment in clinical trials of patients with CNS tumors [J]. Journal of clinical oncology :official journal of the American Society of Clinical Oncology, 2006, 24(8):1305-9.https://doi.org/10.1200/jco.2005.04.6086. https://doi.org/10.1200/jco.2005.04.6086
[80] TAPHOORN M J, KLEIN M. Cognitive deficits in adult patients with brain tumours [J]. The Lancet Neurology, 2004, 3(3):159-68.https://doi.org/10.1016/s1474-4422(04)00680-5. https://doi.org/10.1016/s1474-4422(04)00680-5
[81] PARSONS M W, DIETRICH J. Assessment and Management of Cognitive Symptoms in Patients With Brain Tumors [J]. 2021, (41):e90-e9.https://doi.org/10.1200/edbk_320813. https://doi.org/10.1200/edbk_320813
[82] NASREDDINE Z S, PHILLIPS N A, BéDIRIAN V, et al. The Montreal Cognitive Assessment, MoCA:a brief screening tool for mild cognitive impairment [J]. Journal of the American Geriatrics Society, 2005, 53(4):695-9.https://doi.org/10.1111/j.1532-5415.2005.53221.x. https://doi.org/10.1111/j.1532-5415.2005.53221.x
[83] JAMMULA V, ROGERS J L, VERA E, et al. The Montreal Cognitive Assessment (MoCA) in neuro-oncology:A pilot study of feasibility and utility in telehealth and in-person clinical assessments [J]. Neuro-oncology practice, 2022, 9(5):429-40.https://doi.org/10.1093/nop/npac038. https://doi.org/10.1093/nop/npac038
[84] CARR J H, SHEPHERD R B, NORDHOLM L, et al. Investigation of a new motor assessment scale for stroke patients [J]. Physical therapy, 1985, 65(2):175-80.https://doi.org/10.1093/ptj/65.2.175. https://doi.org/10.1093/ptj/65.2.175
[85] NOLL K R, ZIU M, WEINBERG J S, et al. Neurocognitive functioning in patients with glioma of the left and right temporal lobes [J]. Journal of neuro-oncology, 2016, 128(2):323-31.https://doi.org/10.1007/s11060-016-2114-0. https://doi.org/10.1007/s11060-016-2114-0
[86] ISLAM N, HASHEM R, GAD M, et al. Accuracy of the Montreal Cognitive Assessment tool for detecting mild cognitive impairment:A systematic review and meta-analysis [J]. Alzheimers Dement, 2023, 19(7):3235-43.https://doi.org/10.1002/alz.13040. https://doi.org/10.1002/alz.13040
[87] TOMASINO B, GUARRACINO I, IUS T, et al. Continuous Real-Time Neuropsychological Testing during Resection Phase in Left and Right Prefrontal Brain Tumors [J]. Curr Oncol, 2023, 30(2):2007-20.https://doi.org/10.3390/curroncol30020156. https://doi.org/10.3390/curroncol30020156
[88] CARPENTIERI S C, WABER D P, POMEROY S L, et al. Neuropsychological functioning after surgery in children treated for brain tumor [J]. Neurosurgery, 2003, 52(6):1348-56; discussion 56-7.https://doi.org/10.1227/01.neu.0000064804.00766.62. https://doi.org/10.1227/01.neu.0000064804.00766.62
[89] TAYLOR J W, WEYER-JAMORA C, HERVEY-JUMPER S. Molecularly determining cognition in glioma:New insights as the plot thickens [J]. Neuro-oncology, 2022, 24(10):1671-2.https://doi.org/10.1093/neuonc/noac149. https://doi.org/10.1093/neuonc/noac149
[90] VAN KESSEL E, BERENDSEN S, BAUMFALK A E, et al. Tumor-related molecular determinants of neurocognitive deficits in patients with diffuse glioma [J]. Neuro-oncology, 2022, 24(10):1660-70.https://doi.org/10.1093/neuonc/noac036. https://doi.org/10.1093/neuonc/noac036
[91] WACH J, VYCHOPEN M, BASARAN A E, et al. Efficacy and safety of intraoperative MRI in glioma surgery:a systematic review and meta-analysis of prospective randomized controlled trials [J]. Journal of neurosurgery, 2025, 142(5):1319-30.https://doi.org/10.3171/2024.7.Jns241102. https://doi.org/10.3171/2024.7.Jns241102
[92] SENFT C, BINK A, FRANZ K, et al. Intraoperative MRI guidance and extent of resection in glioma surgery:a randomised, controlled trial [J]. The Lancet Oncology, 2011, 12(11):997-1003.https://doi.org/10.1016/s1470-2045(11)70196-6. https://doi.org/10.1016/s1470-2045(11)70196-6
[93] DUFFAU H. Lessons from brain mapping in surgery for low-grade glioma:insights into associations between tumour and brain plasticity [J]. The Lancet Neurology, 2005, 4(8):476-86.https://doi.org/10.1016/s1474-4422(05)70140-x. https://doi.org/10.1016/s1474-4422(05)70140-x
[94] KöHLERT K, JäHNE K, SAUR D, et al. Neurophysiological examination combined with functional intraoperative navigation using TMS in patients with brain tumor near the central region-a pilot study [J]. Acta Neurochir (Wien), 2019, 161(9):1853-64.https://doi.org/10.1007/s00701-019-04004-1. https://doi.org/10.1007/s00701-019-04004-1
[95] DE WITT HAMER P C, ROBLES S G, ZWINDERMAN A H, et al. Impact of intraoperative stimulation brain mapping on glioma surgery outcome:a meta-analysis [J]. Journal of clinical oncology :official journal of the American Society of Clinical Oncology, 2012, 30(20):2559-65.https://doi.org/10.1200/jco.2011.38.4818. https://doi.org/10.1200/jco.2011.38.4818
[96] LOWENSTEIN P R, CASTRO M G. Pushing the Limits of Glioma Resection Using Electrophysiologic Brain Mapping [J]. 2012, 30(20):2437-40.https://doi.org/10.1200/jco.2011.40.6959. https://doi.org/10.1200/jco.2011.40.6959
[97] MACDONALD D B, SKINNER S, SHILS J, et al. Intraoperative motor evoked potential monitoring - a position statement by the American Society of Neurophysiological Monitoring [J]. Clinical neurophysiology :official journal of the International Federation of Clinical Neurophysiology, 2013, 124(12):2291-316.https://doi.org/10.1016/j.clinph.2013.07.025. https://doi.org/10.1016/j.clinph.2013.07.025
[98] LI T, BAI H, WANG G, et al. Glioma localization and excision using direct electrical stimulation for language mapping during awake surgery [J]. Experimental and therapeutic medicine, 2015, 9(5):1962-6.https://doi.org/10.3892/etm.2015.2359. https://doi.org/10.3892/etm.2015.2359
[99] FATEMI P, ZHANG M, MILLER K J, et al. How Intraoperative Tools and Techniques Have Changed the Approach to Brain Tumor Surgery [J]. Curr Oncol Rep, 2018, 20(11):89.https://doi.org/10.1007/s11912-018-0723-9. https://doi.org/10.1007/s11912-018-0723-9
[100] BRELL M, IBáñEZ J, CARAL L, et al. Factors influencing surgical complications of intra-axial brain tumours [J]. Acta Neurochir (Wien), 2000, 142(7):739-50.https://doi.org/10.1007/s007010070088. https://doi.org/10.1007/s007010070088
[101] DUFFAU H, LOPES M, ARTHUIS F, et al. Contribution of intraoperative electrical stimulations in surgery of low grade gliomas:a comparative study between two series without (1985-96) and with (1996-2003) functional mapping in the same institution [J]. J Neurol Neurosurg Psychiatry, 2005, 76(6):845-51.https://doi.org/10.1136/jnnp.2004.048520. https://doi.org/10.1136/jnnp.2004.048520
[102] KAMP M A, FINK L, FORSTER M T, et al. In-patient neurosurgical tumor treatments for malignant glioma patients in Germany [J]. J Neurooncol, 2024, 170(3):527-42.https://doi.org/10.1007/s11060-024-04784-2. https://doi.org/10.1007/s11060-024-04784-2
[103] BAYER S, MAIER A, OSTERMEIER M, et al. Intraoperative Imaging Modalities and Compensation for Brain Shift in Tumor Resection Surgery [J]. International journal of biomedical imaging, 2017, 2017:6028645.https://doi.org/10.1155/2017/6028645. https://doi.org/10.1155/2017/6028645
[104] NARASIMHAN S, WEIS J A, LUO M, et al. Accounting for intraoperative brain shift ascribable to cavity collapse during intracranial tumor resection [J]. Journal of medical imaging (Bellingham, Wash), 2020, 7(3):031506.https://doi.org/10.1117/1.Jmi.7.3.031506. https://doi.org/10.1117/1.Jmi.7.3.031506
[105] FOUNTAIN D M, BRYANT A, BARONE D G, et al. Intraoperative imaging technology to maximise extent of resection for glioma:a network meta-analysis [J]. The Cochrane database of systematic reviews, 2021, 1(1):Cd013630.https://doi.org/10.1002/14651858.CD013630.pub2. https://doi.org/10.1002/14651858.CD013630.pub2
[106] GIUSSANI C, TREZZA A, RICCIUTI V, et al. Intraoperative MRI versus intraoperative ultrasound in pediatric brain tumor surgery:is expensive better than cheap? A review of the literature [J]. Childs Nerv Syst, 2022, 38(8):1445-54.https://doi.org/10.1007/s00381-022-05545-0. https://doi.org/10.1007/s00381-022-05545-0
[107] XIE X, SHEN C, ZHANG X, et al. Rapid intraoperative multi-molecular diagnosis of glioma with ultrasound radio frequency signals and deep learning [J]. EBioMedicine, 2023, 98:104899.https://doi.org/10.1016/j.ebiom.2023.104899. https://doi.org/10.1016/j.ebiom.2023.104899
[108] FERGUSON J, HWANG S W, TATARYN Z, et al. Neuromonitoring changes in pediatric spinal deformity surgery:a single-institution experience [J]. J Neurosurg Pediatr, 2014, 13(3):247-54.https://doi.org/10.3171/2013.12.Peds13188. https://doi.org/10.3171/2013.12.Peds13188
[109] SAMDANI A F, BENNETT J T, AMES R J, et al. Reversible Intraoperative Neurophysiologic Monitoring Alerts in Patients Undergoing Arthrodesis for Adolescent Idiopathic Scoliosis:What Are the Outcomes of Surgery? [J]. J Bone Joint Surg Am, 2016, 98(17):1478-83.https://doi.org/10.2106/jbjs.15.01379. https://doi.org/10.2106/jbjs.15.01379
[110] KARSCHNIA P, GERRITSEN J K W, TESKE N, et al. The oncological role of resection in newly diagnosed diffuse adult-type glioma defined by the WHO 2021 classification:a Review by the RANO resect group [J]. The Lancet Oncology, 2024, 25(9):e404-e19.https://doi.org/10.1016/s1470-2045(24)00130-x. https://doi.org/10.1016/s1470-2045(24)00130-x
[111] HERBET G, DUFFAU H. Revisiting the Functional Anatomy of the Human Brain:Toward a Meta-Networking Theory of Cerebral Functions [J]. Physiological reviews, 2020, 100(3):1181-228.https://doi.org/10.1152/physrev.00033.2019. https://doi.org/10.1152/physrev.00033.2019
[112] CHOWDHURY T, SINGH G P, ZEILER F A, et al. Anesthesia for Awake Craniotomy for Brain Tumors in an Intraoperative MRI Suite:Challenges and Evidence [J]. Frontiers in oncology, 2018, 8:519.https://doi.org/10.3389/fonc.2018.00519. https://doi.org/10.3389/fonc.2018.00519
[113] THUET E D, WINSCHER J C, PADBERG A M, et al. Validity and reliability of intraoperative monitoring in pediatric spinal deformity surgery:a 23-year experience of 3436 surgical cases [J]. Spine (Phila Pa 1976), 2010, 35(20):1880-6.https://doi.org/10.1097/BRS.0b013e3181e53434. https://doi.org/10.1097/BRS.0b013e3181e53434
[114] DE ZWART B, RUIS C. An update on tests used for intraoperative monitoring of cognition during awake craniotomy [J]. Acta neurochirurgica, 2024, 166(1):204.https://doi.org/10.1007/s00701-024-06062-6. https://doi.org/10.1007/s00701-024-06062-6
[115] TOMASELLI A, LUCA A, FERINI G, et al. Cognitive Profiles and Determinants of Eligibility for Awake Surgery in Non-Dominant Hemisphere Gliomas:A Narrative Review [J]. Brain and behavior, 2025, 15(6):e70604.https://doi.org/10.1002/brb3.70604. https://doi.org/10.1002/brb3.70604
[116] LANDERS M J F, BROUWERS B, WEGGELAAR A M, et al. Monitoring of Executive Functions During Awake Glioma Surgery:A Standardized Multicenter Protocol [J]. Neurosurgery practice, 2025, 6(3):e000152.https://doi.org/10.1227/neuprac.0000000000000152. https://doi.org/10.1227/neuprac.0000000000000152
[117] MCCRACKEN D J, SCHUPPER A J, LAKOMKIN N, et al. Turning on the light for brain tumor surgery:A 5-aminolevulinic acid story [J]. Neuro-oncology, 2022, 24(Suppl 6):S52-s61.https://doi.org/10.1093/neuonc/noac191. https://doi.org/10.1093/neuonc/noac191
[118] WELLER M, VAN DEN BENT M, PREUSSER M, et al. EANO guidelines on the diagnosis and treatment of diffuse gliomas of adulthood [J]. Nature reviews Clinical oncology, 2021, 18(3):170-86.https://doi.org/10.1038/s41571-020-00447-z. https://doi.org/10.1038/s41571-020-00447-z
[119] STUMMER W, PICHLMEIER U, MEINEL T, et al. Fluorescence-guided surgery with 5-aminolevulinic acid for resection of malignant glioma:a randomised controlled multicentre phase III trial [J]. The Lancet Oncology, 2006, 7(5):392-401.https://doi.org/10.1016/s1470-2045(06)70665-9. https://doi.org/10.1016/s1470-2045(06)70665-9
[120] WANG X, ZUO Z, YU S, et al. Long-term clinical prognosis of patients with gliomas infiltrating corticospinal tract on DTI tractography [J]. Chinese neurosurgical journal, 2025, 11(1):26.https://doi.org/10.1186/s41016-025-00412-8. https://doi.org/10.1186/s41016-025-00412-8
[121] BEN DOR N, SIGHINOLFI G, ROSETTI V, et al. Diffusion Tensor Imaging Biomarkers to Predict Neurological Outcomes in Brain Surgery:A Systematic Review [J]. Life (Basel, Switzerland), 2026, 16(1).https://doi.org/10.3390/life16010115. https://doi.org/10.3390/life16010115
[122] FRIEDRICH M, FILSS C P, LOHMANN P, et al. Structural connectome-based predictive modeling of cognitive deficits in treated glioma patients [J]. Neuro-oncology advances, 2024, 6(1):vdad151.https://doi.org/10.1093/noajnl/vdad151. https://doi.org/10.1093/noajnl/vdad151
[123] KAWAHIRA K, SHIMODOZONO M, OGATA A, et al. Addition of intensive repetition of facilitation exercise to multidisciplinary rehabilitation promotes motor functional recovery of the hemiplegic lower limb [J]. J Rehabil Med, 2004, 36(4):159-64.https://doi.org/10.1080/16501970410029753. https://doi.org/10.1080/16501970410029753
[124] DONNELLY B M, STARK K G, PERSAUD C J, et al. Optimizing post-acute care inpatient rehabilitation for patients with brain metastasis:A systematic review of functional outcomes [J]. Supportive care in cancer :official journal of the Multinational Association of Supportive Care in Cancer, 2025, 33(5):418.https://doi.org/10.1007/s00520-025-09468-9. https://doi.org/10.1007/s00520-025-09468-9
[125] MCLARNEY M, FERGESTROM N, ZHENG J, et al. Rehabilitation after brain tumor resection:A national study of postacute care service use through insurance claims data [J]. Pm r, 2024, 16(5):441-8.https://doi.org/10.1002/pmrj.13117. https://doi.org/10.1002/pmrj.13117
[126] MARCINIAK C M, SLIWA J A, HEINEMANN A W, et al. Functional outcomes of persons with brain tumors after inpatient rehabilitation [J]. Arch Phys Med Rehabil, 2001, 82(4):457-63.https://doi.org/10.1053/apmr.2001.21862. https://doi.org/10.1053/apmr.2001.21862
[127] YUAN Y, GU Q, ZHU M, et al. Frailty-originated early rehabilitation reduces postoperative delirium in brain tumor patients:Results from a prospective randomized study [J]. Asia-Pacific journal of oncology nursing, 2023, 10(8):100263.https://doi.org/10.1016/j.apjon.2023.100263. https://doi.org/10.1016/j.apjon.2023.100263
[128] ENGELHARDT M, SCHNEIDER H, REUTHER J, et al. Low-frequency repetitive transcranial magnetic stimulation in patients with motor deficits after brain tumor resection:a randomized, double-blind, sham-controlled trial [J]. Frontiers in oncology, 2024, 14:1368924.https://doi.org/10.3389/fonc.2024.1368924. https://doi.org/10.3389/fonc.2024.1368924
[129] POOLOGAINDRAN A, PROFYRIS C, YOUNG I M, et al. Interventional neurorehabilitation for promoting functional recovery post-craniotomy:a proof-of-concept [J]. Sci Rep, 2022, 12(1):3039.https://doi.org/10.1038/s41598-022-06766-8. https://doi.org/10.1038/s41598-022-06766-8
[130] ENGELHARDT M, GRITTNER U, KRIEG S, et al. Preconditioning of the motor network with repetitive navigated transcranial magnetic stimulation (rnTMS) to improve oncological and functional outcome in brain tumor surgery:a study protocol for a randomized, sham-controlled, triple-blind clinical trial [J]. Trials, 2023, 24(1):638.https://doi.org/10.1186/s13063-023-07640-2. https://doi.org/10.1186/s13063-023-07640-2
[131] EINSTEIN E H, DADARIO N B, KHILJI H, et al. Transcranial magnetic stimulation for post-operative neurorehabilitation in neuro-oncology:a review of the literature and future directions [J]. J Neurooncol, 2022, 157(3):435-43.https://doi.org/10.1007/s11060-022-03987-9. https://doi.org/10.1007/s11060-022-03987-9
[132] MA J, RUI Z, ZOU Y, et al. Neurosurgical and BCI approaches to visual rehabilitation in occipital lobe tumor patients [J]. Heliyon, 2024, 10(23):e39072.https://doi.org/10.1016/j.heliyon.2024.e39072. https://doi.org/10.1016/j.heliyon.2024.e39072
[133] YOUNG M J, LIN D J, HOCHBERG L R. Brain-Computer Interfaces in Neurorecovery and Neurorehabilitation [J]. Seminars in neurology, 2021, 41(2):206-16.https://doi.org/10.1055/s-0041-1725137. https://doi.org/10.1055/s-0041-1725137
[134] CARINO-ESCOBAR R I, RODRIGUEZ-BARRAGAN M A, CARRILLO-MORA P, et al. Brain-computer interface as complementary therapy for hemiparesis in an astrocytoma patient [J]. Neurol Sci, 2022, 43(4):2879-81.https://doi.org/10.1007/s10072-022-05924-0. https://doi.org/10.1007/s10072-022-05924-0
[135] CHAUDHARY U, BIRBAUMER N, RAMOS-MURGUIALDAY A. Brain-computer interfaces for communication and rehabilitation [J]. Nature reviews Neurology, 2016, 12(9):513-25.https://doi.org/10.1038/nrneurol.2016.113. https://doi.org/10.1038/nrneurol.2016.113
[136] WANG N, TU W J. Editorial:Brain-computer interfaces in neurological disorders:expanding horizons for diagnosis, treatment, and rehabilitation [J]. Frontiers in neuroscience, 2024, 18:1526723.https://doi.org/10.3389/fnins.2024.1526723. https://doi.org/10.3389/fnins.2024.1526723
[137] EKERT J O, GOYAL A, YOUNG J S, et al. Interventional neurorehabilitation for glioma patients:A systematic review [J]. Neuro-oncology practice, 2024, 11(6):679-90.https://doi.org/10.1093/nop/npae066. https://doi.org/10.1093/nop/npae066
[138] DE ROECK L, COLAES R, DUPONT P, et al. Increased functional network segregation in glioma patients posttherapy:A neurological compensatory response or catastrophe for cognition? [J]. Network neuroscience (Cambridge, Mass), 2025, 9(2):743-60.https://doi.org/10.1162/netn_a_00449. https://doi.org/10.1162/netn_a_00449
[139] SAVIOLA F, ZIGIOTTO L, NOVELLO L, et al. The role of the default mode network in longitudinal functional brain reorganization of brain gliomas [J]. Brain structure & function, 2022, 227(9):2923-37.https://doi.org/10.1007/s00429-022-02490-1. https://doi.org/10.1007/s00429-022-02490-1
[140] RAMíREZ-FERRER E, AGUILERA-PENA M P, DUFFAU H. Functional and oncological outcomes after right hemisphere glioma resection in awake versus asleep patients:a systematic review and meta-analysis [J]. Neurosurgical review, 2024, 47(1):160.https://doi.org/10.1007/s10143-024-02370-8. https://doi.org/10.1007/s10143-024-02370-8
[142] PEROVNIK M, RUS T, SCHINDLBECK K A, et al. Functional brain networks in the evaluation of patients with neurodegenerative disorders [J]. Nat Rev Neurol, 2023, 19(2):73-90.https://doi.org/10.1038/s41582-022-00753-3. https://doi.org/10.1038/s41582-022-00753-3
[144] DUFFAU H. The huge plastic potential of adult brain and the role of connectomics:new insights provided by serial mappings in glioma surgery [J]. Cortex; a journal devoted to the study of the nervous system and behavior, 2014, 58:325-37.https://doi.org/10.1016/j.cortex.2013.08.005. https://doi.org/10.1016/j.cortex.2013.08.005
[145] YANG J, KUDULAITI N, CHEN Z, et al. Within and beyond the visual cortex:brain tumors induce highly sensitive plasticity of visual processing in whole-brain neural functional networks [J]. Cerebral cortex (New York, NY :1991), 2022, 32(20):4422-35.https://doi.org/10.1093/cercor/bhab492. https://doi.org/10.1093/cercor/bhab492
[146] NG S, MORITZ-GASSER S, LEMAITRE A L, et al. Multivariate mapping of low-resilient neurocognitive systems within and around low-grade gliomas [J]. Brain :a journal of neurology, 2024, 147(8):2718-31.https://doi.org/10.1093/brain/awae130. https://doi.org/10.1093/brain/awae130
[147] DUFFAU H. Brain plasticity:from pathophysiological mechanisms to therapeutic applications [J]. Journal of clinical neuroscience :official journal of the Neurosurgical Society of Australasia, 2006, 13(9):885-97.https://doi.org/10.1016/j.jocn.2005.11.045. https://doi.org/10.1016/j.jocn.2005.11.045
[148] BI W L, HOSNY A, SCHABATH M B, et al. Artificial intelligence in cancer imaging:Clinical challenges and applications [J]. CA:a cancer journal for clinicians, 2019, 69(2):127-57.https://doi.org/10.3322/caac.21552. https://doi.org/10.3322/caac.21552
[149] KICKINGEREDER P, ISENSEE F, TURSUNOVA I, et al. Automated quantitative tumour response assessment of MRI in neuro-oncology with artificial neural networks:a multicentre, retrospective study [J]. The Lancet Oncology, 2019, 20(5):728-40.https://doi.org/10.1016/s1470-2045(19)30098-1. https://doi.org/10.1016/s1470-2045(19)30098-1
[150] BOERGER T F, PAHAPILL P, BUTTS A M, et al. Large-scale brain networks and intra-axial tumor surgery:a narrative review of functional mapping techniques, critical needs, and scientific opportunities [J]. Frontiers in human neuroscience, 2023, 17:1170419.https://doi.org/10.3389/fnhum.2023.1170419. https://doi.org/10.3389/fnhum.2023.1170419
Peer-review Terminology
Identity transparency: Single-anonymous
Reviewer interacts with: Editor
Details
This is an open access article under the terms of the Creative Commons Attribution License(http://creativecommons.org/licenses/by/4.0/), which permits use, distribution and reproduction in any medium, provided the original work is properly cited.
Publication History
Received 2026-02-02
Accepted 2026-05-12
Published 2026-07-03