




Abstract
Objectives: This study aims to explore the feasibility of utilizing tracheal cartilage vascularized with a pectoralis major muscle flap for the reconstruction of vertical hemilaryngeal defects and to provide an experimental foundation for such reconstructions.
Methods: Initially, the tracheal cartilages of nine Beagle canines were vascularized using pectoralis major muscle flaps. Subsequently, a defect model was established by vertically resecting the entire hemilarynx, and the vertical hemilaryngeal defect was reconstructed using the vascularized tracheal cartilage. Laryngeal CT and video laryngoscopy were conducted pre-operation, immediately post-operation, and 28 days post-operation. The reconstructed larynx was then examined histologically.
Results: Eight dogs were successfully extubated and could consume normal food. Immediate postoperative video laryngoscopy indicated a well-sutured trachea, normal mucosal color, and a restored unobstructed laryngeal airway. At 28 days, the reconstructed laryngeal cavity remained unobstructed and the transplanted cartilage maintained its position. HE staining showed favorable survival of the pectoralis major composite flap and transplanted tracheal cartilage.
Conclusion: Short-term restoration of laryngeal structure and swallowing and respiratory function can be achieved using tracheal cartilage vascularized with a pectoralis major flap.
Keywords: laryngotracheal stenosis; vertical hemilaryngeal defect; laryngotracheal reconstruction; vascularized tracheal cartilage; pectoralis major flap.
Introduction
Laryngeal trauma and tumor excision are prevalent causes of laryngeal defects. Firstly, laryngeal trauma is a frequent occurrence owing to the prominent position of the larynx on the central surface of the neck. The crux of the surgical management of laryngeal trauma lies in the prompt removal of necrotic lesions and the repair of laryngeal defects to reinstate the physiological functions of the larynx [1]. When laryngeal trauma is accompanied by infection, functional reconstruction of the larynx is contraindicated in the initial stage and can be carried out after the infection has been treated [2]. Secondly, laryngectomy for laryngeal tumors frequently leads to a laryngeal defect [3]. The repair and functional reconstruction of the laryngeal defect, in conjunction with the complete resection of the tumor, can preserve laryngeal functions such as respiration, articulation, and protection of the lower airway, thereby enhancing the patients' quality of life [4].
Autologous tissue presents the merits of straightforward sampling, a high survival rate, and non-immunogenicity; consequently, it is being increasingly employed in laryngeal functional reconstruction [4–6]. At present, the pectoralis major flap, supraclavicular artery island flap, and free tissue transfer are among the autologous materials commonly utilized for repairing laryngeal defects [3, 7–11]. These restorative materials possess their respective indications and are regarded as suitable for the repair of various partial laryngeal defects, such as the repair of subtotal laryngeal defects, as well as horizontal and vertical hemilaryngeal defects. Despite continuous progress, the current clinical laryngeal reconstruction methods still depend on the posterior plate of the entire cricoid cartilage, and there remains no satisfactory surgical approach for an entire half-laryngeal defect (including the cricoid cartilage on one side) resulting from trauma or radical tumor resection [12].
The mucosal epithelium of the larynx exhibits structural and functional similarities to that of the trachea, which, in theory, renders the tracheal mucosal epithelium the most appropriate tissue for laryngeal defect reconstruction [13]. Nevertheless, there are few relevant experimental and clinical investigations in this domain. It is well-established that free tracheal cartilage lacks blood supply and is highly prone to ischemic necrosis. To utilize tracheal cartilage for repairing a laryngeal defect, a tissue flap with an ample blood supply should first be employed to establish the blood supply to the tracheal cartilage. The pectoralis major flap is one of the most frequently used tissue flaps for laryngeal defect reconstruction. This flap has the advantage of an abundant blood supply and a large tissue volume. It is also in close proximity to the myocutaneous flap of the neck and can offer a favorable vascular bed. However, to the best of our knowledge, there are no reports on the repair of horizontal or vertical hemilaryngeal defects using tracheal cartilage vascularized with the pectoralis major flap. In this study, we experimentally repaired a vertical hemilaryngeal defect in an animal model using tracheal cartilage vascularized with a pectoralis major flap. A positive outcome would provide an experiment-based approach to laryngeal defect reconstruction.
Methods
Nine Beagle dogs (male, approximately 2 years old, and weighing approximately 15 kg) were provided by the Animal Center of the Second Military Medical University [license number: SCXK (Shanghai) 2012-0007]. The ethics committee of Changhai Hospital approved the experiment. The dogs were individually housed in standard cages under controlled temperature (20-22℃), with a constant 12-hour light/dark cycle and unrestricted access to food and water.
Preparation for Animal Surgery
All procedures were carried out under general anesthesia (1 ml/kg 3% sodium pentobarbital, i.v.). Oxygen was administered via a face mask, and the animals were monitored with pulse oximetry. The neck and chest were depilated with a 10% NaS solution. All microsurgical dissections were performed under ×2.5 magnification loupes and an operating microscope.
Vertical Hemilaryngeal Defect Reconstruction Using Pectoralis Major Flap-Vascularized Tracheal Cartilage
First-stage prefabrication of vascularized tracheal cartilage
After disinfection and draping, a radial incision was made along the midline of the neck from the lower margin of the thyroid cartilage to the suprasternal fossa. The strap muscles were then separated from the midline to expose the larynx and trachea, while preserving the blood vessels and nerves. A diagonal chest incision was made from the intersection of the right midclavicular line and the lower edge of the clavicle to expose the pectoralis major muscle, which was dissected along the side of the sternum and retracted laterally to create a pectoralis major muscle flap approximately 5 cm wide and 25 cm long. The pedicled pectoralis major muscle flap was tunneled through the subclavian region to the inferior border of the first tracheal ring, wrapped around the 3rd–5th tracheal cartilages to cover an approximately 4-cm tracheal segment, and secured to the tracheal membrane with 3-0 absorbable sutures as a vascular carrier (Figure 1A-B). Finally, the surgical cavity was sequentially irrigated, a negative pressure tube was inserted, and the wound was closed.
Second-stage creation of the vertical hemilaryngeal defect
After the three-week prefabrication step to vascularize the tracheal cartilage, vertical hemilaryngeal defect reconstruction was performed. The preoperative preparation was the same as that for the first-stage surgery. The cervical skin was incised, and the pedicled pectoralis major muscle-tracheal cartilage flap was cut from the lower edge of the first tracheal ring to the 4th or 5th tracheal rings, producing a flap length of approximately 4 cm (Figure 1C). The right hemilarynx, including the thyroid cartilage plate, arytenoid cartilage, and periglottic space, was removed vertically to prefabricate a hemilaryngeal defect model (Figure 1D).
Reconstruction of the vertical hemilaryngeal defect
An end-to-end anastomosis of the remaining trachea was performed, and a tracheostomy was fixed to the skin below the anastomosis. The trachea with the muscle flap was sutured to the remaining left part of the larynx, and the lower edge was sutured to the first tracheal ring (Figure 1E-F). The surgical cavity was irrigated routinely, and a disposable suction bulb was inserted in the neck. The cervical skin incision was closed, and a 14 mm metal tracheal cannula was inserted into the tracheostomy.
Figure 1. Surgical procedure for vertical hemilaryngeal defect reconstruction with vascularized tracheal cartilage using a pectoralis major flap.
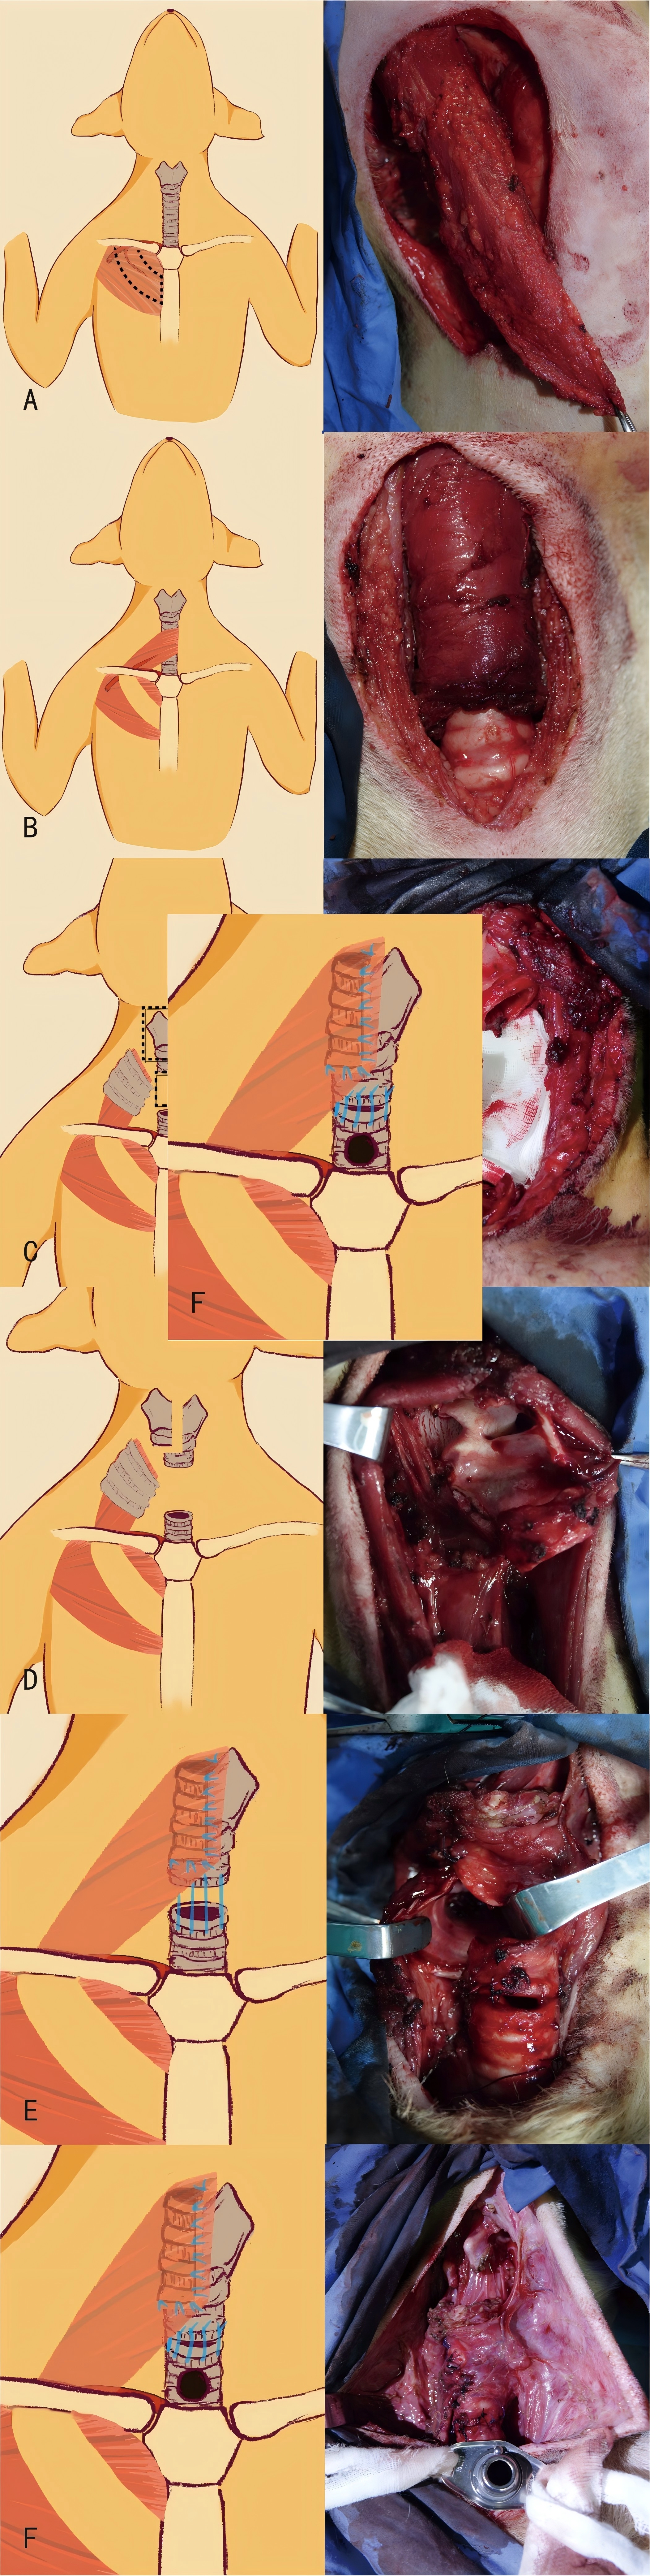
(A) The pectoralis major muscle and thoraco-acromial artery. (B) The pedicled pectoralis major muscle flap wrapped around the tracheal cartilage. (C) The trachea was cut to create a pedicled pectoralis major muscle-tracheal cartilage flap. (D) The right hemilarynx was resected vertically. (E) The trachea with muscle flap was sutured to the remaining left larynx. (F) End-to-end tracheal anastomosis and lower tracheostomy. PMF, pectoralis major flap; TC, tracheal cartilage.
Postoperative Care
Following the surgical procedure, the canine subject was maintained in a thermally regulated environment and permitted to regain consciousness spontaneously upon the dissipation of the anesthetic effect. To mitigate the risk of infection throughout the experimental period, all animals received a course of antibiotic therapy (penicillin, 1.6 million units per day) for a duration of one week. An anti-bite collar was affixed around the dog's cervical region to preclude any interference with the surgical wound, and the metal inner housing was subjected to daily cleaning and disinfection using sputum aspiration techniques. Subsequent to the initial stage of surgery, the dogs were provided with a standard diet, and enteral nutrition suspension was administered via a nasogastric tube subsequent to the second stage of the surgical intervention.
Postoperative Monitoring and Assessment
Definition of Primary Endpoints
Successful extubation was defined as tracheostomy tube occlusion for 48 h without dyspnea, stridor, or desaturation (SpO2 ≥ 95% on room air), according to standard veterinary tracheostomy decannulation criteria [14–15] and previous canine laryngeal reconstruction studies [16]. Normal feeding was defined as the ability to consume solid kibble without coughing, aspiration, or leakage from the tracheostomy site for 3 consecutive days, consistent with established postoperative functional assessment in canine head and neck models [16].
Evaluation of swallowing and respiratory function
Seven days after surgery, we gave fluid feedings to check for any food exudation in the tracheotomy hole as well as to check for the presence of coughing during drinking and eating. We recorded recovery based on the time required for swallowing function and changed to normal feeds if there was no choking or pharyngeal fistula. Fourteen days post-operatively, the tracheal tubes were occluded for 2 days and removed if no difficulty in deglutition or breathing was noted.
Computed tomography examination of the larynx and video laryngoscopy examination
Computed tomography (CT) and video laryngoscopy were performed under general anesthesia at the following time points: preoperatively, immediately postoperatively, and 28 days postoperatively. CT scans were obtained in 1-mm slices. After each iteration of the laryngeal CT scan, a video laryngoscope was advanced through the glottis via the direct laryngoscope to observe the new half-laryngeal mucosa, laryngeal and tracheal cavities, suture healing, and surface color and luster.
Histologic evaluation
The experimental dogs were euthanized by intravenous injection of KCl after anesthesia, and the reconstructed laryngeal tissue specimens were paraffin-embedded and subjected to hematoxylin-eosin (HE) staining.
Results
Postoperative survival and functional recovery
Table 1 shows the normal feeding time, postoperative survival time, and extubation time of the nine experimental dogs. All dogs survived the surgeries, but dog #7 developed a postoperative infection, resulting in a local neck abscess. The abscess was treated with incision and drainage, followed by wound dressings, and eventually healed completely. All dogs were observed and evaluated for 28 days after the surgery. Among the surviving animals, the median time to resumption of normal feeding was 16 days (range: 14-17 days), and the median time to successful decannulation was 18 days (range: 16-21 days) (Table 1).Their swallowing difficulties were relieved at different time points after the surgery, and they were successfully extubated to resume normal feeding.No respiratory distress after extubation in all dogs except dog #7.
Dog #7 developed a localized cervical abscess on postoperative day 10, which was managed with incision and drainage plus daily dressing changes. Histology showed excessive scar proliferation and poor cartilage survival on the operative side, leading to persistent airway stenosis and failed extubation. This case highlights that postoperative infection is a critical risk factor for graft failure; strict aseptic technique, prolonged antibiotic prophylaxis, and tension-free anastomosis are recommended to minimize this complication.
Table 1. The normal feeding time, postoperative survival time and extubation time of the experimental dogs.
| Serial number | Weight (Kg) | Survival time | Postoperative extubation time | Normal feeding time after surgery |
|---|---|---|---|---|
| 1 | 14.5 | 28 d | 18 d | 16 d |
| 2 | 16.0 | 28 d | 17 d | 16 d |
| 3 | 15.0 | 28 d | 20 d | 16 d |
| 4 | 17.0 | 28 d | 21 d | 17 d |
| 5 | 16.0 | 28 d | 17 d | 15 d |
| 6 | 16.5 | 28 d | 16 d | 14 d |
| 7 | 13.5 | 28 d | * | 18 d |
| 8 | 15.5 | 28 d | 18 d | 17 d |
| 9 | 15.0 | 28 d | 17 d | 15 d |
Note: * No extubation.
Video laryngoscopy findings
One day after surgery, video laryngoscopy revealed complete removal of the right vocal cord. Furthermore, we could see that the tracheal wall was convex outwardly and had a smooth mucosa. It was noted that the larynx and the lower edge of the first tracheal ring were well anastomosed, and the metal tracheal tube was in place (Figure 2). On postoperative day 28, video laryngoscopy confirmed normal movement of the left arytenoid cartilage. In addition, the right tracheal mucosa was pale pink in appearance, and a well-supported and intact laryngeal chamber was noted. There was a small amount of white secretion adhering to the mucosal surface, and the laryngeal and tracheal cavities showed no obvious granulation hyperplasia (Figure 3).
Figure 2. Immediate postoperative video laryngoscopy.
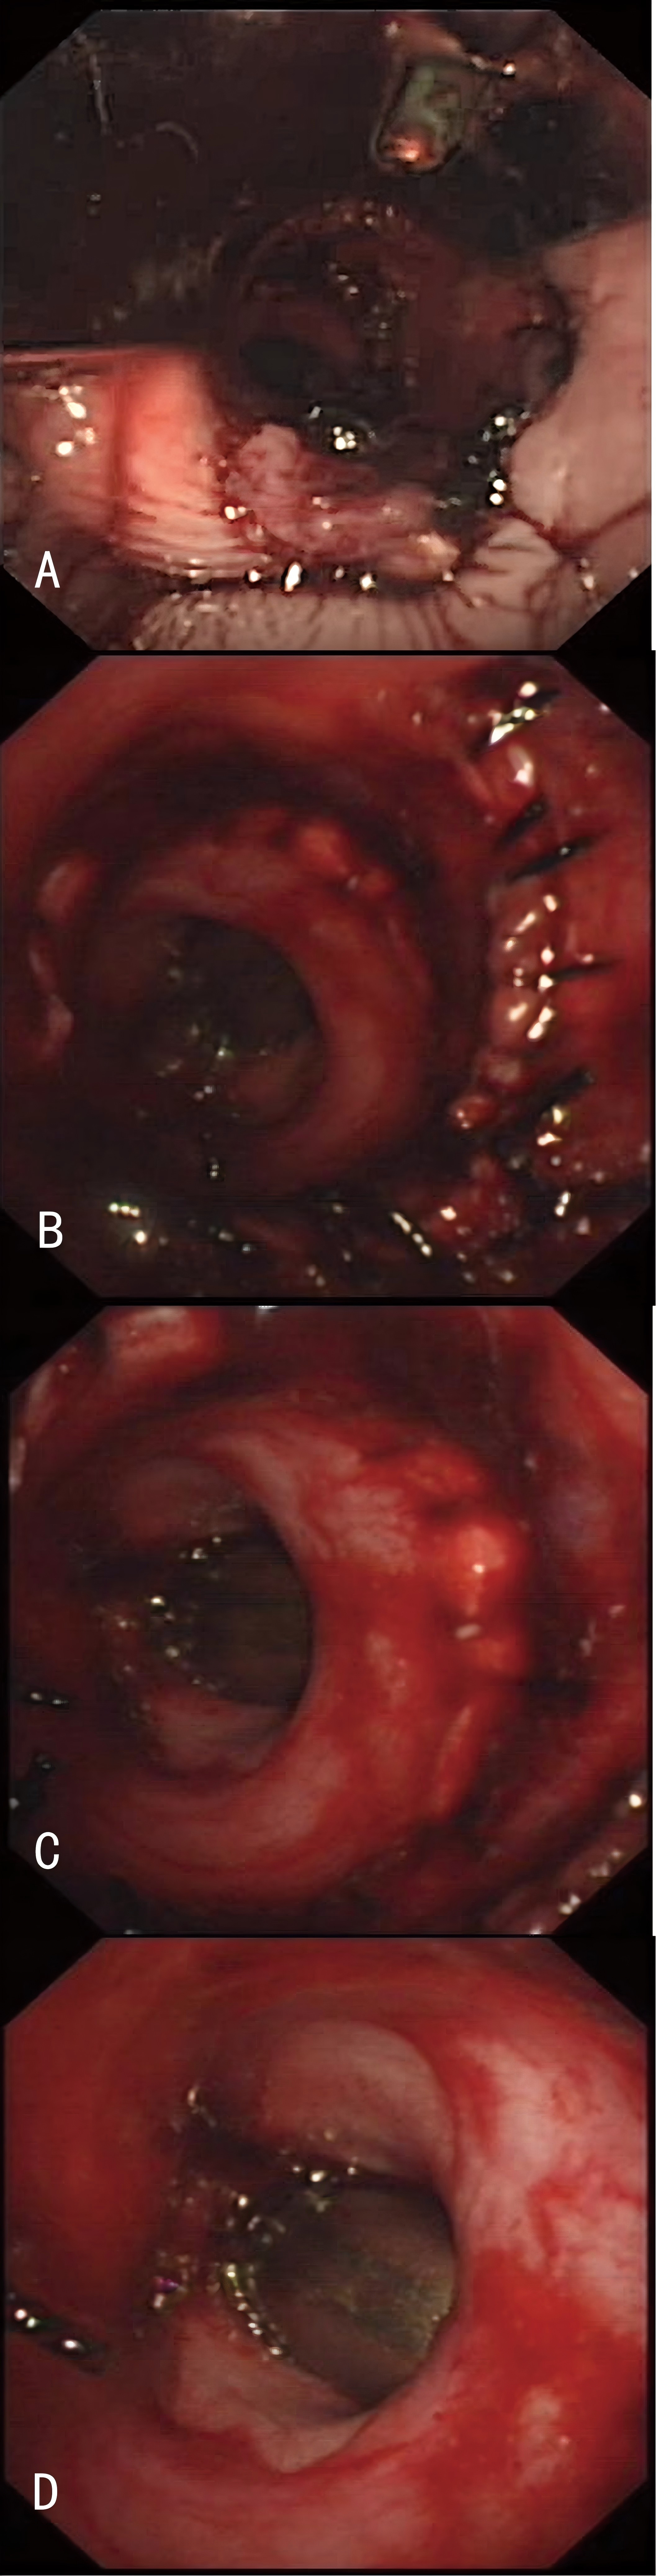
(A) Immediate postoperative findings. (B) Glottic inlet and suture line. (C) Anastomosis at the upper margin of transplanted tracheal cartilage. (D) Anastomosis at the lower margin and end-to-end tracheal anastomosis.
Figure 3. Video laryngoscopy findings at 28 days postoperatively.
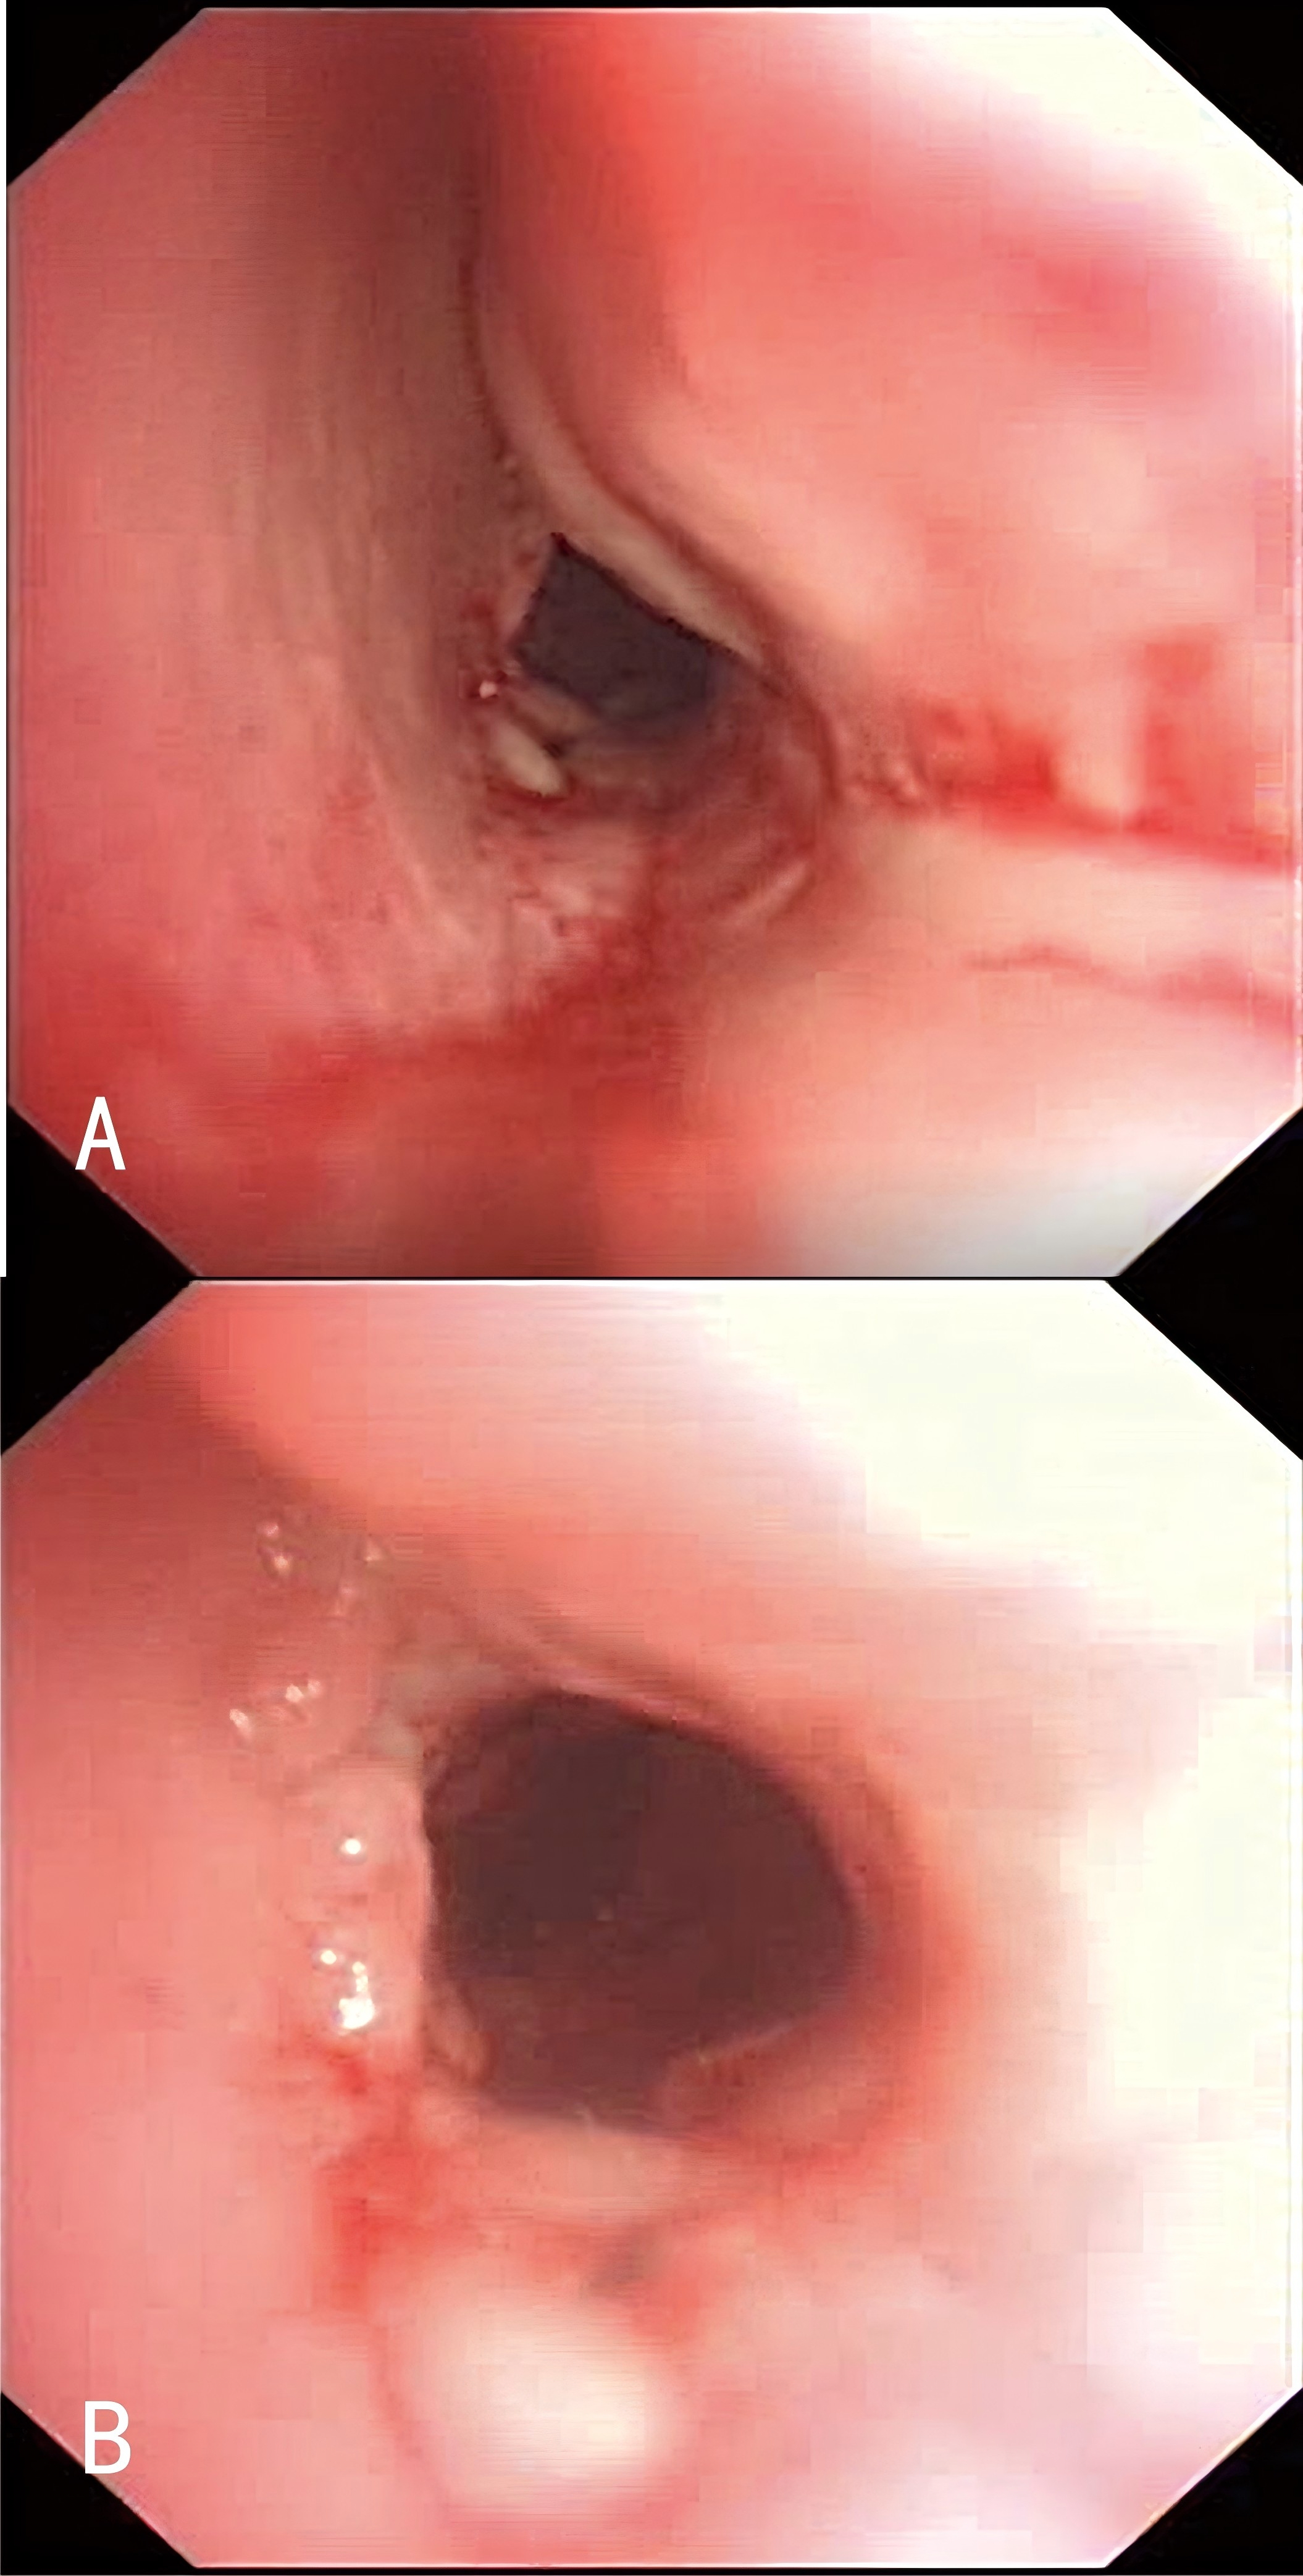
(A) Glottic entrance. (B) Laryngotracheal anastomosis site. The video shows slightly edematous mucosa, a well-supported laryngeal cavity without collapse, and well-healed anastomosis without obvious granulation.
CT examination results and analysis of the larynx and trachea
In this case, CT images of the larynx taken immediately post-operatively showed the semicircular tracheal cartilage of the right graft segment as well as the anastomosis with the left larynx. Post-operatively, an excessive fluid density shadow was observed in the laryngeal cavity, indicating the formation of a gas-liquid level (Figure 4A-B). Next, a CT scan of the larynx 28 days post-operatively showed an unobstructed laryngeal cavity and well-supported right reconstructed laryngeal cartilage (Figure 4C-D).
Figure 4. Postoperative CT images of the larynx.
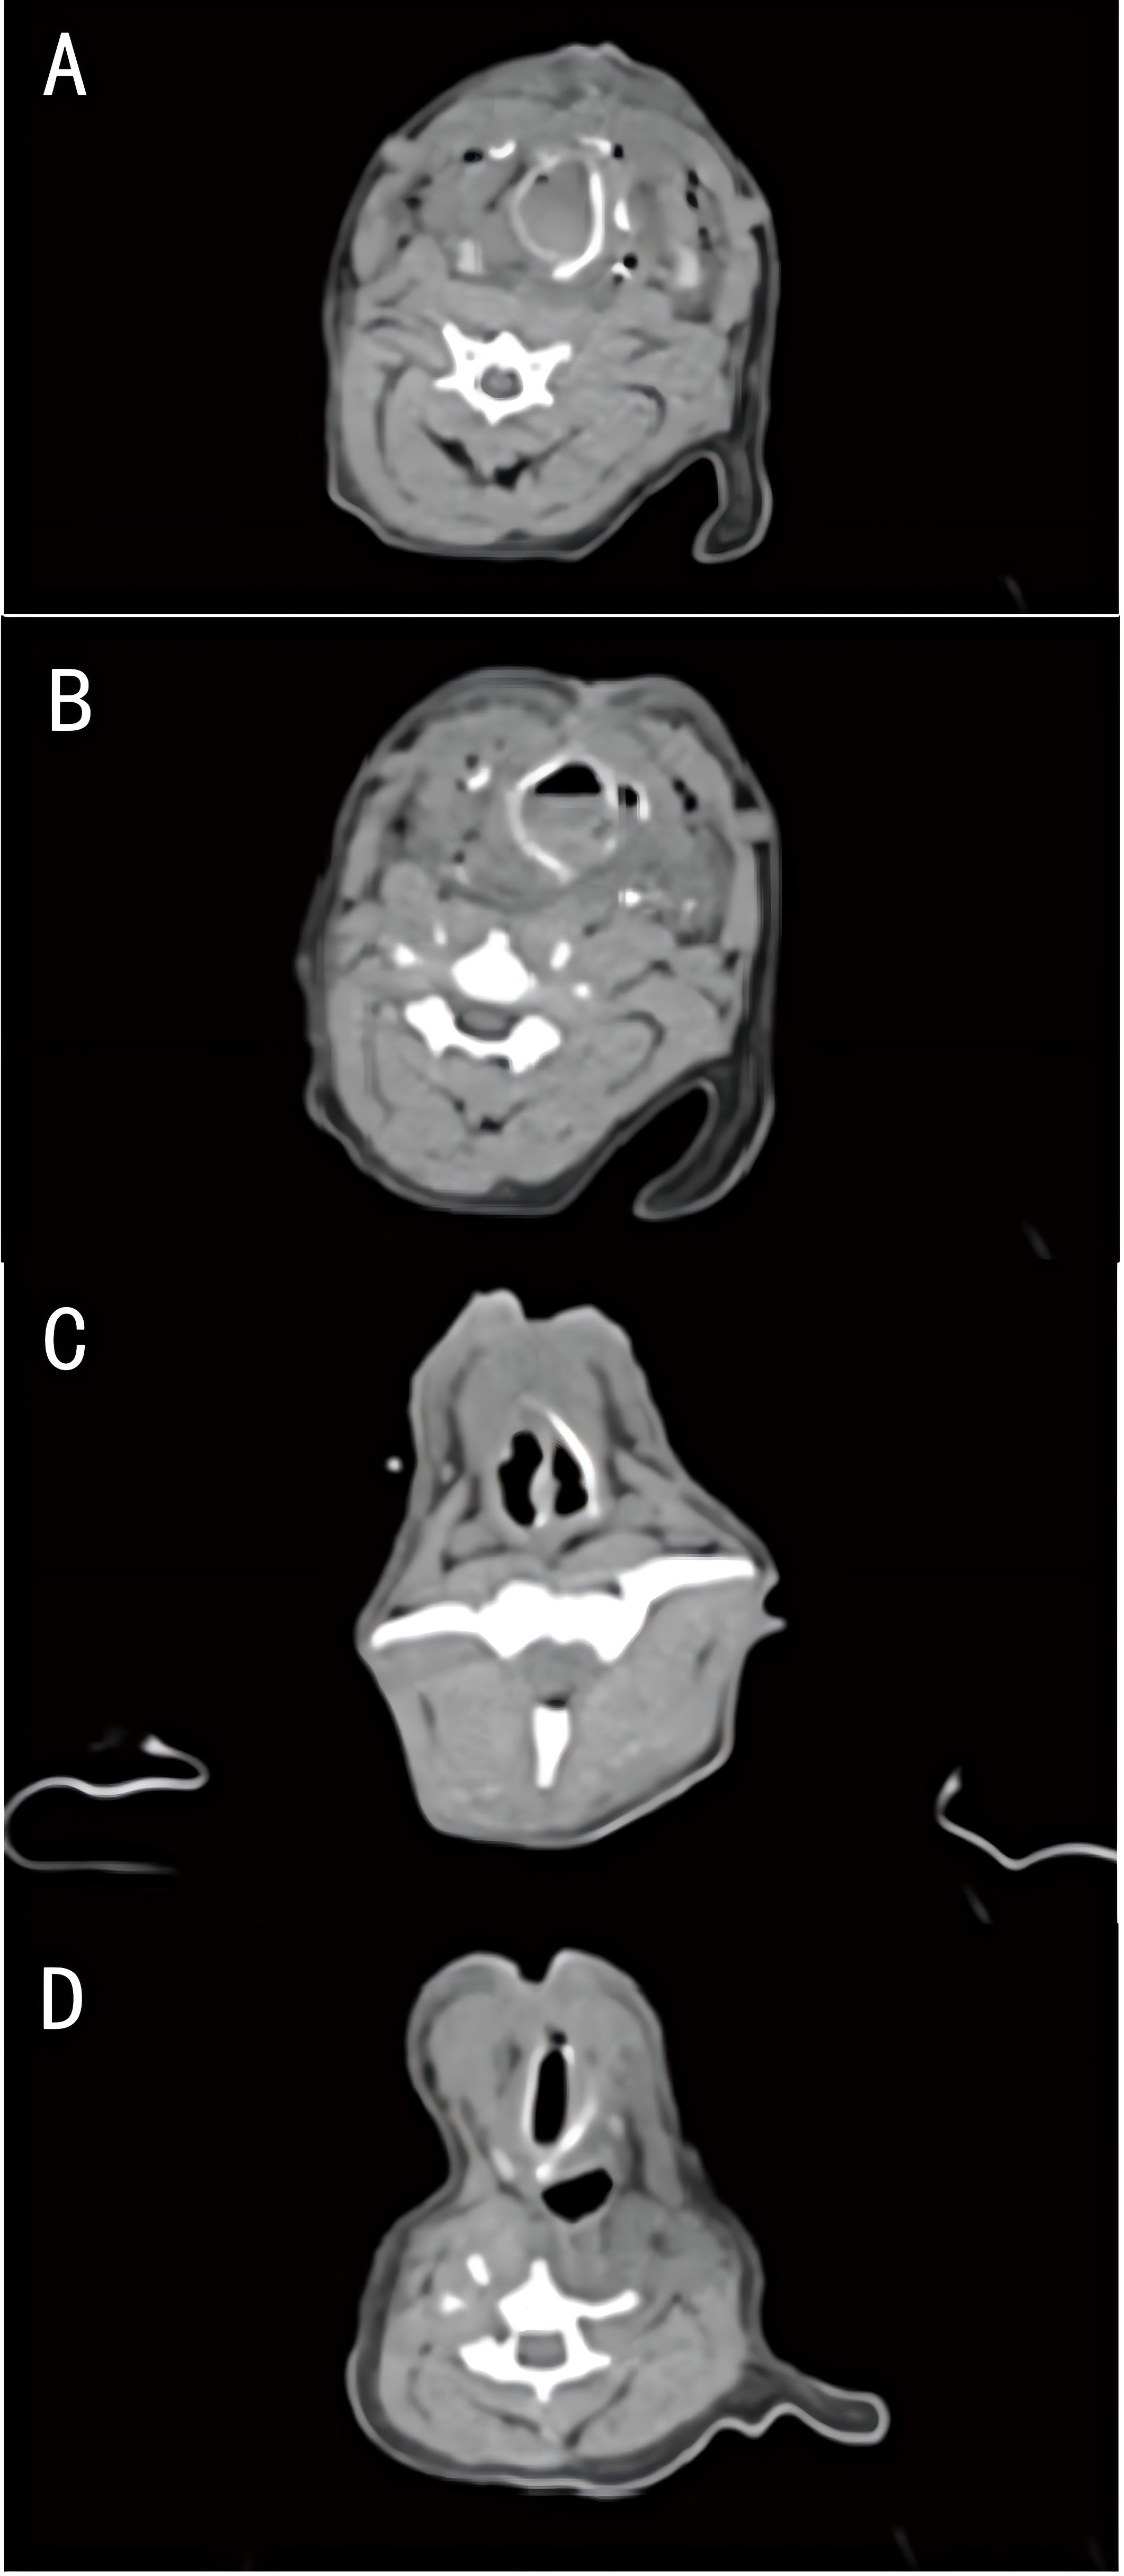
(A, B) Immediate postoperative images showing the semi-arc-shaped transplanted tracheal cartilage segment and a gas-fluid level in the laryngeal cavity. (C, D) CT images at 28 days demonstrating a patent laryngeal cavity and well-supported reconstructed laryngeal cartilage.
Histological results and analysis
Eight dogs were extubated, and complete histologic data at 28 days were available for all eight dogs. The histologic findings for the reconstructed hemilarynx of the eight dogs showed restoration of good tracheal cartilage structure and mucosal structure on the operative side of the hemilarynx, which did not appear significantly different from the laryngeal cartilage on the normal side (Figure 5A-B). However, extubation failed in one dog (dog 7), and this dog had more scar and connective tissue, significantly poor healing, and poor cartilage structure on the operative side of the larynx.
Figure 5. Hematoxylin and eosin staining of laryngeal tissue at 28 days postoperatively.
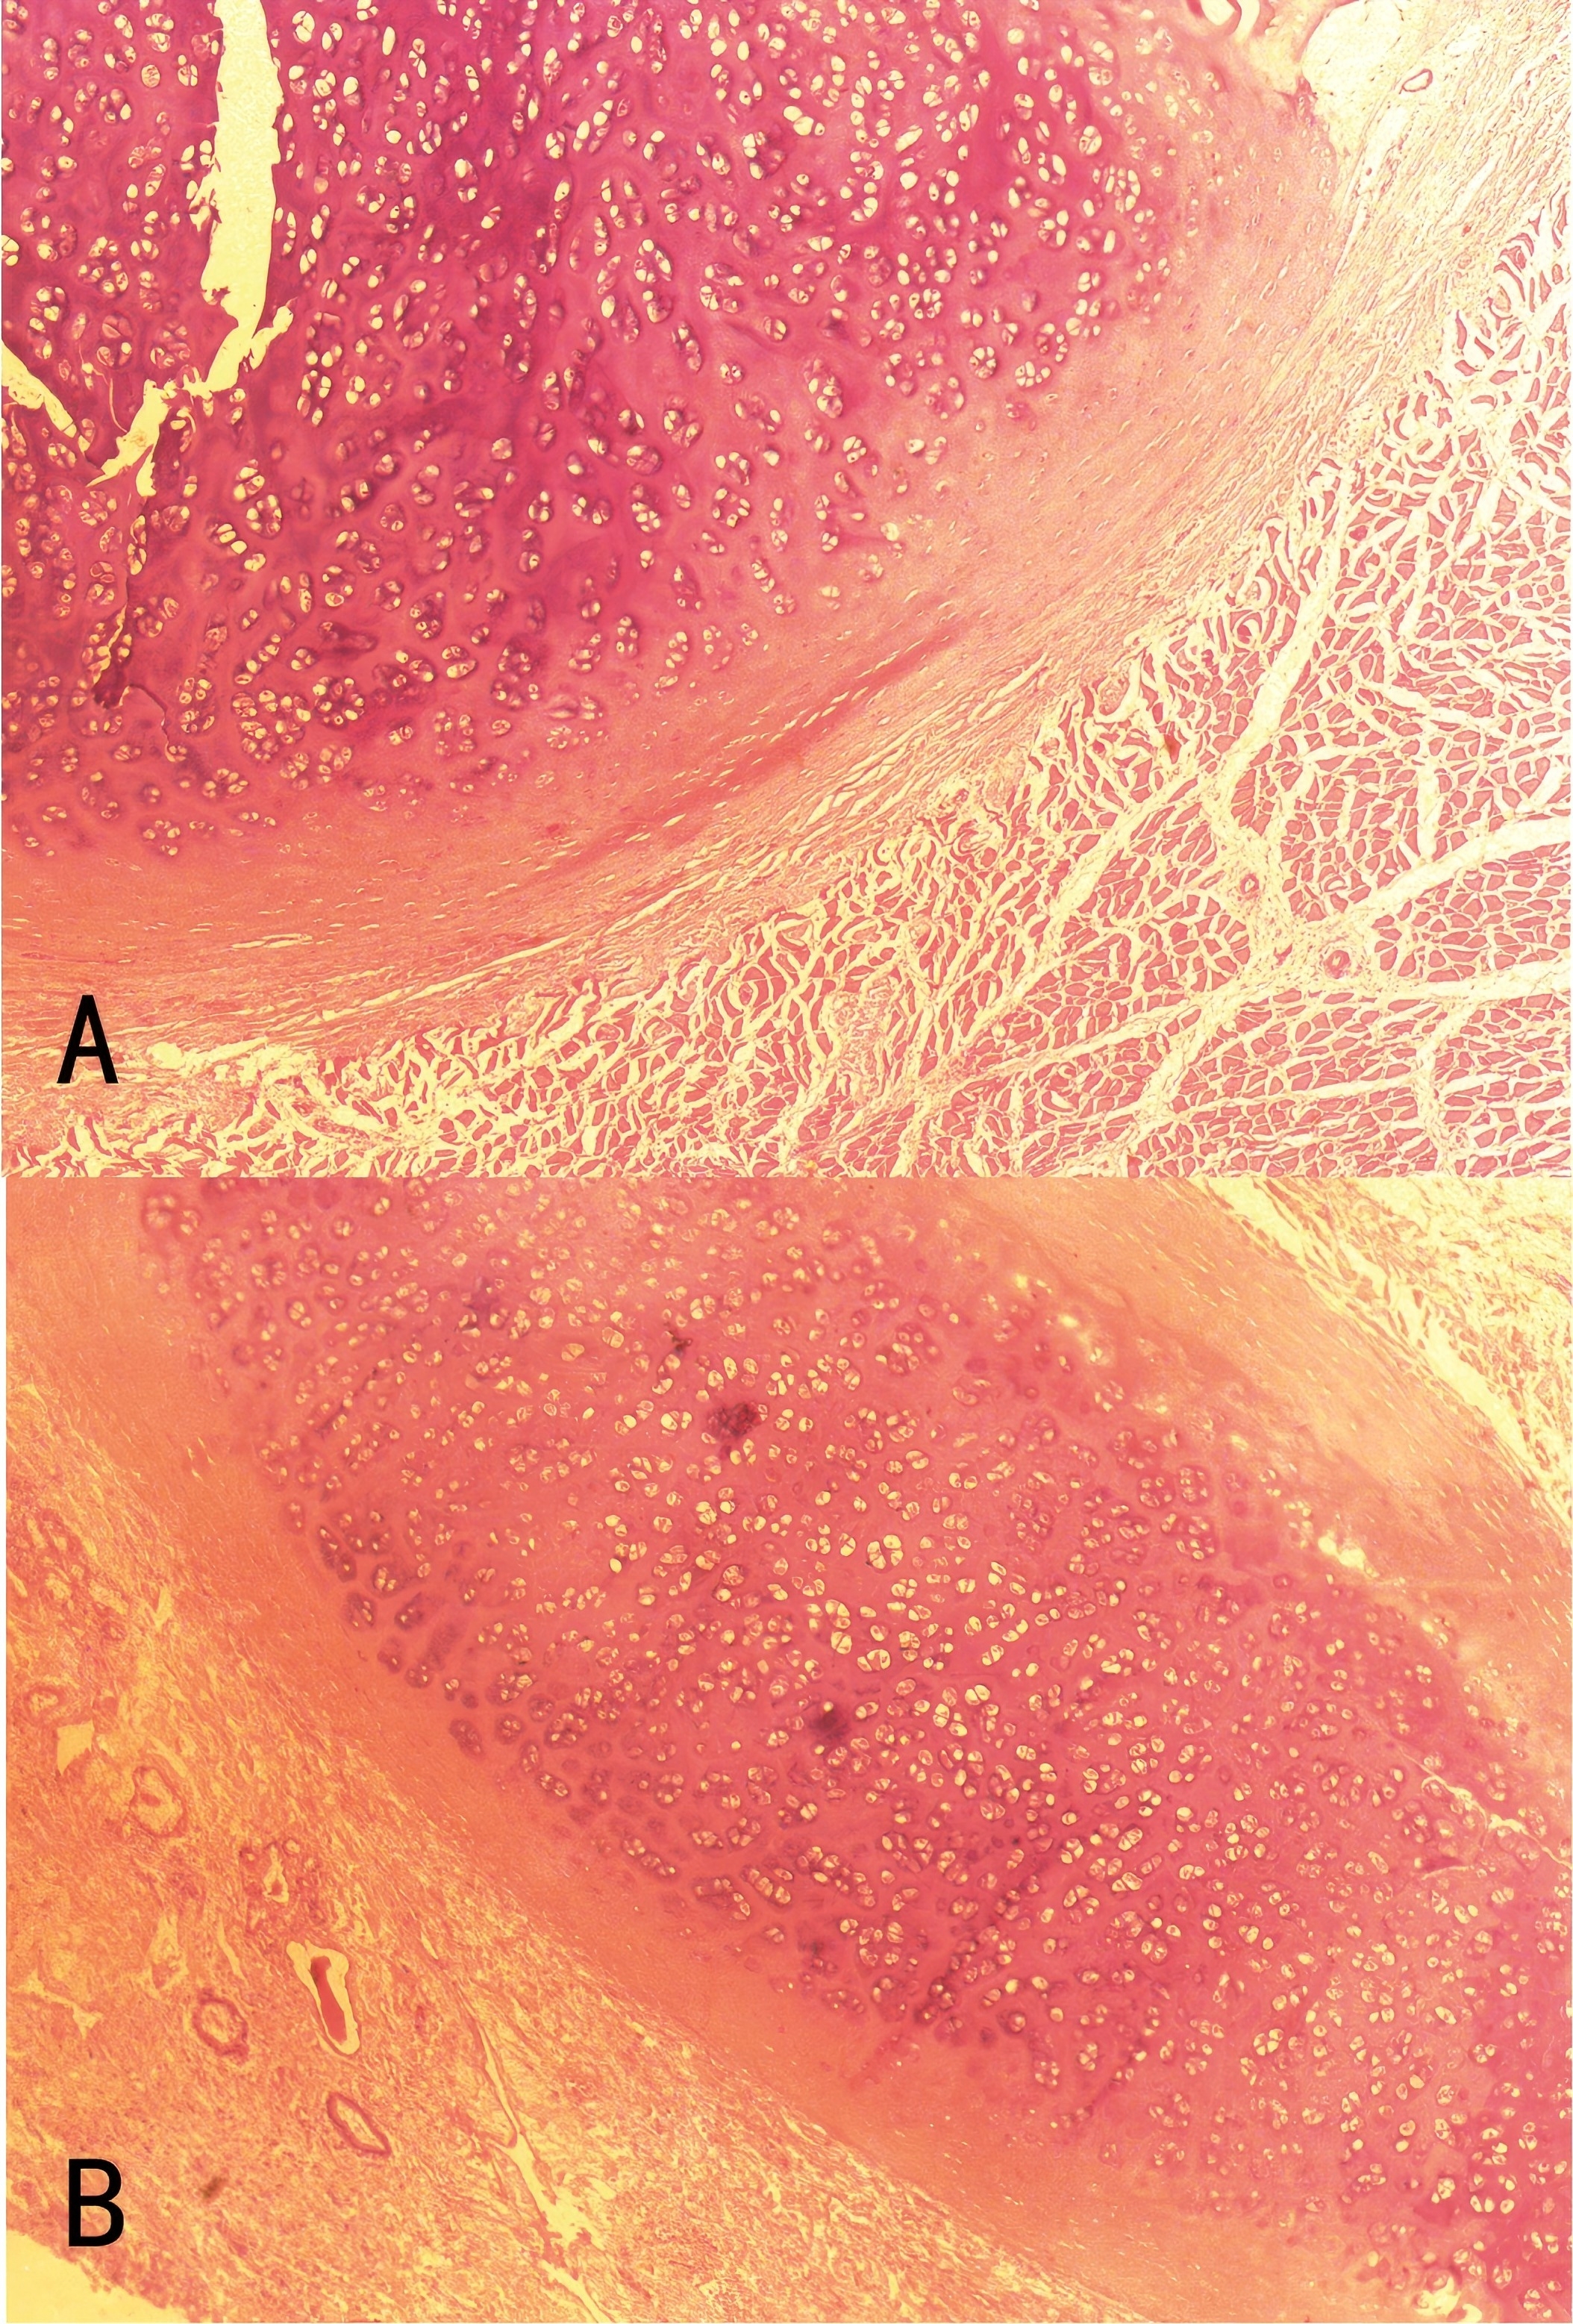
(A) Normal side of the hemilarynx. (B) Operative reconstructed side, showing restored tracheal cartilage and mucosal structures.
Discussion
Adequate cartilaginous support of the airway is essential for the repair of laryngeal defects, and a relatively complete posterior plate of cricoid cartilage is essential to avoid uncompensated aspiration. Despite recent advances in the field of laryngotracheal reconstruction, current clinical approaches in this area require a complete posterior plate of cricoid cartilage [12].Therefore, there is still no satisfactory repair approach for a trauma- or radical tumor treatment-induced entire hemi-laryngeal defect that includes the cricoid cartilage on one side. For cartilaginous tissue reconstruction, the costal cartilage is clinically the most widely used tissue [17–19];however, its application in laryngeal defect reconstruction is limited by some of its characteristics, such as difficulties in vascularization and its long and narrow shape. Instead, the tracheal cartilage adjacent to the larynx, which has a support resembling a C-shaped hose ring, is well suited for laryngeal defect reconstruction. Because of the similarity between its internal epithelium and the laryngeal epithelium and the ease of epithelialization, the likelihood of granulation hyperplasia formation is reduced [13].The shape, structure, and function of the airway and the internal mucosal epithelium are theoretically identical, making the trachea vascularized by a pectoralis major flap the most suitable option for reconstructing laryngeal defects and ensuring blood supply to the reconstructed tissue; however, this is supported by few relevant experimental and clinical studies. The main reason for this gap in the literature is that the reconstructed laryngeal tissue after tracheal cartilage transfer to the larynx requires a vascularized tissue flap to provide blood supply.
Some researchers have reported the use of free omentum to wrap the trachea and reconstruct laryngeal defects, followed by using small blood vessel anastomosis to provide blood supply to the reconstructed tissue. However, the free-flap technique is complex, and the chances of complications further limit its application. The pectoralis major flap is among the most commonly used tissue flaps for laryngeal defect reconstruction [10].The advantages of this flap include large tissue volume and abundant blood supply, and its proximity to the neck, which can provide an ideal vascular bed for the tracheal cartilage [20].The experimental design of this project aimed to solve the problems of vascularization and epithelialization of the graft. Therefore, we chose to use tracheal cartilage vascularized with the pectoralis major flap for laryngeal reconstruction.
According to our experimental animal model using Beagle dogs, we observed that eight of nine dogs were successfully extubated and their dysphagia gradually resolved over time, allowing them to eat normally. The experimental results suggested a high success rate for the surgical procedure. On day 7, we attempted to feed the dogs a liquid diet to exercise and restore swallowing function, but some dogs experienced varying degrees of coughing and leakage of liquid food from the fistula tube. However, they were typically able to eat normally at an average of 16 days after surgery, and the tracheal tube could be removed at an average of 18 days. Immediate electronic laryngoscopy after surgery showed a smooth laryngotracheal cavity after reconstruction, with normal mucosal color and well-sutured anastomosis between the residual larynx and the transplanted trachea. Long-term postoperative findings also showed normal color of the mucosal epithelium of the tracheal cartilage in the right graft segment, consistent with the surrounding laryngeal tissue, and no obvious granulation formation. In addition, the laryngeal cavity was unobstructed, indicating sufficient mucosal blood supply and well-preserved mucosal clearance function. CT scans of the throat showed that in the early postoperative period, the transplanted tracheal cartilage segment had a semi-arc shape, causing an enlarged laryngeal cavity and an increased risk of aspiration during swallowing. In the later period, the tracheal cartilage of the transplanted segment formed a good laryngeal support structure with the left residual thyroid cartilage and cricoid cartilage, reconstructing a smooth laryngeal cavity. The curvature of the transplanted tracheal cartilage segment decreased with compensatory movement of the left arytenoid cartilage, resulting in a reduced laryngeal cavity and decreased risk of aspiration, leading to the restoration of swallowing function. In this study, dog #7 developed a localized neck abscess postoperatively. Although it healed completely with drainage and dressings. This dog had more scar and connective tissue, significantly poorer healing, and poor cartilaginous structure on the surgical side of the larynx, which eventually led to failed extubation. Therefore, postoperative anti-infective treatment should be intensified, and tension on the anastomosis should be reduced.
Based on the above results, when reconstructing and repairing a vertical hemilaryngeal defect, the structure and function of the larynx can be satisfactorily restored using the pectoralis major flap in combination with tracheal cartilage. The following aspects should be considered when performing the operation: First, a period of 3 weeks was required for complete vascularization of the tracheal cartilage after the first-stage operation. Second, in the first-stage operation, the pectoralis major flap must be wrapped downward from the first tracheal ring. With a low wrapping position, the pectoralis major flap may not be long enough for the second-stage reconstruction, causing excessive anastomotic tension in the larynx. Third, the trachea must be appropriately trimmed according to the size of the defect to achieve an adequate laryngeal cavity. Fourth, during reconstruction, every step should be taken to avoid infection and inflammatory reaction, so that fibrosis or necrosis of the transplanted larynx can be avoided.
However, this study has several limitations. First, the small sample size (n=9) and absence of a control group (e.g., rib cartilage reconstruction comparator) limit the strength of conclusions. Second, the 28-day follow-up only reflects short-term feasibility, and long-term outcomes (≥6 months) regarding cartilage resorption, airway stability, and laryngeal phonatory function remain unknown. Third, swallowing and respiratory function were assessed via qualitative observation rather than validated scoring systems (e.g., Penetration-Aspiration Scale). Future studies with larger cohorts, longer follow-up, and objective functional assessments are needed to validate these preliminary findings.
Future clinical translation of this technique warrants caution. While the approach theoretically expands indications for organ-preserving surgery in select advanced laryngeal cancers, the current 3-week prefabrication interval conflicts with standard oncologic principles requiring immediate tumor resection. Potential solutions include simultaneous neck dissection with induction chemotherapy during the prefabrication stage, or adopting single-stage designs with prevascularized tissue-engineered grafts. These hypotheses require validation in tumor-bearing animal models prior to human trials. We believe that future breakthroughs in laryngeal defect repair technology will come from advanced techniques such as 3D printing of the repair laryngeal cartilage [6, 21].Joanna F et al. fabricated a polycaprolactone scaffold using 3D printing technology and coated it with porcine-derived small intestinal submucosa extracellular matrix. The resulting bioengineered graft was transplanted into experimental pigs to replace a 2-cm segment of the trachea. The experimental results showed that loading the small intestinal submucosa extracellular matrix on the surface of the graft could promote a good integration of the graft with the natural organ [22].This exploration of constructing multifunctional organ prostheses using the scaffold-free approach holds great promise for bringing about a major breakthrough in the field of biological reconstruction of the laryngeal defect [23].These will provide new ways to reconstruct laryngeal mucosal tissue and help restore laryngeal function by reconstructing the laryngeal structure. Certainly, there is still a long way to go before these advances are realized, as there are many technical problems that need to be solved.
In conclusion, this pilot study demonstrates that vertical hemilaryngeal defects (including unilateral cricoid cartilage defects) can be successfully reconstructed using pectoralis major flap-vascularized tracheal cartilage, with satisfactory short-term restoration of laryngeal structure and swallowing/respiratory function. The technique does not require a laryngeal mould due to the spacious postoperative airway, and offers a high success rate of extubation. Further studies are warranted to validate long-term outcomes and expand the clinical applicability of this approach.
Conclusion
This preliminary investigation demonstrates that short-term restoration of laryngeal structure and swallowing/respiratory function can be achieved through the reconstruction of vertical hemilaryngeal defects (including involvement of the unilateral cricoid cartilage) using tracheal cartilage vascularized with a pectoralis major flap.
Abbreviations
Fangzheng Yi: Conceptualization, Investigation, Methodology,Writing - original draft, Writing - review & editing. Mengjie Chen:Conceptualization,Investigation, Writing - original draft, Writing - review & editing. Jing Song:Writing - original draft, Writing - review & editing. Guanghao Zhu:Investigation, Writing - original draft. Tianxiang Zhu, Haopu Li, Haojun Yu:Data curation,software.Hongliang Zheng & Minhui Zhu:Conceptualization,Funding acquisition,Methodology,Resources,Supervision.All authors read and approved the final manuscript.
This study was conducted in strict accordance with the Guide for the Care and Use of Laboratory Animals (National Research Council, 8th edition, USA). The animal experiments were approved by the Ethics Committee of Changhai Hospital. The Beagle dogs were provided by the Animal Center of the Second Military Medical University [license number: SCXK (Shanghai) 2012-0007]. All procedures were performed under general anesthesia to minimize animal suffering. The study did not involve human participants; therefore, informed consent was not applicable.
Not Applicable.
The authors declare that they have no existing or potential commercial or financial relationships that could create a conflict of interest at the time of conducting this study.
Not Applicable.
Not Applicable.
Abbreviations
3D: Three-dimensional; CT: Computed tomography; HE: Hematoxylin and eosin; i.v.: Intravenous; KCl: Potassium chloride; NaS: Sodium sulfide; SCXK: Laboratory Animal Production License; SpO₂: Peripheral capillary oxygen saturation.
Declarations
Author Contributions
Fangzheng Yi: Conceptualization, Investigation, Methodology, Writing - original draft, Writing - review & editing. Mengjie Chen: Conceptualization, Investigation, Writing - original draft, Writing - review & editing. Jing Song: Writing - original draft, Writing - review & editing. Guanghao Zhu: Investigation, Writing - original draft. Tianxiang Zhu, Haopu Li, Haojun Yu: Data curation, software. Hongliang Zheng and Minhui Zhu: Conceptualization, Funding acquisition, Methodology, Resources, Supervision. All authors read and approved the final manuscript.
Acknowledgements
Not Applicable.
Funding information
Not Applicable.
Ethics Approval and Consent to Participate
This study was conducted in strict accordance with the Guide for the Care and Use of Laboratory Animals (National Research Council, 8th edition, USA). The animal experiments were approved by the Ethics Committee of Changhai Hospital. The Beagle dogs were provided by the Animal Center of the Second Military Medical University [license number: SCXK (Shanghai) 2012-0007]. All procedures were performed under general anesthesia to minimize animal suffering. The study did not involve human participants; therefore, informed consent was not applicable.
Competing Interests
The authors declare that they have no existing or potential commercial or financial relationships that could create a conflict of interest at the time of conducting this study.
Data availability
Not Applicable.
References
[1] Akali NR, Jaya AC, Balasubramanian D, Iyer S, Thankappan K. Islanded facial artery musculo-mucosal flap for partial pharyngeal defect reconstruction after total laryngectomy: Case report. Head Neck-J Sci Spec Head Neck. 2021;43(1):E1-E6. https://doi.org/10.1002/hed.26522
[2] DePorre AR, Schechtman SA, Hogikyan ND, Thompson A, Westman AJ, Sargent RA, et al. Airway Management and Clinical Outcomes in External Laryngeal Trauma: A Case Series. Anesth Analg. 2019;129(2):E52-E4. https://doi.org/10.1213/ANE.0000000000003843
[3] Hayden RE, Chang BA, Mullin DP, Patel AK, Nagel TH, Howard BE, et al. Bipedicled submental musculofascial "hammock" flap for salvage laryngectomy closure reinforcement. Head Neck-J Sci Spec Head Neck. 2021;43(1):198-202. https://doi.org/10.1002/hed.26473
[4] Liao CH, Huang JF, Chen SW, Fu CY, Lee LA, Ouyang CH, et al. Impact of Deferred Surgical Intervention on the Outcome of External Laryngeal Trauma. Annals of Thoracic Surgery. 2014;98(2):477-83. https://doi.org/10.1016/j.athoracsur.2014.04.079
[5] Werner J, Scaglioni MF, Ko SS, Rajan GP. Preservation of laryngeal function through reconstruction of the supraglottis and thyrohyoid membrane with a chimeric anterolateral thigh flap after supraglottic laryngectomy: A case report and literature review. Microsurgery. 2021;41(5):462-7. https://doi.org/10.1002/micr.30708
[6] Vella O, Blanchard D, de Raucourt D, Rame JP, Babin E. Function evaluation of laryngeal reconstruction using infrahyoid muscle after partial laryngectomy in 37 patients. Eur Ann Otorhinolaryngol-Head Neck Dis. 2020;137(1):7-11. https://doi.org/10.1016/j.anorl.2019.09.004
[7] Yeh DH, Sahovaler A, Fung K. Reconstruction after salvage laryngectomy. Oral Oncol. 2017;75:22-7. https://doi.org/10.1016/j.oraloncology.2017.10.009
[8] León X, López M, García J, Casasayas M, Rovira C, Quer M. Indications and results of extended total laryngectomy with en-bloc resection of overlying cervical skin. Eur Arch Oto-Rhino-Laryn. 2019;276(11):3179-84. https://doi.org/10.1007/s00405-019-05573-8
[9] Lai YS, Lee YC. Comparison of outcomes between circumferential and near-circumferential pharyngoesophageal reconstruction using anterolateral thigh flap. J Plast Reconstr Aesthet Surg. 2023;85:316-25. https://doi.org/10.1016/j.bjps.2023.07.010
[10] Kang SK, Qamar SN, Khan IM, Crosbie R, Tikka T. 10-Year Experience with the Modified Pectoralis Major Flap: The Use of the Deltopectoral Flap to Reduce Skin Tension. Indian J Otolaryngol Head Neck Surg. 2023;75(2):358-65. https://doi.org/10.1007/s12070-022-03154-6
[11] Banaszewski J, Gaggl A, Buerger H, Wierzbicka M, Pabiszczak M, Pastusiak T, et al. The reconstruction of large laryngeal defect with medial condyle femur corticoperiosteal free flapa case report. Microsurgery. 2016;36(2):157-60. https://doi.org/10.1002/micr.22509
[12] McCullagh KL, Shah RN, Huang BY. Anatomy of the Larynx and Cervical Trachea. Neuroimaging Clin N Am. 2022;32(4):809-29. https://doi.org/10.1016/j.nic.2022.07.011
[13] Mehrban N, Bowen J, Tait A, Darbyshire A, Virasami AK, Lowdell MW, et al. Silsesquioxane polymer as a potential scaffold for laryngeal reconstruction. Mater Sci Eng C-Mater Biol Appl. 2018;92:565-74. https://doi.org/10.1016/j.msec.2018.07.003
[14] Fossum TW, Dewey CW, Horn CV, et al. Small Animal Surgery. 5th ed. St Louis: Elsevier; 2019:739-756.
[15] Monnet E. Tracheostomy. In: Tobias KM, Johnston SA, eds. Veterinary Surgery: Small Animal. Vol 1. 2nd ed. St Louis: Elsevier Saunders; 2018:1563-1571.
[16] Andrews RJ, Calcaterra TC, Sercarz JA, et al. Vocal function following vertical hemilaryngectomy: comparison of four reconstruction techniques in the canine. Ann Otol Rhinol Laryngol. 1997;106(4):261-270. https://doi.org/10.1177/000348949710600401
[17] Piazza C, Paderno A, Del Bon F, Grammatica A, Montalto N, Bresciani L, et al. Fascio-cutaneous-free flaps as primary reconstruction in salvage total laryngectomy. Eur Arch Oto-Rhino-Laryn. 2021;278(1):219-26. https://doi.org/10.1007/s00405-020-06137-x
[18] Wolter NE, Vilchez-Madrigal LD, Jh JHG, Greer MLC, Peer S, Highmore K, et al. Predicting Maximal Costal Cartilage Graft Size for Laryngotracheal Reconstruction. Laryngoscope. 2022;132(8):1682-6. https://doi.org/10.1002/lary.29914
[19] Schweiger T, Roesner I, Rodrigues IDS, Evermann M, Frick AE, Denk-Linnert DM, et al. Functional outcome after single-stage laryngotracheal reconstruction with rib cartilage grafting. J Thorac Cardiovasc Surg. 2022;163(1):313-.322.e3. https://doi.org/10.1016/j.jtcvs.2020.11.155
[20] Choudhury A, Laxmidhar MI, Ahirwar N. Has the Pectoralis Major flap Really Become Obsolete? Indian J Otolaryngol Head Neck Surg. 2023;75(3):2172-6. https://doi.org/10.1007/s12070-023-03842-x
[21] Tracy LF, Patel SN, Buckmire RA, Shah RN. Laryngeal reconstruction for recurrent desmoid tumor using three-dimensional modeling: A unique approach for a rare tumor. Laryngoscope. 2019;129(9):1989-92. https://doi.org/10.1002/lary.27756
[22] Weber JF, Rehmani SS, Baig MZ, Lebovics R, Raad W, Connery C, et al. Novel composite trachea grafts using 3-dimensional printing. JTCVS Open. 2021;5:152-60. https://doi.org/10.1016/j.xjon.2020.11.001
[23] Yang ML, Chen JF, Chen Y, Lin WK, Tang H, Fan ZW, et al. Scaffold-Free Tracheal Engineering via a Modular Strategy Based on Cartilage and Epithelium Sheets. Adv Healthc Mater. 2023;12(6):14. https://doi.org/10.1002/adhm.202202022
 Figures
 References
 Peer
 Information
Figure 1. Surgical procedure for vertical hemilaryngeal defect reconstruction with vascularized tracheal cartilage using a pectoralis major flap. (A) The pectoralis major muscle and thoraco-acromial artery. (B) The pedicled pectoralis major muscle flap wrapped around the tracheal cartilage. (C) The trachea was cut to create a pedicled pectoralis major muscle-tracheal cartilage flap. (D) The right hemilarynx was resected vertically. (E) The trachea with muscle flap was sutured to the remaining left larynx. (F) End-to-end tracheal anastomosis and lower tracheostomy. PMF, pectoralis major flap; TC, tracheal cartilage.
Figure 2. Immediate postoperative video laryngoscopy. (A) Immediate postoperative findings. (B) Glottic inlet and suture line. (C) Anastomosis at the upper margin of transplanted tracheal cartilage. (D) Anastomosis at the lower margin and end-to-end tracheal anastomosis.
Figure 3. Video laryngoscopy findings at 28 days postoperatively. (A) Glottic entrance. (B) Laryngotracheal anastomosis site. The video shows slightly edematous mucosa, a well-supported laryngeal cavity without collapse, and well-healed anastomosis without obvious granulation.
Figure 4. Postoperative CT images of the larynx. (A, B) Immediate postoperative images showing the semi-arc-shaped transplanted tracheal cartilage segment and a gas-fluid level in the laryngeal cavity. (C, D) CT images at 28 days demonstrating a patent laryngeal cavity and well-supported reconstructed laryngeal cartilage.
Figure 5. Hematoxylin and eosin staining of laryngeal tissue at 28 days postoperatively. (A) Normal side of the hemilarynx. (B) Operative reconstructed side, showing restored tracheal cartilage and mucosal structures.
[1] Akali NR, Jaya AC, Balasubramanian D, Iyer S, Thankappan K. Islanded facial artery musculo-mucosal flap for partial pharyngeal defect reconstruction after total laryngectomy: Case report. Head Neck-J Sci Spec Head Neck. 2021;43(1):E1-E6. https://doi.org/10.1002/hed.26522
[2] DePorre AR, Schechtman SA, Hogikyan ND, Thompson A, Westman AJ, Sargent RA, et al. Airway Management and Clinical Outcomes in External Laryngeal Trauma: A Case Series. Anesth Analg. 2019;129(2):E52-E4. https://doi.org/10.1213/ANE.0000000000003843
[3] Hayden RE, Chang BA, Mullin DP, Patel AK, Nagel TH, Howard BE, et al. Bipedicled submental musculofascial "hammock" flap for salvage laryngectomy closure reinforcement. Head Neck-J Sci Spec Head Neck. 2021;43(1):198-202. https://doi.org/10.1002/hed.26473
[4] Liao CH, Huang JF, Chen SW, Fu CY, Lee LA, Ouyang CH, et al. Impact of Deferred Surgical Intervention on the Outcome of External Laryngeal Trauma. Annals of Thoracic Surgery. 2014;98(2):477-83. https://doi.org/10.1016/j.athoracsur.2014.04.079
[5] Werner J, Scaglioni MF, Ko SS, Rajan GP. Preservation of laryngeal function through reconstruction of the supraglottis and thyrohyoid membrane with a chimeric anterolateral thigh flap after supraglottic laryngectomy: A case report and literature review. Microsurgery. 2021;41(5):462-7. https://doi.org/10.1002/micr.30708
[6] Vella O, Blanchard D, de Raucourt D, Rame JP, Babin E. Function evaluation of laryngeal reconstruction using infrahyoid muscle after partial laryngectomy in 37 patients. Eur Ann Otorhinolaryngol-Head Neck Dis. 2020;137(1):7-11. https://doi.org/10.1016/j.anorl.2019.09.004
[7] Yeh DH, Sahovaler A, Fung K. Reconstruction after salvage laryngectomy. Oral Oncol. 2017;75:22-7. https://doi.org/10.1016/j.oraloncology.2017.10.009
[8] León X, López M, García J, Casasayas M, Rovira C, Quer M. Indications and results of extended total laryngectomy with en-bloc resection of overlying cervical skin. Eur Arch Oto-Rhino-Laryn. 2019;276(11):3179-84. https://doi.org/10.1007/s00405-019-05573-8
[9] Lai YS, Lee YC. Comparison of outcomes between circumferential and near-circumferential pharyngoesophageal reconstruction using anterolateral thigh flap. J Plast Reconstr Aesthet Surg. 2023;85:316-25. https://doi.org/10.1016/j.bjps.2023.07.010
[10] Kang SK, Qamar SN, Khan IM, Crosbie R, Tikka T. 10-Year Experience with the Modified Pectoralis Major Flap: The Use of the Deltopectoral Flap to Reduce Skin Tension. Indian J Otolaryngol Head Neck Surg. 2023;75(2):358-65. https://doi.org/10.1007/s12070-022-03154-6
[11] Banaszewski J, Gaggl A, Buerger H, Wierzbicka M, Pabiszczak M, Pastusiak T, et al. The reconstruction of large laryngeal defect with medial condyle femur corticoperiosteal free flapa case report. Microsurgery. 2016;36(2):157-60. https://doi.org/10.1002/micr.22509
[12] McCullagh KL, Shah RN, Huang BY. Anatomy of the Larynx and Cervical Trachea. Neuroimaging Clin N Am. 2022;32(4):809-29. https://doi.org/10.1016/j.nic.2022.07.011
[13] Mehrban N, Bowen J, Tait A, Darbyshire A, Virasami AK, Lowdell MW, et al. Silsesquioxane polymer as a potential scaffold for laryngeal reconstruction. Mater Sci Eng C-Mater Biol Appl. 2018;92:565-74. https://doi.org/10.1016/j.msec.2018.07.003
[14] Fossum TW, Dewey CW, Horn CV, et al. Small Animal Surgery. 5th ed. St Louis: Elsevier; 2019:739-756.
[15] Monnet E. Tracheostomy. In: Tobias KM, Johnston SA, eds. Veterinary Surgery: Small Animal. Vol 1. 2nd ed. St Louis: Elsevier Saunders; 2018:1563-1571.
[16] Andrews RJ, Calcaterra TC, Sercarz JA, et al. Vocal function following vertical hemilaryngectomy: comparison of four reconstruction techniques in the canine. Ann Otol Rhinol Laryngol. 1997;106(4):261-270. https://doi.org/10.1177/000348949710600401
[17] Piazza C, Paderno A, Del Bon F, Grammatica A, Montalto N, Bresciani L, et al. Fascio-cutaneous-free flaps as primary reconstruction in salvage total laryngectomy. Eur Arch Oto-Rhino-Laryn. 2021;278(1):219-26. https://doi.org/10.1007/s00405-020-06137-x
[18] Wolter NE, Vilchez-Madrigal LD, Jh JHG, Greer MLC, Peer S, Highmore K, et al. Predicting Maximal Costal Cartilage Graft Size for Laryngotracheal Reconstruction. Laryngoscope. 2022;132(8):1682-6. https://doi.org/10.1002/lary.29914
[19] Schweiger T, Roesner I, Rodrigues IDS, Evermann M, Frick AE, Denk-Linnert DM, et al. Functional outcome after single-stage laryngotracheal reconstruction with rib cartilage grafting. J Thorac Cardiovasc Surg. 2022;163(1):313-.322.e3. https://doi.org/10.1016/j.jtcvs.2020.11.155
[20] Choudhury A, Laxmidhar MI, Ahirwar N. Has the Pectoralis Major flap Really Become Obsolete? Indian J Otolaryngol Head Neck Surg. 2023;75(3):2172-6. https://doi.org/10.1007/s12070-023-03842-x
[21] Tracy LF, Patel SN, Buckmire RA, Shah RN. Laryngeal reconstruction for recurrent desmoid tumor using three-dimensional modeling: A unique approach for a rare tumor. Laryngoscope. 2019;129(9):1989-92. https://doi.org/10.1002/lary.27756
[22] Weber JF, Rehmani SS, Baig MZ, Lebovics R, Raad W, Connery C, et al. Novel composite trachea grafts using 3-dimensional printing. JTCVS Open. 2021;5:152-60. https://doi.org/10.1016/j.xjon.2020.11.001
[23] Yang ML, Chen JF, Chen Y, Lin WK, Tang H, Fan ZW, et al. Scaffold-Free Tracheal Engineering via a Modular Strategy Based on Cartilage and Epithelium Sheets. Adv Healthc Mater. 2023;12(6):14. https://doi.org/10.1002/adhm.202202022
Peer-review Terminology
Identity transparency: Single-anonymous
Reviewer interacts with: Editor
Details
This is an open access article under the terms of the Creative Commons Attribution License(http://creativecommons.org/licenses/by/4.0/), which permits use, distribution and reproduction in any medium, provided the original work is properly cited.
Publication History
Received 2026-04-16
Accepted 2026-06-02
Published 2026-07-05